
Archive for the ‘Uncategorized’ Category
For a future perfect “Noble profession”
Posted in Uncategorized on October 17, 2022|
A forbidden quote in medical science
Posted in Uncategorized on October 13, 2022|

Definition of HFpEF needs a tweak : Time to make pulmonary hypertension an essential criteria !
Posted in Uncategorized, tagged criteria for hfpef, esc guidelines on hfpef, HFpEF on October 12, 2022|
Though all of us are aware, the incidence of heart failure is increasing exponentially and is the leading cause of global disease mortality, what we fail to understand is, we still lack a good definition cardiac failure.
Defining HF based on EF% is convenient but adds more complexity, and is less scientific too. Still, as of now, we have adopted this. I think, one of the important factors that apparently increased the incidence of HF is the creation of an entity called HFpEF. (Formerly diastolic heart failure)
Thanks to ESC, we have a consensus document, which has defined HFpEF based on functional, morphological, and biochemical features. This is a more refined model from the original Mayo clinic H2FpEF score.
Both are given below.


Can we diagnose clinically significant HFpEF, without pulmonary hypertension?
In my understanding, the answer is No.
Looking at the two schemes (Mayo & ESC) one thing is clear. Pulmonary hypertension is the key hemodynamic expression of HFpEF. It could be either resting and persistent or exertional and transient.t is obvious the PH in HFpEF is post-capillary. (The modern term for pulmonary venous HT). Mind you, while PVH is mandatory to diagnose HFpEF, PAH (precapillary ) is also observed in most patients with significant HFpEF. This is the reason TR jet velocity is included as one of the criteria. (To make things simple, we may need to create a new classification of HFpEF, ie resting vs exertional HFpEF.This is what the diastolic stress testing is all about.)
Final message
It is back to basics & time to dig into the fundamentals, of what exactly we mean by heart failure. Is the elevation of LV filling pressure alone sufficient? Should it happen at rest or at exertion, and whether neuroendocrine activation is necessary? Is RASS activation similar in both HFrEF and HFpEF? Try to find the answer to this. How often does HFpEF fulfill Framingham’s criteria of HF.? ( Löfström et al ESC Heart Fail. 2019)
Trying to understand the nuances of HFpEF, I think, we can make a statement,- HFpEF can not be diagnosed without pulmonary hypertension. It makes a lot of sense the P in the H2FpEF scoring system denotes PH, however, It is assigned only a single point, which needs revision. In fact, there is a strong case to argue and make it an essential criterion.
Paradoxically & curiously HF with reduced ejection fraction (which is the most common form of HF) doesn’t require the presence of PAH to diagnose it. This issue may also be examined.
Reference
Does the Aortic root contract or relax during ventricular systole ?
Posted in Anatomy of heart, Uncategorized, tagged aortic root dynamism, cardiology research topic on October 1, 2022|
Does the Aortic root contract or relax during ventricular systole? Some time back, I asked this question in one of my classes for the fellows and found no takers. Not even a guess? I realized later, it was indeed a tough question. The heart is not the only dynamic organ, as we generally believe. The entire aorta which is an extension of the left ventricle has to be dynamic according to the physics of ventricular-arterial coupling and the momentum of blood flow.
What happens to the aortic dimension with systole?
Even prior to systole, there is evidence, the aorta gets ready to receive the blood from the LV. So, the Aortic root must be larger at the onset of systole. (Ref 2 ) It is been generally agreed now, that the systolic dimension is slightly more by a few mm. That is why aortic dimensions are measured in peak systole as per the American society of echocardiography.
There has been an opposite argument as well. The diastolic aortic dimension could be larger, as the aortic valve is in the closed position and the aortic root distended, & becomes a reservoir of blood that’s meant to be distributed during diastole. What determines the aortic dimension on a moment-to-moment basis? Is it the, LV contractility, pressure, or volume, or the compliance of the aortic wall that determines the aortic dimension and pulsatility? How does a prosthetic valve alter this?
So, what exactly happens to the aortic dimension during the cardiac cycle ?
A wonderfully done study from University Medical Center Utrecht, The Netherlands throws some important facts with their analysis of ECG-gated CT scans in 108 Aortas.(Ref 1)
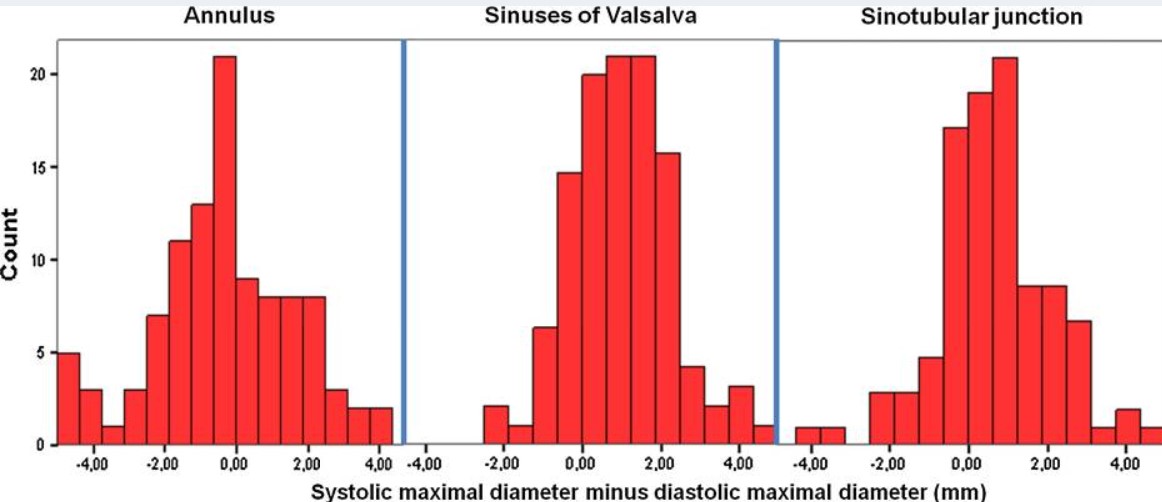
Clinical implication of aortic pulsatility
The implication of knowing (or not knowing )the dynamism of the aorta can be huge.
- Age-related stiffening and onset of systolic hypertension
- Aortic diameter, pulsatility, and shear stress are the key parameters in initiating dissection and its propagation
- Choosing the right sized valve for AVR
- Current interventional heart-throb TAVI involves just a passive placement of the valve in the aortic root. Imagine what will happen, if the foundations are excessively dynamic and shaky
It is surprising, even after decades of vascular research, we lack clarity on what exactly happens to aortic root during various phases of the cardiac cycle. (Currently, paravalvular leak, & migration of TAVI remains a major worry, which has a direct relationship with pulsatility of the aortic root ) One thing is obvious,.Young cardiologists have a lot of work to do in this arena.
Final message
Though the aorta is a direct extension of LVOT, its vaso-motion doesn’t seem to be in complete sync with the cardiac cycle. It tends to have an independent behavior, out of phase with the heart.
As per available evidence, the aortic root dimension can either increase, decrease, or be static in response to LV contractility.
Reference
2. Pang DC, Choo SJ, Luo HH, et al. Significant increase of aortic root volume and commissural occurs prior to aortic valve opening. J Heart Valve Dis. 2000;9:9–15. [PubMed] [Google Scholar]
3. Vesely I. Aortic root dilation prior to valve opening is explained by passive hemodynamics. J Heart Valve Dis. 2000;9:16–20. [PubMed] [Google Scholar]
Civilized and uncivilized, blood pressure response : Learning from the Kuna Indians
Posted in Uncategorized, tagged kuna Indians and hypertension on September 17, 2022|
Welcome to Kuna island. The Kuna Indians are really unique people. living off Panama, right in the isthmus connecting North and south America, The Kunas reside in the San Blas archipelago comprising about 360 islands, of which about 60 are populated by them. They have lived on these islands for centuries, but their exact origin is not completely understood.
These innocent tribes have taught an important lesson in human blood pressure regulation, vascular biology, and salt sensitivity. We know, that high blood pressure, is a maximally researched entity in medical science in terms of etiology, vascular effects, and its control. Still, we don’t know, what are the limits of normal BP for human beings. The debate will not end until we are clear about, whether human beings evolved from monkeys or emerged as de-nova organisms. Recent studies have revealed a remarkably low level of mitochondrial gene diversity in monkeys, suggesting that there has been remarkably little genetic admixture. (Ref 2)
What we know from 3000-years-old human history is, blood pressure is directly related to the physical work done by us and the diet we eat. While salt is considered pro hypertension, physical activity is a much more important determinant in bringing it down. Normal BP in a pre-civilized world was low compared to a civilized population. They also enjoyed better vascular health. Where is the evidence? It comes from the life cycle of Kuna Indians. Here is a very unique paper published in the Hypertension journal.(Ref 1) Three cheers to the authors for confirming this long pending speculation with meticulous data collection. (See the Image)
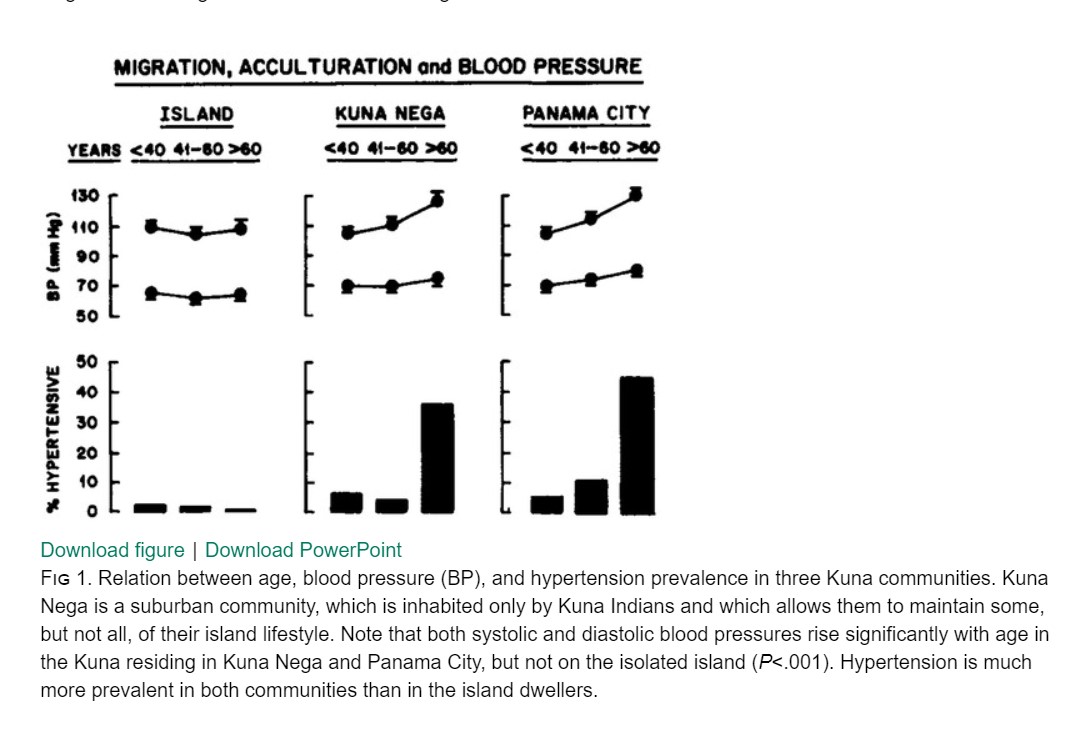
What was special in Kuna’s diet that prevented cardiovascular events? It is been shown in the study by Hollenberg, their diet contained rich in cocoa and flavonoids that made the difference.(The salt consumption was still high though)
As Kuna’s moved out from their primitive lifestyle to first, the Kuna Nega,(a suburb) and subsequently to a fast-paced Panama city. See the impact on their systole and diastolic stress on the heart. The loss of protective effect of the native diet is obvious.
Final message
Lifestyle is the buzzword today. It is a by-product of the new civilized world that will define human health. The human vascular tree tries to sync with a new lifestyle pushing the BP curve to the north. The true normal BP for denova-human beings may still be very much lower than what we believe. A crazy suggestion was made, that human BP should match that of non-sedentary monkeys. I Hope, we get more evidence later for such hyperboles. As of now, we have to accept, hypertension is largely due to disorder in human civilization, development, and prosperity.
How about embracing the styleless lives of native Kunas to take control of our vascular health.
Reference
BROWN (S.), ATKINS (C.), BAGLEY (R.), CARR (A.), COWGILL, DAVIDSON (M.), EGNER (B.), ELLIOTT (J.), HENIK (R.), LABATO
(M.), LITTMAN (M.), POLZIN (D.), ROSS (L.), SNYDER (P.), STEPIEN (R.) – Guidelines for the Identification, Evaluation, and
Management of Systemic Hypertension in Dogs and Cats. J Vet Inern Med, 2007, 21: 542-558
OCT is not “Obsessive compulsive tomography”
Posted in Uncategorized, tagged coronary Imaging, ILUMEN study, oct, opitical coherence tomography on September 8, 2022|
This is the story of PCI to LAD from the customary bifurcation workshop for the budding experts, which ended up with a compulsive final OCT run-through, triggering a debate on what to do with the side branch.
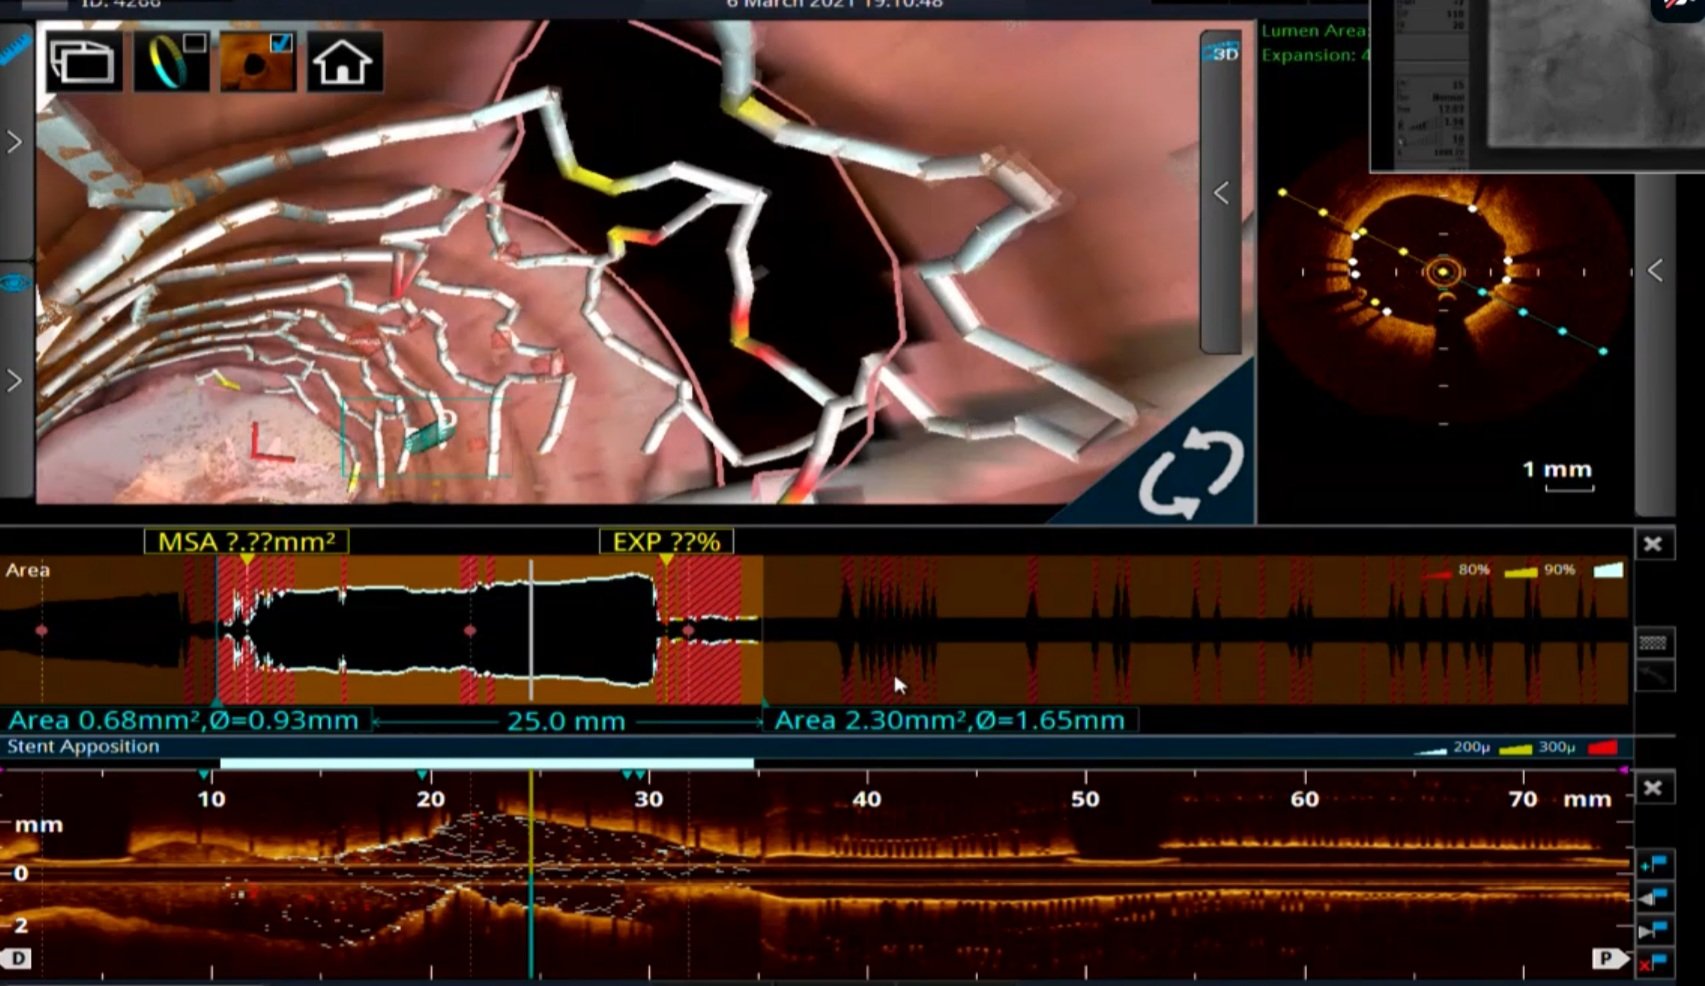
- Just balloon dilate the distal strut
- Would consider a second stent. Maybe a TAP depending upon LCX morphology
- At this stage, I would like to know the FFR or iFR across LCX Jail.
- Get rid of this OCT, Let me have look at regular CAG. I bet I can make a better decision.
- Leave it alone if the clinical status & profile is good
Leave it alone? Is it not an incomplete Job?
Definitely incomplete. Please realize, No job is complete in interventional cardiology. If we believe so, it exposes our Ignorance ( & some arrogance). Intentional side branch jailing is an integral part of PCI techniques. Are we not ignoring day in and day out.
Someone in the audience asked Why did you do OCT at all?
The chief operator quipped “You can’t ask this silly question in a scientific workshop. We bought the OCT kit to improve the quality of PCI. We are proud of it. Really feel blessed to use it and I am sure my patients will benefit from it”. We have to agree with him. These new Imaging techniques though give us extra high-definition, but it comes with troubling revelations with their new vision. If you are pathologically honest and believe in empowering patients, it is absolutely necessary to convey the following facts in the discharge record as well. It would be something like this, “There was a 120-micron strut crossing the LCX ostium, that might continuously impede a chunk of platelets & RBCs every beat, for the rest of your life and might enhance the risk for thrombosis. (Of course, DAPT will take care of it and ask the patient not to worry)”
OCT: One-minute review
OCT is Indeed a stunning Innovation. It can be useful in all 3 phases of PCI. 1. Assessment and preparation of lesion bed. 2. during stent deployment and optimization. ,3. Post-stenting follow up. The technology has grown so fast, now angiographic co-registration and longitudinal frame reconstruction comes inbuilt. It required 3 versions of LUMEN study and a 4 th one (LUMEN 4 ) is yet to come, expected in 2022 to prove the worthiness (or worthlessness) of OCT.
One attractively named DOCTORS study asked the specific question directly (Does Optical Coherence Tomography Optimize Results of Stenting)” This is from NSTEMI patients .read yourself for the conclusion. It is not convincing to me. DOCTORS study (Does Optical Coherence Tomography Optimize Results of Stenting)”. Circulation 2016; 134: 906.
Mind you, OCT is not only an expertise-dependent procedure, it also has important imaging limitations. It has low penetration max 2mm, can not differentiate lipids from calcium, shadowing behind red thrombus is an issue and most importantly it may miss the external elastic lamina (EEL) and measurement errors are real.
Cost-effectiveness
If an imaging technique to assess a stent *(*Still waiting to prove its worthiness) could cost more than the device itself, realize how good our economic intellect is. Just because your lab has an OCT console, it need not transform into a technically perfect PCI. There are at least half a dozen factors other than Imaging that matters.
Final message
OCT is a breakthrough technology that needs to be used judiciously and it definitely helps us understand the nuances of coronary stenting, especially in complex lesion subsets, and its mechanical and histological contents. However, let us not propagate a false message, that without OCT we can’t perform a perfect PCI. Give due respect to all those sharp-eyed interventional cardiologists with good techniques, who can do a better job, beating the HD vision of OCT, with their native blindness.
Reference
Post-amble
Can you guess how many PCIs are done with OCT guidance globally?
It is less than 5 %. In India, it must be, I guess it is < 2% So, we are living in a terrifying world of coronary interventions, where 98 % of PCI is happening blindly, sub-optimally, and unscientifically., Data from CLI-OPCI registry adds more panic: Centro per la Lotta Contro l’Infarto – Optimisation of Percutaneous Coronary Intervention (CLI-OPCI) registry: It says device-oriented cardiovascular event (DOSE) is high with OCT detected sub-optimal PCI.
So, what are we going to tell our patients who will undergo PCI (undergone) without OCT guidance in the past, present, and future?
Simply ask them to forget this OCT stuff. Just reassure them. Nothing will happen.
Why “Isolation of pulmonary veins” and “Arrest of AF” may turn out to be two different events !
Posted in Atrial fibrillation, Uncategorized, tagged affirm trial, atrial fibrillation, CABANA trial, fire and ice study atrial fibrillation, pulmonary vein isolation, race trial, rate vs rhythm control in af, RF ablation for af, right atrial focus in atrial fibrillation, svc focus in af on August 19, 2022|
AF is not only the most common cardiac arrhythmia,it is also an extensively researched entity in cardiology literature. We are trying to rein in, this arrhythmia for the past three decades with multiple strategies. Drugs, pacemakers, ICDs devices, surgical cuts, RF catheters, and the latest technique is trying to frostbite the atrial electrical circuits with ICE. ( Karl-Heinz Kuck,N Engl J Med 2016 )
It is believed that up 60% of AF originate from pulmonary veins. What does it mean? So, when we blindly suggest PV Isolation routinely for all PAF, there is 40% futility straightaway! Apart from the hugely variable anatomy of the pulmonary veins, there are prohibitive levels of recurrence due to PV reconnections. Maybe, will find new technical solutions as we are now moving in 2nd or third generation cryo balloons, 4D imaging, contact force sensing, etc. But let us not forget there are other sources of focal electrical activity too
Importance of non-PV ectopic beats initiating AF(Ref 1,2)
- Superior vena cava (SVC),
- left atrial posterior free wall (LPFW),
- LA appendage
- crista terminalis (CT),
- coronary sinus ostium (CSO),
- Ligament of Marshall
- Interatrial septum (IAS)
Ablation or no ablation, we need to reflect on two things in the management of AF.
1. AF can be triggered by totally different mechanisms like intermittent hypoxia, adverse electrolytic flux, diffuse atrial interstitial pathology or amyloid, etc. Before calling the appointment desk of the EP guy’s office please rule out all the systemic causes. This could be your last (lost) chance to save the atria from pulmonary burns.
2. This one is more important. Read carefully. It is not a divine protocol that demands us to restore sinus rhythm in all patients with AF. There is an excellent knowledge base, backed up by wonderfully done studies. (Need not mention the trial name, I think) that should effectively neutralize our compulsive & misplaced urge to bring back sinus rhythm in all chronic AF.
With respect to the overall outcome, It hardly matters whether you treat the AF by rate control or rhythm control. While there is major technological leap in our fight with AF.It is heartening to know simple measures like regular exercise can control or reverse AF by atrial fatty mass regression.
Final message
We have played with fire for quite some time within the innocent lesser chambers of the heart (RF ablation) and burnt our reputation considerably. Now, silently we have decided to fall for a more friendly weapon ICE. But we must remember our obsession with the pulmonary vein as the only source of initiation of AF is essentially flawed. Further, all these hyper-technology-based combat of AF is indicated only in a fraction of our patients (Maybe 5-10%)
Reference
Postamble
If you think this write-up is too biased, please read the CABANA trial fully before ditching this post into the dustbin.
Poignant moments in History of cardiology : James Mackenzie’s dying heart !
Posted in history of cardiology, Uncategorized, tagged Dr James Mackenzie, father of british cardiology, history of cardiology, land mark article in cardiology, wisdom papers in cardiology on August 14, 2022| Leave a Comment »
1908, Going back on the time machine, more than 100 years ago, world war I was all set to begin, and the great Titanic was being built in the Belfast shipyard. A parallel histroy is being created in cardiology.
This is a brief story of Dr. James Mackenzie, a general practitioner from a remote Scottish village who ended up with the title of the father of British cardiology. Dr. Harvey might have invented circulation, but it was Mackenzie who taught the science of arterial pulse and wrote a classic on the topic to the new medical world. He was able to decode the secrets of the jugular venous pulse as well and diagnosed various arrhythmias including atrial fibrillation at the bedside. He used the polygraph to record his vast observations in pulse and JVP waveforms which were popularised later by Dr. Paulwood. ECG was just beginning to enter the scene in the 1920s. This makes his work all the more significant, as his treatise on pulse and JVP were based purely on clinical acumen.

Sir James Mackenzie, 1853-1925
Apart from his stupendously successful academic life, it was through his death, that he sent out an extraordinary message to the scientific community. His deep desire to know the truths about coronary atherosclerosis was astonishing. Since he himself was suffering from angina and possibly Infarct, he became his own subject of study. He became case number 28 in his own book on cardiology. When he was on his death bed, as a last wish he Insisted his colleagues do a learning post-mortem and keep his heart in the same hospital he worked. When he died in the early morning of January 25th, 1925, as per his wish, his students Dr. Parkinson,(WPW fame) and another pioneer Dr.Thomas Lewis did an autopsy on his heart.

It is tragic to know about the final days of Dr. Mackenzie’s life and how their beloved students performed the postmortem on their teacher and later published their findings in the British Heart Journal. (BHJ link )It is one of the poignant moments ever recorded in the history of cardiology, a doctor wishing to teach cardiology lessons to the generation next with his dead heart.No surprise, he is being conferred the title of father of British cardiology.

Final message
How could an unassuming GP practicing in a remote rural place reach the pinnacle of scientific glory?
Yes, it is possible. Today’s young (super) specialists must realize, that true scientific minds don’t require exotic research labs, tools, or conflict-ridded funds from Industry for the growth of science. All we require is a passion to teach, and the curiosity to learn. The rest of the things will follow… I think that was the message in the great life of Sir James Mackenzie.
Further reading

http://www.dundee.ac.uk/museum/exhibitions/medical/cardiology/cardiology1/
Is Curative medicine an enemy of “Preventive medicine’ ?
Posted in Uncategorized, tagged prevention is better than cure, preventive medicine on August 10, 2022|

It is so unfortunate, the quote has almost become a silly cliche for every one of us including the physicians, and patients. Preventive medicine always struggles to prevail over its starry-eyed colleague, curative medicine in spite of the fact that cure is an assumption in many illnesses. Classic examples are diabetes, hypertension, and atherosclerotic disease. Many of the chronic diseases that afflict human beings have no complete cure. At best we can control them. All that we do is symptomatic and supportive treatment.
Overlaps between preventive and curative medicine
Meanwhile, we must also understand preventive medicine is not only about sanitation, nutrition, and a good lifestyle. Most facets of curative medicine are actually preventing complications of the disease. So in reality curative medicine works by preventing events. There is a big overlap.
The cure is often a mirage except in treatable medical emergencies. Still, we strongly believe every disease listed in the ICD code has a cure. It would be unbecoming of a medical professional if we don’t try for a cure. We are repeatedly sensitized that cost (& effectiveness too )should never be an issue. The Insane world of medical merchandise does this propaganda perfectly. How many of us realize PTCA and CABG are essentially poor palliative procedures in our attempt to conquer atherosclerosis and CAD? No surprise, 90% of the global cost of medical care is spent on prolonging the last one month of human lives.
Preventive medicine is less popular, primarily because it demands more effort, perseverance, and also wisdom. On the other hand, curative medicine gives a sense of accomplishment and also the glamor of modern medical modalities. Of course, one of the new chapters to be added in the current preventive medicine books is the public health dysfunction due to incongruous tertiary care.
We are caught in a vicious cycle of poorly administered preventive medicine and indiscriminate usage of curative medicine, with the former under siege, by the latter with its bigger design. It is almost certain, that the malignant growth of curative medicine is indirectly preventing the“preventive medicine” to reach its desired goals.
Preventive medicine has its own issues. One ingenious way to increase the glamor quotient in preventive medicine is to increase the cost and mode of administration of (Apple watch!) No, It didn’t work. What about five-star preventive master checks? Maybe, it works on an individual patient level, but still, a suspect value on a global scale. The problem with master health checks is their skewed priorities. It aims to catch the disease very early in the asymptomatic or subclinical stage and try to administer the cure on a large scale, with an illusion of an intervention. (Recall the PSA times on the prostate, now the breasts armed with BRACAs may end up in the same story.)
Final message

No doubt “Prevention is better than cure” will be an immortal medical quote. Two things are essential. 1. The term preventive medicine is to be understood in proper context. 2. We may need to clip the redundant wings of “curative medicine” and divert the wasted resources to resurrect the much-maligned specialty of preventive medicine, for human goodness.
Counterpoint
There are fundamental gaps between the two limbs of treatment. It sounds like a crazy regressive statement to criticize curative medicine. Both shall grow and prosper on their path.
But … why is it not happening?
Call it as “Vascular astrology” : Network medicine and computational genomics
Posted in Uncategorized, tagged computational genomics, network medicine on July 23, 2022|
When does the high blood pressure befriends blood sugar and instigates the LDL to initiate the vascular damage? Does it sound like medical astrology? Yes, welcome to a new world of network medicine, polygenic risk score & computational genomics. Experts believe this is going to be the future of medicine.
Dr. Jospeh Loscalzo, Physician-in-Chief Brigham and Women’s Hospital, a leader in the field gives a brief introduction.
How to understand these complex subjects?
We need not bother much in one sense. It’s all made to look complex by big data machines and modern scientific wordplay. It is true, that the power of computing and machine thinking will help us reach hidden secrets in our bodies. However, the bottom line is, If we live a simple. peaceful, worthy, active life we can afford to forget about this sophisticated risk predicting science, which comes loaded with unlimited anxiety. Let the science grow at its own pace.
Imagine the consequence of a powerful artificial intelligence algorithm telling us in advance all the possible future biological adversaries with 100% accuracy.
Final message
Do you believe in astrology, an ancient Indian science? No. Never!
Do you believe in network medicine: Yes for sure!
Reference
Two good review articles on Network medicine
Categories
-

-
The contents of the this blog is being published as Kindle E book , as per the request of many of the readers. Every article will continue to be open source in this site. Again I shall reiterate the book format is not aimed at any commercial intent. It is only to facilitate learning in a single book format Here is the link to book
https://amzn.in/d/euhL5vu Archives
- September 2026 (5)
- August 2026 (8)
- July 2026 (6)
- June 2026 (9)
- May 2026 (6)
- April 2026 (11)
- March 2026 (10)
- February 2026 (8)
- January 2026 (8)
- December 2025 (11)
- November 2025 (7)
- October 2025 (8)
- September 2025 (7)
- August 2025 (9)
- July 2025 (10)
- June 2025 (8)
- May 2025 (9)
- April 2025 (7)
- March 2025 (10)
- February 2025 (4)
- January 2025 (9)
- December 2024 (11)
- November 2024 (8)
- October 2024 (10)
- September 2024 (5)
- August 2024 (5)
- July 2024 (6)
- June 2024 (5)
- May 2024 (4)
- April 2024 (7)
- March 2024 (4)
- February 2024 (8)
- January 2024 (6)
- December 2023 (8)
- November 2023 (13)
- October 2023 (14)
- September 2023 (5)
- August 2023 (6)
- July 2023 (10)
- June 2023 (5)
- May 2023 (5)
- April 2023 (4)
- March 2023 (5)
- February 2023 (2)
- January 2023 (7)
- December 2022 (3)
- November 2022 (5)
- October 2022 (5)
- September 2022 (4)
- August 2022 (3)
- July 2022 (9)
- June 2022 (2)
- May 2022 (1)
- April 2022 (2)
- March 2022 (1)
- February 2022 (3)
- January 2022 (7)
- December 2021 (3)
- November 2021 (5)
- October 2021 (8)
- September 2021 (4)
- August 2021 (6)
- July 2021 (6)
- June 2021 (7)
- May 2021 (5)
- April 2021 (4)
- March 2021 (3)
- February 2021 (6)
- January 2021 (8)
- December 2020 (4)
- November 2020 (5)
- October 2020 (7)
- September 2020 (7)
- August 2020 (10)
- July 2020 (6)
- June 2020 (9)
- May 2020 (9)
- April 2020 (5)
- March 2020 (7)
- February 2020 (3)
- January 2020 (4)
- December 2019 (4)
- November 2019 (6)
- October 2019 (3)
- September 2019 (6)
- August 2019 (3)
- July 2019 (1)
- June 2019 (3)
- May 2019 (2)
- April 2019 (2)
- March 2019 (2)
- February 2019 (4)
- January 2019 (2)
- December 2018 (2)
- November 2018 (2)
- October 2018 (2)
- September 2018 (1)
- August 2018 (2)
- July 2018 (3)
- June 2018 (1)
- May 2018 (3)
- April 2018 (1)
- March 2018 (3)
- February 2018 (3)
- January 2018 (1)
- December 2017 (3)
- November 2017 (3)
- October 2017 (3)
- September 2017 (2)
- August 2017 (2)
- July 2017 (2)
- June 2017 (2)
- May 2017 (4)
- April 2017 (3)
- March 2017 (3)
- February 2017 (5)
- January 2017 (3)
- December 2016 (2)
- November 2016 (5)
- October 2016 (4)
- September 2016 (3)
- August 2016 (5)
- July 2016 (3)
- June 2016 (4)
- May 2016 (3)
- April 2016 (6)
- March 2016 (4)
- February 2016 (3)
- January 2016 (5)
- December 2015 (6)
- November 2015 (5)
- October 2015 (8)
- September 2015 (2)
- August 2015 (5)
- July 2015 (7)
- June 2015 (4)
- May 2015 (6)
- April 2015 (5)
- March 2015 (7)
- February 2015 (15)
- January 2015 (8)
- December 2014 (5)
- November 2014 (9)
- October 2014 (7)
- September 2014 (9)
- August 2014 (5)
- July 2014 (11)
- June 2014 (5)
- May 2014 (4)
- April 2014 (5)
- March 2014 (8)
- February 2014 (8)
- January 2014 (5)
- December 2013 (7)
- November 2013 (7)
- October 2013 (14)
- September 2013 (12)
- August 2013 (15)
- July 2013 (15)
- June 2013 (15)
- May 2013 (15)
- April 2013 (15)
- March 2013 (15)
- February 2013 (15)
- January 2013 (15)
- December 2012 (15)
- November 2012 (15)
- October 2012 (15)
- September 2012 (15)
- August 2012 (15)
- July 2012 (15)
- June 2012 (15)
- May 2012 (15)
- April 2012 (15)
- March 2012 (15)
- February 2012 (15)
- January 2012 (15)
- December 2011 (15)
- November 2011 (17)
- October 2011 (17)
- September 2011 (17)
- August 2011 (21)
- July 2011 (20)
- June 2011 (17)
- May 2011 (15)
- April 2011 (17)
- March 2011 (25)
- February 2011 (20)
- January 2011 (20)
- December 2010 (18)
- November 2010 (21)
- October 2010 (21)
- September 2010 (25)
- August 2010 (20)
- July 2010 (10)
- June 2010 (11)
- May 2010 (19)
- April 2010 (16)
- March 2010 (14)
- February 2010 (22)
- January 2010 (18)
- December 2009 (20)
- November 2009 (20)
- October 2009 (3)
- September 2009 (21)
- August 2009 (19)
- July 2009 (12)
- June 2009 (12)
- May 2009 (11)
- April 2009 (15)
- March 2009 (21)
- February 2009 (4)
- January 2009 (12)
- December 2008 (13)
- November 2008 (9)
- October 2008 (22)
- September 2008 (20)
- August 2008 (16)
- July 2008 (14)
- June 2008 (7)
Blog Stats
- 6,738,751 hits
Please give your feed back .
Click below to see who is watching this website live !

- This site will never aim for profit. Still ,this donation link is added at the request of few visitors who wanted to contribute and of-course that will help make it sustainable .

Please Note

 Dr.S.Venkatesan MD
