It is fashionable to frequently change the terminology, definitions, and classification of cardiac disorders. Now, the ESC is renaming therapeutic strategies in heart failure. Terms like OMT (Optimal Medical Therapy) and GDMT (Guideline-Directed Medical Therapy) have been taken off the table. A new term called FMT, (Foundational) AMT (Additional) and GDIT (Guideline directed Interventional therapy)
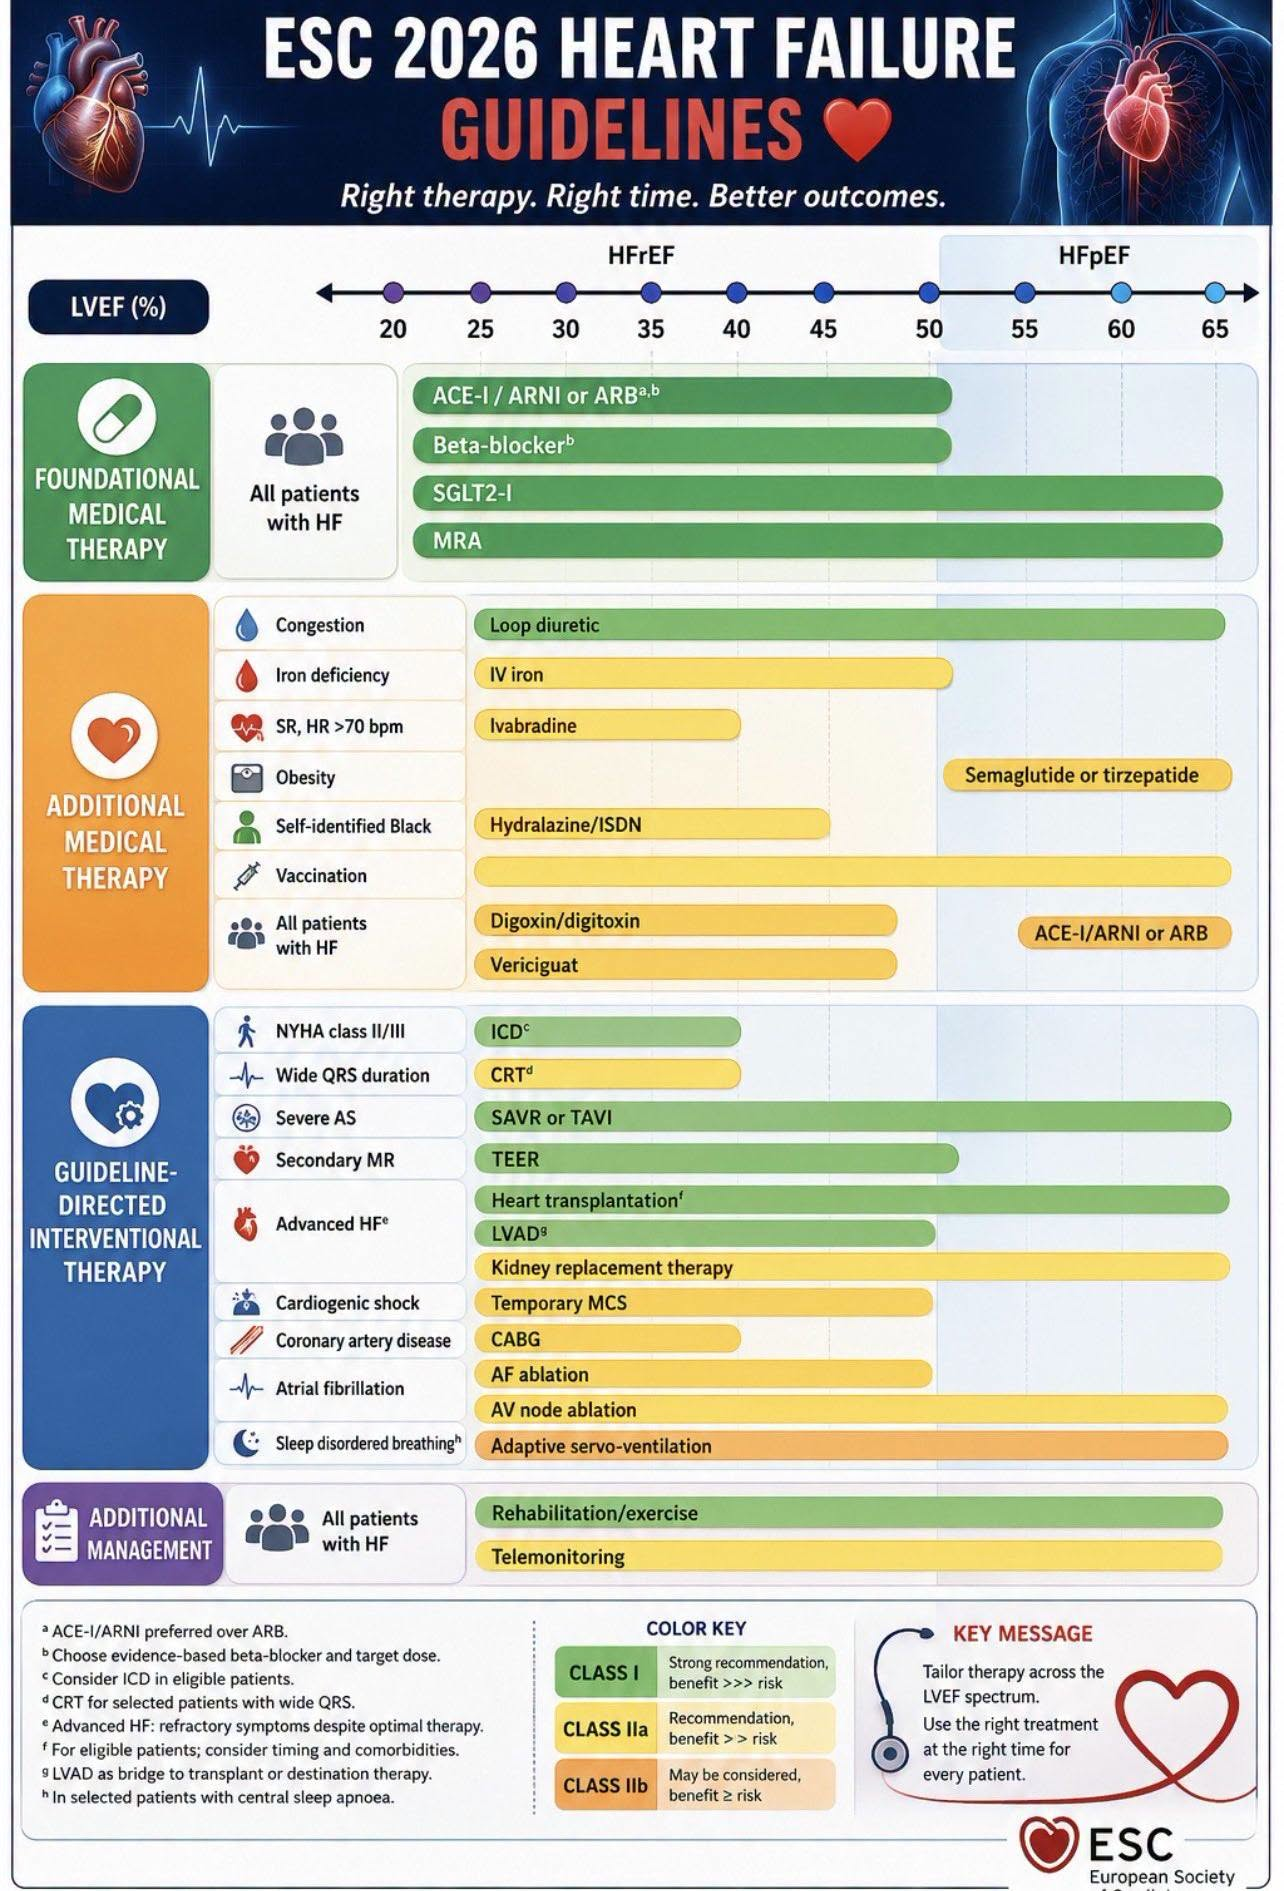
It is Intriguing to see more green color in the device arena and add on therapy is still yellowish.Note : The diuretics, despite bring the only green in the add on category, still considered unfit, to be part of the foundation.
What could be the reason for this?
“Optimal” is entirely subjective, and guidelines are always fluid ( Including the current one!) A few things are particularly glaring in this update. For instance, the term “interventional therapy ” has been introduced, as if laying a pharmacological foundation is not an intervention by itself.
Why Digoxin is not in the foundation ?
Digoxin the wonder drug used for centuries was previously looked down upon. It was kicked out in earlier guidelines, but has now been brought back and placed under the category of “additional drugs”. As a cardiologist who has continued using this drug and rejecting those old guidelines, I was called unprofessional and unscientific. Now, I realize: who was really being unscientific all this time?
*Ask a simple question, can any physician manage heart failure without diuretic ? How many lives a loop diruerrics are saving every day across the globe & how many lives ARNI’s are unbale to save ? Do we have a one to one study ? We have a serious problem in asking right research questions.
I am sure, the committee will ultimately realize their mistake and will be compelled to move digoxin and diuretics to the foundational therapy.Meanwhile , we should appreciate them for including rehabilitation and exercise as a green intervention, even though it was pushed to the bottom of the list.
Final message
Frequent tinkering of nomenclature, classifications, and definitions in cardiology has become an academic time pass. It is not going to alter the actual clinical outcomes of heart failure. We need a lot more application of mind to remove the clutter from genuinely beneficial drugs and modalities.



 Dr.S.Venkatesan MD
