
A good collection of resources dedicated to cardiology
A good collection of resources dedicated to cardiology
Posted in Cardiology - Clinical, Great websites in cardiology | Tagged cardiology, dr s venkatesan, drsvenkatesan, madras medical college, top cardiology websites | Leave a Comment »
Myocardial wall motion defects are sine qua non of coronary artery disease. This occurs as regional wall motion defects following myocardial infarction or during unstable angina.Myocardium is divided into 16 segments for this purpose. The wall motion defect occurs in the respective segments , depending upon the compromised coronary arterial blood supply.
Under physiological conditions myocardial segments contract in a synchronous fashion so that the chambers have a uniform contraction and relaxation. The heart is a complex electromechanical organ. Any thing , that interferes the sequence of electrical conduction or mechanical contraction or relaxation can result in WMD.
Apart from this , differential filling of right and left ventricle can make one ventricle bigger or smaller in relation to other ventricle .This makes the ventricle to contract or relax earlier or later (ASD ).This can not produce WMD in the strict sense , but since the IVS is shared between the two ventricles there can be paradoxical septal motion which mimics WMD.
The other major cause for WMD in the absence of CAD is pericardial pathology .we know pericardium limits ventricular dilatation. When there is a defect in pericardium , after pericardiectomy ( cardiac surgery patients) part of the myocardium can bulge out (or tend to bulge ) .This happens often , anteriorly to produce a WMD.
Similarly a pericardial pathology which constricts can cause a regional compression .This can happen in many of the adhesive pericarditis .They may resolve or end up with progressive constriction.These type of WMD is especially common in the posterior surface of the heart just near the AV groove.

Electrical disorders
The much glamorous entity WPW syndromes and it’s variant can result in WMD due to pure electrical short circuiting hence altering the sequence of ventricular contraction .In fact one can try to locate the accessory pathway origin and insertion sites depending upon the WMD .The segments abutting the insertion site , that are innervated by accessory pathway fibres contracts prematurely and out of phase.
Rarely primary muscle disease like cardio myopathy can have regional WMD .This is uncommon as global hypokinesia is the hall mark . Regional variation in fibrotic processes can result in WMD.
CRT : Cardiac resynchronisation therapy is supposed to normalise the pathological WMD sas in ischemic or non ischemic cardiomyopathies. Ironically CRT may induce new wall motion defects if lead position and stimulation protocols are not proper.
Now we have identified regional diastolic wall motion defects as well .This is made possible by myocardial tissue doppler velocity profiles
*Even though it is difficult to explain , isolated electrical de/ repolarisation defects like long QT, early repolarisation syndromes and brugada syndromes have rarely shown wall motion defects(Class 3 , type C observational evidence )
Non cardiac causes of wall motion defects
Final message
Contrary to the popular perception , wall motion defects(WMD) are not an exclusive property of CAD.It can occur in varied pathological states both mechanical and electrical .The implication for not recognizing this fact can be enormous .The “fancy habit” of diagnosing acute coronary syndrome solely by means of echocardiographic WMD (With out ECG / Enzyme changes ) is to be strongly discouraged .
//
Posted in Cardiology - Clinical, Uncategorized | Tagged wall motion defect | Leave a Comment »
Diastolic dysfunction is a common clinical cardiac problem which has no specific therapy.It can occur either in isolation or in combination with systolic dysfunction.The later may be more common.
Isolated diastolic dysfunction
In association with systolic dysfunction
General principles of management
Even though there is no specific drugs to tackle diastolic dysfunction the following measures may have significant impact.
What are the treatments in the horizon ?
Antifibrotic drugs ,Antiproliferative drugs
Collagen breakers ,
Posted in cardiac surgery, Cardiology - Clinical, Uncategorized | Tagged diastolic dysfunction | Leave a Comment »
Cardiac failure is the number one killer of mankind. So far we have believed the major function of the heart is to contract . Relaxation was thought to be a passive process .Now we know, for myocardium to relax properly the calcium which was pumped in to acto myosin complex, has to be taken back into the sarcoplasmic reticulum during diastole .This is mediated by SERCA 2 , Phospholamban the active calcium uptaking kinase.Clinical diastolic dysfunction as a concept has been disputed for too long that has delayed our knowledge gap .
Myocardial relaxation is much more complex than we think !
We have given too much importance to calcium kinetics and diastolic dysfunction .While impaired relaxation and diastolic dysfunction are used interchangably by both researchers and clinicians resting myocardial stiffness is an important parameter that has been overlooked .
The myocardium is made up of not only myocytes , in fact it has more non myocytic components than myocytes themself. Myocytes constitute only 33 % of cardiac mass . The interstitial cells, fibroblasts the extracellular matrix (This is in fact a vague terminology in use !) It is nothing but sheets of tissues made up of collagen criss crossing the myocardial planes. The type 1 collagen is as powerful as stainless steel . Type 3 collagen is little more flexible. The issue here is , how to flex these rigid collagens without compromising it’s contractile role. One can realise , how ignorant it would be be , if we thought altering calcium kinetics within the myocardium is the ultimate answer to tackle diastolic dysfunction .
So our aim is to reduce the resting stiffness of cardiac muscle in pathological states like SHT/LVH/CAD etc . . .
How to do augment myocardial relaxation ?
Altering calcium kinetics within the cell is one option. But as we have discussed much of the stiffness comes from cells which do not have calcium at all (Fibroblasts) or from life less molecules like collagen etc
The proliferation of interstitial cells and fibroblasts make the myocardium stiff.So drugs which inhibit these reactive events may help.ACE inhibitors, ACE receptor blockers, anti aldosterone (Spirinolactone) are vigorously tried by respective patent holders to bring in another indication for these drugs namely positive lusiotropic agents .But the crux of the issue and the fact of the matter is we have not made any break through in finding a positive lusiotropic drug. (Milrinone was shownto have some promise !)
We need to try new concepts instead of trying the existing band of drugs .
The following are some of the options
Collagen – The interstitial collagen may be modified.The so called MMP matrix metalloprotinase which lyse collagen cross linkages can make the myocardium agile and fit.Tissue inhibitors of MMP has a role.
One should remember we can not afford to play the dangerous game of manipulating myocardial structural protein frames . If the myocardium becomes too flabby it will forget it’s primary job that is contraction
Final message
There are thousands of articles in cardiology literature that cry fowl over diastole and few hundred of them devoted to quantify diastolic dysfunction by various imaging technique .
It is unfortunate there is no single drug or intervention that has a meaningful impact on this entity. We look forward for cardiac scientists to divert the resources to find an answer to this problem instead of simply documenting the presence of it .
Common sense has taught us the most effective method that can reverse established diastolic dysfunction is by simple , regular exercise .Exercise not only make the skeletal muscles agile & fit it does the same to cardiac muscle too !
Posted in Cardiology - Clinical | Tagged diastolic dysfunction | Leave a Comment »
We know human heart contracts and relaxes in an active manner .Systole happens when calcium is pumped from the cytoplasm into the actin myosin complex and diastole occur when the calcium is returnded back into the sarcoplasmic reticulam .The rate of calcium reuptake is detemined by the molecules calmodulin , phospholamban and it’s functional status .
When the heart fails acutely , as in asystolic cardiac arrest , does it fail in systole or diastole ?
The seemingly simple question can never be answered dogmatically.
Pathological studies of post moretm specimens suggest contraction band necrosis is a feature of systolic cardiac arrest .We are not yet sure yet . . . How a heart will appear when it stops in diastole .In fact , if a heart gets struck in systole it means systole has actually occured and because it fails to relax it assumes a stone like contracture state .
While the molecular basis are pretty much confusing , what is clear is we do get number of clinical situations where a acute diastolic dysfunction may occur.
Flash pulmonary edema
The mechanism in the former could be sudden afterload mediated mechanical stunning while in the later ischemia mediated acute contractile and diastolic dysfunction.
In both situations there is severe pulmonary venous HT and class 4 pulmonary edema. The credance to concept of acute diastolic dysfunction came to light , when we noticed many of these patient with acute LVF had preserved EF % and absence of MR to explain acute pulmonary edema .
*Coronary vasospasm–induced acute diastolic dysfunction in a patient with Raynaud’s phenomenon http://www.springerlink.com/content/g1774g34544q2482/
Posted in Cardiology - Clinical, Cardiology -unresolved questions, Uncategorized | Tagged acute diastolic dysfunction, acute pulmonary edema, coronary spasm, flash pulmonary edema, ischemic cardiogenic shock, raynauds phenomenon of heart, renal flash pulmonary edema, systolic vs diastolic dysfunction, unstable angina | Leave a Comment »
The most common ECG dilemmas one encounters is to differentiate between the ST segment depression and T wave inversion due to LVH from that of primary ischemia.
Very often , the entity is misdiagnosed . The implication can be serious , and adding further complexity is exercise stress testing is alos prone for errors in these group of patients as false negative or positive results are very common due to basline ST/T changes.So it needs a CAG to confirm or rule out CAD in many .
Still the clinical acumen with the help of ECG can help us to a great extent !
A rough and approximate way to identify primary ischemia is given below.
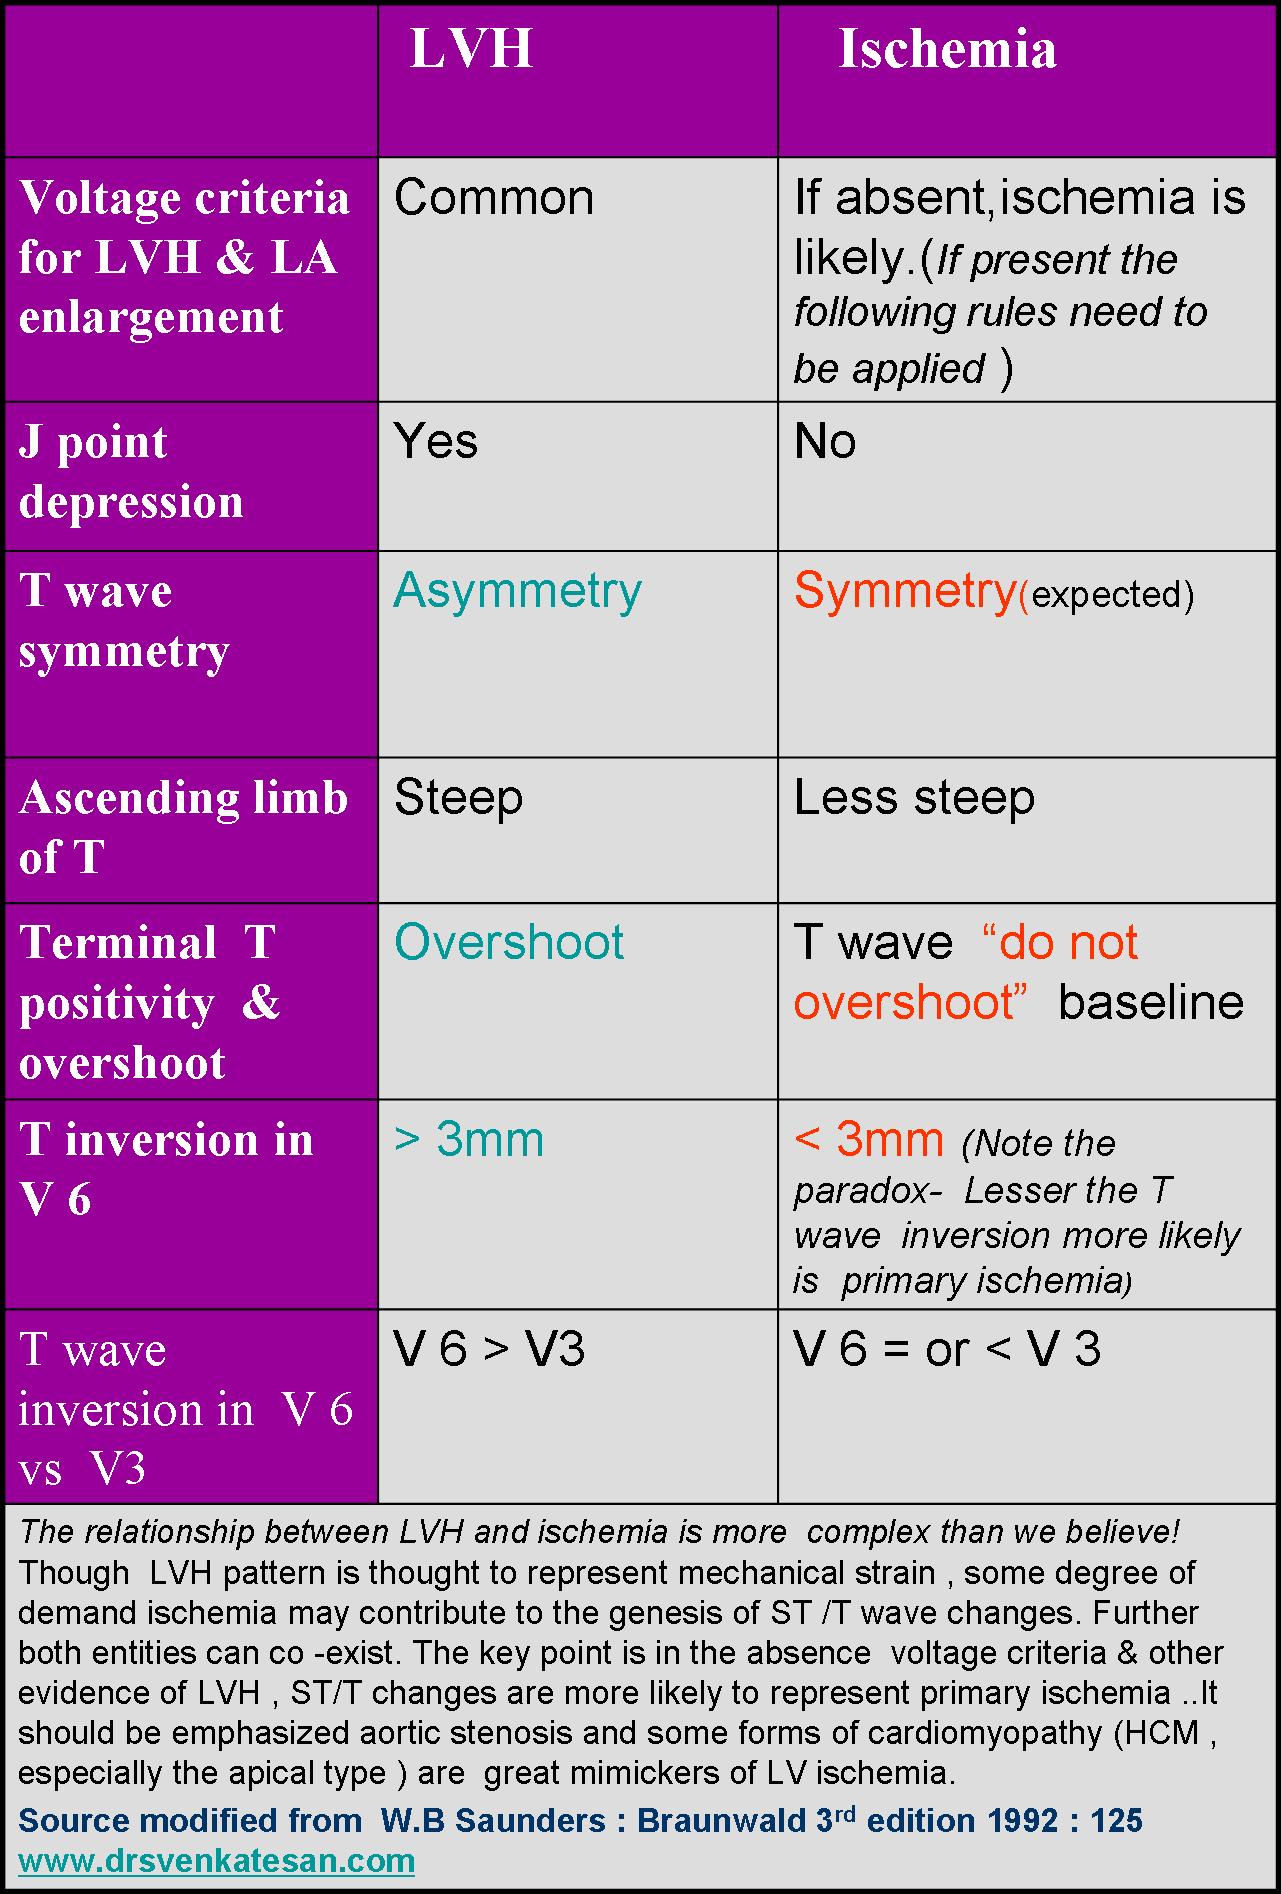
Though these humble ECG features may not be specific to diagnose CAD . One need to remember even a normal coronary angiogram is not synonymous with normal coronary arteries !
Read this blog on limitations of CAG .
Posted in Uncategorized | Tagged ascending limb of t wave, asymmetrical t waves, deep t waves, ECG, j point depression, lv strain pattern, lv voltage criteria, lvh, lvh vs ischemia, overshooting og t waves, primary vs secondary st t, st depression, st segment, symmetrical t wave inversion, T WAVE INVERSION, t wave inversion 3mm, v6 t > v3 t | Leave a Comment »
STEMI is the most common cardiac emergency . It removes more human lives out of this planet than any other illness. Fortunately modern medicine has an answer to this deadly disease . Of course , we are far . . . far away from conquering it. Only if a patient with STEMI reach the hospital one can make a significant impact on it.

This , unfortunately does not happen in about 30 % of patients . They never reach the hospital . It does not imply all those who do not reach hospital die . Current understanding is that the incidence of out of hospital STEMI deaths have been overestimated. The classical teaching of 50% die before reaching the hospital is based on data from old community observations when the awareness , transport, modalities were grossly inadequate.
Now most of the patients has access to emergency care like 911 /108 etc .
It is the era of coronary care in the streets . The concept is , If the patient is not reaching the hospital , let the coronary care reach the patient ! In spite of all these there are major “time pockets” which stand between the patient and his /her ailing heart .
There has been lot of analysis of the various components of delay in STEMI. Of course ,this is directly dependent upon the economic and health status of a country . For example in country like Sweden emergency cardiac services can reach the patient within 10 mts , while a person suffering from an MI in a remote Indian village can reach the hospital only after most of the myocardium undergoes complete necrosis !
Even in urban areas where there is excellent emergency services are available the following factors have a great role in determining the time window and outcome .
Among the above 10 time pockets can you guess which has the greatest potential to make a deep impact on the outcome of STEMI ?
Yes , you are right The first two !Patient misinterpretation of symptoms is the key obstacle for effective care of STEMI .What drives a patient from home or office to a hospital .It is the symptom .If it is severe there is acceleration of every aspect of patient transport to the hospital .The spouse response time is also critical.The problem with STEMI is many times it can occur less dramatically so the patient is likely to miss it!So cognitive response to symptom becomes vital .An intelligent patient or spouse shortens this time window .
Whether to call emergency service or use personal transport ?
This is some times difficult decision especially in country like India. One has to make a rapid assessment , what is the chances of getting a 911/108 services within 15 mts. Developed countries have improved upon ER response time. The issue here is the destination of the patient should be a place where there is a facility to manage a primary VF . In short the ultimate aim of STEMI management in the early hours is to narrow the physical distance between the patient and a defibrillator . This requires availability of health care personnel , equipment , simple physical presence of medical personnel is not sufficient .They should be able to recognise the VF and shock when needed . Next come the method of reperfusion . Shifting to a tertiary hospital for primary PCI or to the nearest hospital for thrombolysis is a separate issue that needs elaborate discussion.
Where should the victim go ?
The answer is not a simple one . There will always be a trade off between optimal STEMI care and the common panic reaction & false alarm and wastage of ER resources .
Since the first hour is very crucial , the outcome depends lot on the patient response pattern .Health education and awareness become vital .Emergency medcation , self adminstred aspirin may be an answer in the future.
What ails emergency cardiac care in our country ?
Every citizen of a country should be made aware of the nearest cardiac medical facility ie . Coronary care unit (CCUs) . It is an unfortuante fact , many of our country people have it in their finger tips , the movie house that is showing the current hit & restaurant that serves best cuisine , have zero knowledge about the nearest coronary care unit in their vicinity . Many lives have been lost because of this ignorance . More important than this , is lives are lost on transit to many ill-equipped ambulances and some times even hospitals .
In the modern era STEMI patient should not die due to an electrical death (Venticular fibrillation) within a ambulance or a hospital .An ambulance that do not have a defibrillator is not an ambulance at all .It is a sorry state of affairs some hospitals do have such ambulances .
There are numerous instances of patients dying in the ER due to poor response time of para medics in defibrillating a VF. It should be made a cognisable offence* to allow a patient die for lack of proper defibrillation within the hospital premises
There has also been instances of good intentional deaths , as a patient is shifted for a better place for catheter reperfusion strategies . If these centres are located in the other end of city , the door ( In fact it is the second door to balloon time ) to balloon time is directly related to the degree of traffic jam ! and has a great potential to accelerate the death of myocardium and some time the patient as well
*Deaths due to pump failure , cardiogenic shock is an allowed mode of death in STEMI as the natural history demands it ! Some body has to die for the sake of statistics
How to recognise the ACS early : Read the link elsewhere in my blog.
Posted in Uncategorized | Tagged coronary | Leave a Comment »
What are the fundamental difference between randomised studies and observational studies ?
New discoveries come from shrewed observations made in bedside or labside while , randomised studies evaluate these discoveries for it’s effectiveness or futileness .
Let us realise , RCTs primarily never contribute to generation of original concepts or discoveries ! .It is a statistical tool to assess an observation .
Click below to reach the excellent knowledge source on above the issue .
PLoS Medicine: Observational Research, Randomised Trials, and Two Views of Medical Science
The fact that observational studies are done with open eyes & mind , it is obvious it demands intense conceptualization and thinking .
Blinded studies are mechanical studies . It is pure statistical research . It requires no thinking , medical mind , in fact one can do it with eyes closed as it is a strict protocol driven , even a non medical men can do a medical research , while it needs a alert mind to do a observational study .
Observational studies , especialy when done retrospectively has zero bias as the case selection and the potential intervention are completed even before the research question is raised. In fact many of the greatest medical breakthrough comes from retrospective analysis. Of course this has to be proved prospectively preferably in a randomised fashion.
So , we the medical professionals , shall do great observational research with open eyes and mind and let the the statisiticins do the outcome analysis blind folded .
If the core medical professionals are bothered more about randomised blinded studies ,which is meant only for evaluation purposes , the future of intellectual medical research is going to be in jeopardy!
Posted in cardiac surgery | Tagged bmj, clinicaltrials, doubleblinded, lancet, medicalresearch, nejm, observationalstudiesbetterthanrct, observationalstudyvsrct, plos, pubmed, Randomisedcontrolledtrial, rct, what is rct? | Leave a Comment »
For all those youngsters , who are into the mystery world of medical research , please begin your journey with this great book. The greatness lies in it’s simplicity in expression & search of truth !
Download this 1 MB marvel , free from http://www.jameslindlibrary.com in less than a minute

Posted in Uncategorized | Tagged commerce in medicine, conflict in medicine, dr s venkatesan, ebm, emprical medicine, ethics in medicine, evidence based medicine, hippocrates, levels of evidence, medicial research, randomised trials | 2 Comments »
Heart rate and human survival has an inverse relationship. This is in fact true for all mammals.The tortoise which has a heart rate of 6/mt lives for over 200 years. The rat which has heart rate of 500 dies does not even celebrate it’s first birth day ! Human beings with an average heart rate of 70 lives for 70 years. 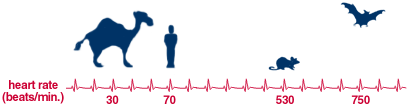
There is a belief human heart is programmed to beat for certain trilion beats in it’s life time .It is possible , with evidence mounting this belief could indeed be true .
People with low heart rate simply outlive the ones with fast heart rate ! Is this due to simple fact they conserve their heart rate .Each human has a reserve of few trillion heart beats for usage in his or her life time .So if this is true what does regular vigorous exercise do to our longevity ! These are pure fantasy questions that need to be answered !
The truth may be regular excercise even though raises the heart rate to high levels it keeps our vagal tone high and maintain the basl heart rate low and there by conserving both heart rate and myocardial oxygen consumption.The other evidence for heart rate being vital in prolonging life is the proven benefits of beta blockers in patients with decompensated heart.
Read the excellent issue dedicated to the importance of heart rate for human survival especially in relation to cardiovascular disease .
From the publishers of dialogues in cardiology .This knowledge sharing comes free of cost
Courtesy of Servier


http://www.dialogues-cvm.org/pdf/19/DCVM19_05.pdf
Posted in Uncategorized | Tagged heart rate | Leave a Comment »




