Arterial grafting, i.e., LIMA to LAD, is one of the revolutionary concepts that redefined outcomes in CABG surgery. It is an artery-to-artery graft, and a perfect size and physiology match that made LIMA-LAD a success story. But the RCA graft choice is not that straightforward.
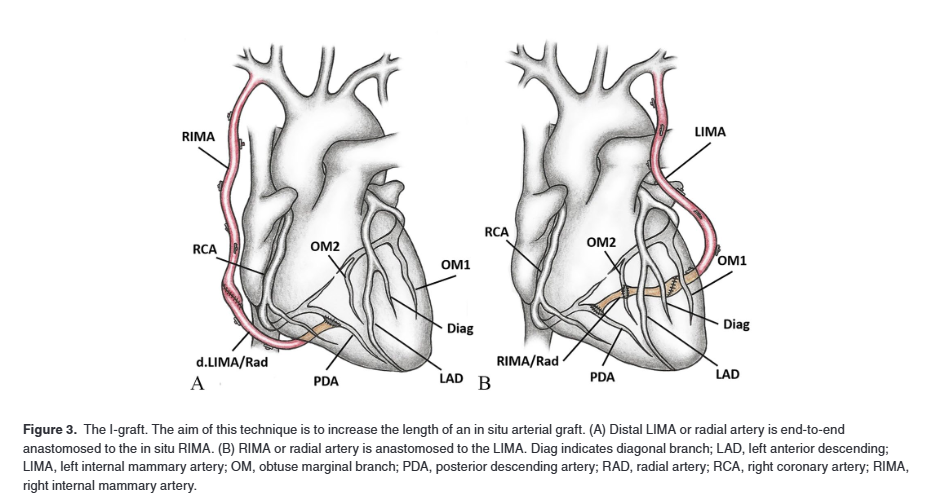
Image source : Prapas SN, Pangiotopoulos et al Open J Cardiovasc 2019
Why arterial graft for RCA is very often avoided ?
A. Anatomical, technical & logistics reasons
B.Coronary to the popular belief arterial grafts are not really beneficial over SVG in RCA.
C.Instituional and surgeon’s preference
D.No, it is never avoided Intentionally. (RIMA, Free radial or sequential LIMA is used whenever required )
Is Arterial grafts really avoided for RCA ?
Conduit selection in CABG need a fine balance between long-term biological durability and real world surgical logistics. Arterial conduits mainly LIMA or RIMA or radial artery possess an endothelium adapted to systemic pressures that resists atherosclerosis, yielding superior 10 year patency and lower rates of adverse cardiac events compared to saphenous vein grafts (SVGs), which undergo progressive intimal hyperplasia and vein graft disease. Consequently, major revascularization guidelines recommend arterial conduits over SVGs for significant lesions even for non LAD locations, especially a dominant RCA, in younger patients with low perioperative risk.
Despite a large cohort of patients meeting these favorable criteria, real-world practice indicate surgeons hesitate to use arterial grafts to RCA and SVGs remain the predominant conduit in over 80 % of procedures. This guideline – practice mismatch is more of technical and logistics .
Why ?
1.Surgeons routinely prioritize and reserve arterial conduits for big brothers LAD & LCX , leaving SVGs for the RCA rather than harvesting a difficult arterial graft with somewhat uncertain survival benefit.
2.Bringing RIMA near to RCA/PDA is not always easy , involves stretching .Free arterial graft is still possible, but need a fairly lengthty one.
3..Also, when RCA has only moderate stenosis (or diffuse distal disease) or where competitive flow from LAD can induce vasospasm in arterial grafts. In contrast, SVGs are larger caliber, lengthy, and most importantly user friendly without compromising flow.
4.With off pump , minimal access, Robotic CABG becoming more popular , an arterial graft to RCA is looks still distant wish.
5.Arterial grafts are still considered superior in specific subset of carefully selected lesions and patients.
Final message
Graft selection for the RCA is not a matter of strict science and superiority , it is more a matter of surgeon preference, convenience, institutional protocol. Most surgeons feel, it is not worth the time for a marginal benefit for arterial graft, if at all. My understanding is SVG grafts have become the default option for the RCA. Note: This is in contrast to the LAD, where venous grafts are almost always avoided except in emergency situations or very poor LV function.
Reference




