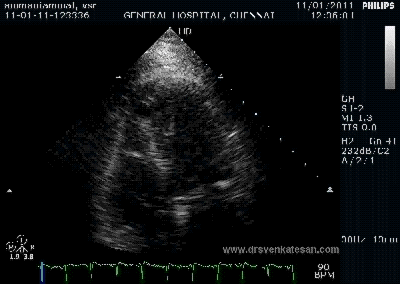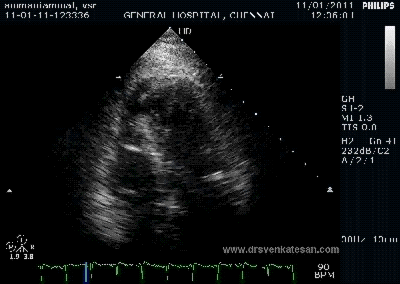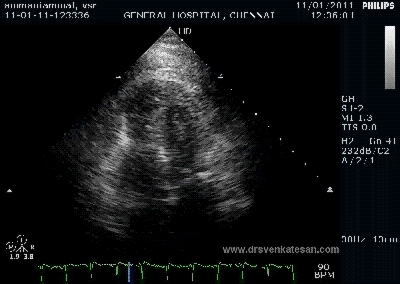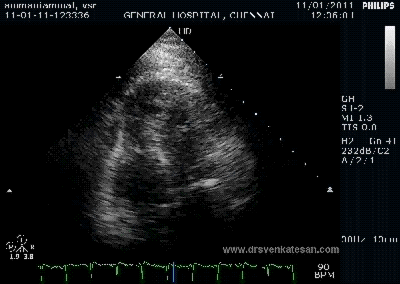
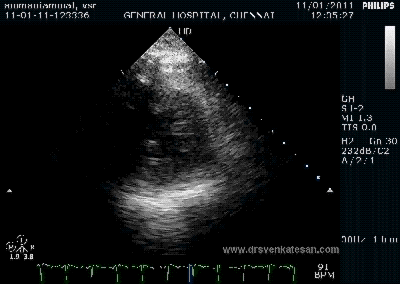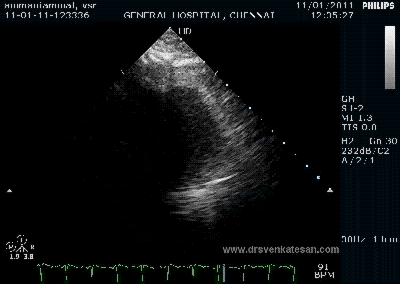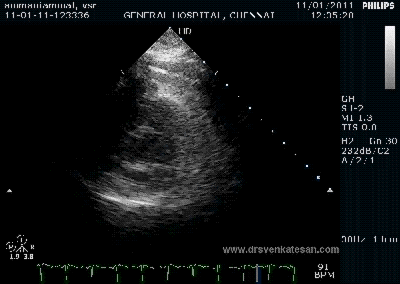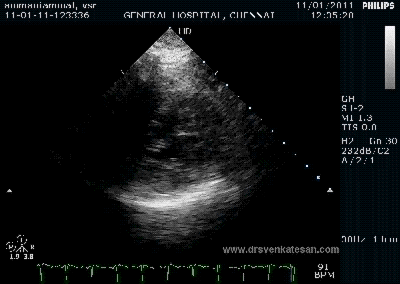
Note the septal rupture is visible even in 2D Echo
Home | Aim of this blog | Archives
January 14, 2011 4:34 pm
We know, electrical deaths constitute the bulk of sudden cardiac deaths in MI. Mechanical deaths due to pump failure, muscle rupture , valve leak , also cause significant deaths .(Surprisingly many of the mechanical deaths may also fulfill the sudden death criteria !)
Free wall rupture is invariably a fatal event. Papillary muscle trunk rupture leads to severe LVF and unless intervened sure to result in fatality.
The ones who tear their interventricular septum are some what blessed ! Here , the rupture does not result in instant death as there is no loss of blood , instead , there is an volume over load of right ventricle followed by the left ventricle after a few beats. Hypotension is the rule. Even though this is a major complication there is something about VSR which makes it unique.
Sudden giving way of IVS has a decompressing effect on the ailing left ventricle.This many times bring a temporary relief to LV and if the patient survives the first few hour he is likely to stabilise further . In fact , sudden deaths within 24hours after the onset of VSR is an exception.This defect always gives the cardiologists and surgeon some time to plan the management. We need to use this time judiciously.
The natural history is delicate . Five themes are possible
* Pleasant themes occasionally witnessed !)
Here is 55 year old women came with extensive anterior MI with lower septal rupture.(She belonged to type 3 of the above scheme)
Note the septal rupture is visible even in 2D Echo
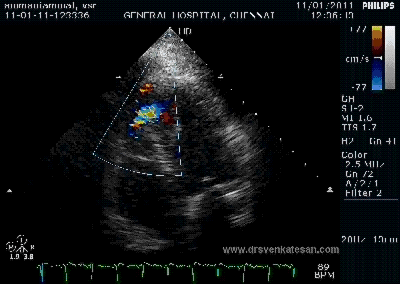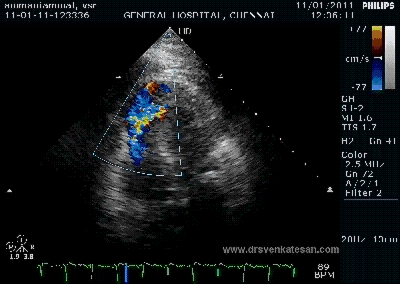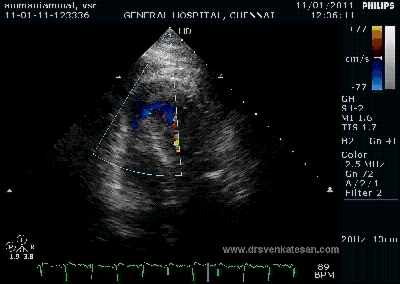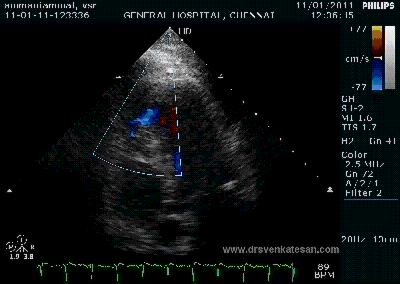
Color flow showing significant shunting from LV to RV.This shunt depends upon the LV contractile function, LVEDP and ofcourse the RV pressure
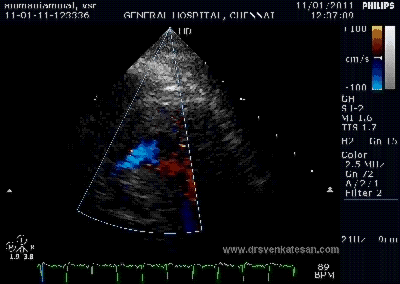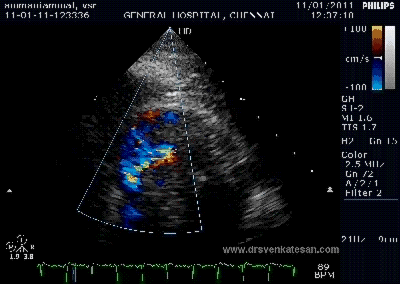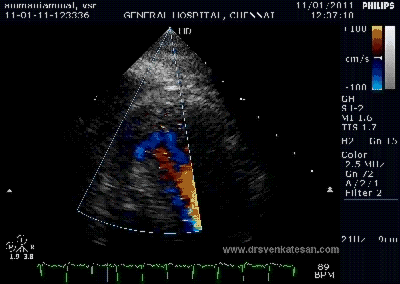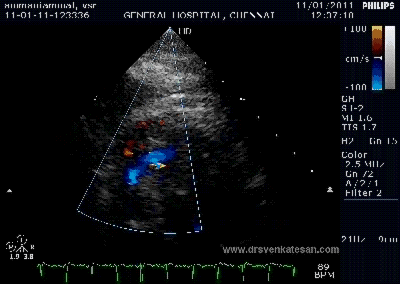
If there is severe RV dysfunction or bi ventricular dysfunction flow across the defect is inconspicuous.Brisk left to right shunting may be an indirect marker for good LV systolic function and absence of significant pulmonary hypertension.Both imply a better outcome.
The main determinant of survival is the underlying LV dysfunction and associated co morbidity(Renal function ) and complications .
Infero -posterior ruptures tend to be complex and may have multiple irregular tracks that makes it difficult to repair.
Investigations
Echo cardiogram is the mainstay .Serial echos should be done to assess the mechanical function and the progress of VSR.Hemodynamic monitoring may be done without injuring the patient .
Medical management
Surgeons role
Timing of surgery
Continues to be a controversy . Surgeons love to operate in a stable patient. But they need to realise , surgery is often needed to stabilise many patients. . The issue of tissue friability is blown out of proportion in the literature .When a life is is at danger we can not worry about friable tissues !
The rule of thumb could be
Surgical options
In our experience each of the above , has a role in a given patient depending upon the logistic , financial , social and even the available expertise. (A good surgeon in bad Institution !)
Is coronary angiogram mandatory before attempting to close VSR ?
Logically yes. If it is not available just do not bother . But, many times , when issue is saving lives , we can not afford to be too scientific , many lives have been saved by not following such strict protocols .A simple emergency thoracotomy and closure of rupture site (Without even touching the LAD ) can be a distinct and viable option in a selected few .
Role of cardiologists
Contrary to the popular belief the role of cardiologists is minimal , except to prepare the patient and hand over to the surgeon.
Interventional approach to close a VSR is currently be termed as an adventurous option ! The VSRs can assume unpredictable shapes and the tears can be multiple in different planes. The devices , catheters and other hard ware are not specifically made to tackle these issues .An acquired VSR should never be compared with congenital VSD.
Posted by dr s venkatesan
Categories: cardiac surgery, Cardiology - Clinical, Cardiology -Interventional -PCI, cardiology -Therapeutics, Cardiology -unresolved questions, Echo library and gallery, echocardiography, myocardial disease
Tags: acquired vsd, cabg, cardiogenic shock, catheter closure of vsr, dobutamine for vsr, free wall rupture, lad bypass in vsr, lvedp in vsr, mechanical complications of stemi, post infarct vsd, stable vsr, surgery for vsr, sutures give way in vsr, tissue friability in vsr, unstable vsr, ventricular septal rupture, vsr closure without cabg, vsr closure without coronary angiogram, vsr vs mr
Mobile Site | Full Site
Get a free blog at WordPress.com Theme: WordPress Mobile Edition by Alex King.
Thank you doctor for u r valuable infrmation
By niyas on November 15, 2014 at 12:19 pm
Dr Venkatesan, may I ask if one should attempt to reperfuse the IRA by means of thromboaspiration/ POBA to establish flow? Or it is a contraindication whereby one should just do diagnostic angiogram, IABP and refer for VSR repair? Any guidelines or evidence?
Thanks
By KL on January 11, 2018 at 8:22 pm