Feeds:
Posts
Comments

It was 1912 , Titanic had just sank off the Atlantic . When the world attention was elsewhere , An unassuming young Dr.Herrick J.B silently working in his Michigan lab inquisitively proposed thrombus occluding the coronary artery is the chief culprit in acute myocardial Infarction.It took seven more decades when Davis et all from Glasgow .UK. proved it by doing dramatic angiographic studies soon after STEMI in year 1979.

Now, even after 100 years , we, the confused cardiologists debate endlessly in glamorous global conclaves in exotic locales whether to aspirate these humble looking thrombus, threatening to damage the myocardium with every passing moment !

Why is this controversy ?

My answer

I am failing to understand the concept and the answer is elusive .While every one agrees that thrombus is true culprit, in bulk of the STEMI , still we are not authorised (In an assertive fashion ) either to lyse as first choice or to aspirate as second choice.

It seems vital, thrombus must be tackled vigorously by any means. Drugs,lytics,(Intravenous or Intra-coronary.) by micro and rheolytic catheters .Only documented, flow limiting complex mechanical lesions must be stented. If we are convinced tackling thrombus by mechanical means is problematic (As studies would suggest ) lysis should prevail over aspiration as a routine measure by default isn’t ?

*It’s a been quite a while , the world cardiology community has made it appear thrombolysing a patient who is otherwise eligible for primary PCI ! a “coronary crime*” Ofcourse , I must say , I proudly commit that crime with rewarding results in many MI patients.

*In fact , I would think not promoting or delaying prompt lysis should qualify for the definition.

In the management of STEMI, prehospital lysis followed by a Intensive care in a good coronary care center is best modality.

This doesn’t mean in-hospital lysis is banished. Yes, STEMI is a cardiac emergency , but triaging STEMI patients must be done by scientific means (STEMI risk score) as well with accumulated wisdom .Rush only true emergencies into cath lab. (A best estimate is about 20 % of all STEMI) If we are not able to decide which STEMI will require prompt PCI , it would Imply we need to go back and do once more the basics postings in coronary care of resident days !

An angry counter from a young Interventionist

Only God can tell whether a given patient with STEMI will (or will not) derive maximum benefit from pPCI. We are not yet trained to make that decision by looking at patient and his ECG.So my logic is all STEMIs are equal. I will continue to do emergency angioplasty in all STEMI patients . I expect them blindly to accept all the potential complications arising out of poking the thrombotic milieu in those low risk patients who might have done well with thrombolysis.

Never afraid of challenges. It is like going to war. Casualties are bound to happen.We have enough technology , Imaging , expertise, to tackle all those complex lesions we encounter during primary PCI especially in elderly comorbid patients. We can even do a triple vessel angioplasty , left main etc. Only Yesterday I posted in my nonstop whatsapp group , where I did a dramatic acute angled bifurcation angioplasty for a stable STEMI patient that required a iFR guided jailed side branch assessment and 3d OCT transmitting stunning snaps of fresh thrombus, ending with a semi culotte procedure.The patient is doing well with a Impella 2.5 device and a high frequency ventilator support and my anesthetist has promised me to wean him soon ! I must actually thank his Glo-Health plus Insurance company for clearing the procedure.

An Important tip for complex lesions during STEMI

We need to know there is always a saving grace , if for some reason we couldn’t accomplish PCI due to complexities of the lesion with multiple IRA mimickers. We can always sheepishly thrombolyse these patients inside cath lab . . . a modality just few minutes ago would have been ridiculed with all our vigor to convince the anxious family for a costly Invasive procedure !

Reference

3. Herrick Original paper . https://jamanetwork.com/

Hyperlipidimia is one of the well-known coronary  risk factor.Serum cholesterol ( Various fractions ) levels are measured to represent that risk. Epidemiologically ,it does a perfect job , however , the fact is , circulating lipids has little correlation with the lipids that’s deposited in the vessel wall.

Time and again , we have proven this as severity of CAD has little  to do with the absolute levels of lipid levels.The number  volume of plaques , the thickness of lipid core, and degree of vulnerability  show  poor correlation with circulating lipid levels than  what we would expect.It tempts us to make a statement , that serum lipid is a poor surrogate marker for CAD. (Still, it may predict the risk of developing it !)

Why this paradox ? What are the  missing links and hidden secrets ?

If you plot a simple graph with serum lipids with  plaque mass, volume and content in CAD population , we might get an  answer .I don’t know whether such a study exist. (Those who find one , please share)

A new concept called cholesterol crystalisation 

It’s not the lipids alone that are responsible for CAD . There is a whole lot of factors , circulating  pro inflammatory  mediators, altered blood coagulation system  , various  inflammatory molecules, , heightened  intra-coronary pressures, genetic vulnerabilities .

Most importantly ,the format  of lipid molecule in side  the plaque seems to matter more  rather the  absolute content.(Small dense LDL, oxidised lipids,Lipid fed macrophages etc )

There is lesser reported phenomenon  called cholesterol crystalisation , with sharp edges (Lipid knife ?) that are responsible random episodes  plaque fissure and rupture.

It was reported in  one of the  rare research paper that came from  (Abela Am J Cardiol.2009)  Factors that crysalise cholesterol include local saturation,  PH, temperature , hydration and plaque RBC contact.

If you argue lipid levels are not  correlating with CAD , how is that reducing it with statins dramatically reduce  CAD and the events ?

Like blood pressure the normality of serum lipids itself is not defined.One insightful definition was proposed , that the level at which a person develops CAD is high for that patient however low it may be..A person who develops extensive CAD  say at a level of  90mgLDL what to infer ? We do not know exact  answer.

That’s why the  concept of satin for all with clinical CAD looked attractive. Still , statin’s action doesn’t help  answer the original query about the relationship between blood lipids and plaque lipids.

Statins beneficial effect is not by reduction of serum cholesterol.It primary acts by  regressing intra-plaque lipids by blocking synthesis of lipids in every cell.The anti inflammatory,plaque stabilisation action of  statin may be  independent of lipid reduction.How much it contributes to overall benefits is not known.

The mystery will deepen

Not every LDL is bad.(I will be slapped if I call them Good LDL !) Small dense LDL , LDL P (Particle) ApoB (The real culprit on which LDL piggybacks ) lipoprotein little a and so many other lipid sub particles are being studied.

Final message

The purpose of this post is not to confuse our understanding about coronary  lipidology but to widen our vision . Serum lipids remain a poor surrogate marker for plaque lipids. This is because , It’s rather a small fraction of sample volume we catch in the  circulating blood , while loads of lipids gets deposited elsewhere in the body ! This also make it clear,no single risk factor in isolation is really CAD risky.It is the combination of risks , genetic susceptibility , LDL subfractions, few unknown risk/protective factors and finally a mandatory trigger(Hemodynamic, Emotional ?) that determine the outcome of  CAD.

So ladies and gentle men , just don’t over react to mildly abnormal lipid levels you often find in  master health checks .There is much more untold stories behind the true CAD risk than the glossy lab printouts would suggest !

Reference

2.

3.The Role of Lipids and Lipoproteins in Atherosclerosis MacRae F Linton, MD, Patricia G Yancey, 

Indian subcontinent has a grand old history with a great civilization that began even before the ancient Greek and possibly Egyptian pharaohs .Post renaissance Europe made the British monarchy enter the country in early 1600s .This could be perceived as a new journey of modern India.In the early days of British colonization through East India company , the province in southern Indian Coramandal coast called Madras (Currently named Chennai) was a key economic and power center. Since the hospitals were the prime requirement to take care the Incoming officers ,Govt general hospital is the first major health care center to appear in India more than 300 years ago (In which the author of this blog is currently associated for over two decades) !

history of madras medical college government general hospital elihu yales

Though we currently call it as GGH , the original name was MGH* Madras General Hospital .

Originally built for the sick soldiers of east India company which functioned in the present St George fort premises.Then president of Madras fort Elihu Yale allotted the adjoining land and was instrumental in building the Govt general hospital in the year 1664 .The academic limb of the hospital the Madras medical college came more than a century later in 1835 .

elihu yale madras medical college

Few decades later in 1718 a Governor of New heaven Connecticut , Cotton Mather from far way North America wanted to start a small hospital who was short of money.He requested through his American contacts of British east India company for a donation from a successful British businessman Yale from Wales who making a fortune in the Indian county of Madras . Since, Yale had an American connection by birth in Boston, was willing to donate the money through Indian gifts worth of 560 pounds which was good enough to build the legendary hospital in New Haven which was named later after his name.

*It should mentioned the first seed of this hospital was planted by another British Sir Edward winter (1622-1686) , the Madras agent for the East India Company .

An article which appeared in Yale journal recently recalled the link between these two institutes.

history of madras medical college yale university drsvenkatesan dr s venkatesan cardiologist

Yale, of course carried a tag of being a controversial leader of British empire for misusing his power, still has his name permanently etched in the history of two great medical institution located far across the globe.

His life ended in 1721 , was laid to rest inside the quiet compound of church of Wales .The dark black concrete letters telling to the occasional visitors about the extraordinary life he lived over 300 years ago.

DIGITAL CAMERA

Elihu Yales 1641 -1721.Born in Boston , Lived in Madras died in London. This memorial is found just outside St.Giles Church Wrexham , Wales .UK

st giles church elihu yales memorial Wrexham 2 wales

St.Giles Church Wrexham , Wales .UK

Click here : How to reach Wrexham ?

Another MGH . . .

The MGH as we know today is Massachusetts General hospital which was stated 150 years later than MGH senior in 1811 in Boston. It some times pains me to compare the growth of two . In terms of science , technology and research they are poles apart But in terms of equitable service , care , and social impact I think the senior MGH would still prevail over. !

Postamble

It is fascinating to know origins of college that taught us medicine.I wonder how many of the current students and the alumni know the grand old history of their Alma mater.I wish they pay a visit to St Giles church Wrexham , Wales once in life time. As we stand in-front of the Yale’s memorial one will definitely get that unique feel of travelling to the vintage past when Chennai GH was born with a baby cry !

Reference

1.http://en.wikipedia.org/wiki/Elihu_Yale

2.http://en.wikipedia.org/wiki/Yale_University

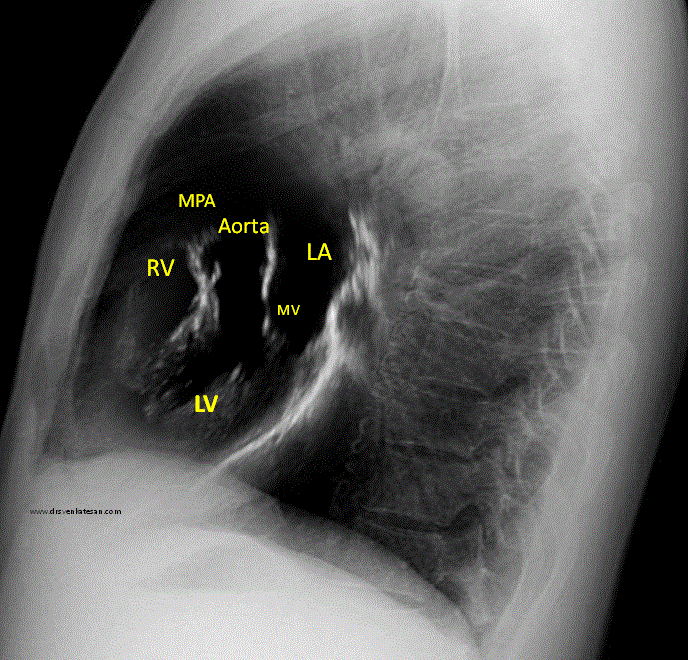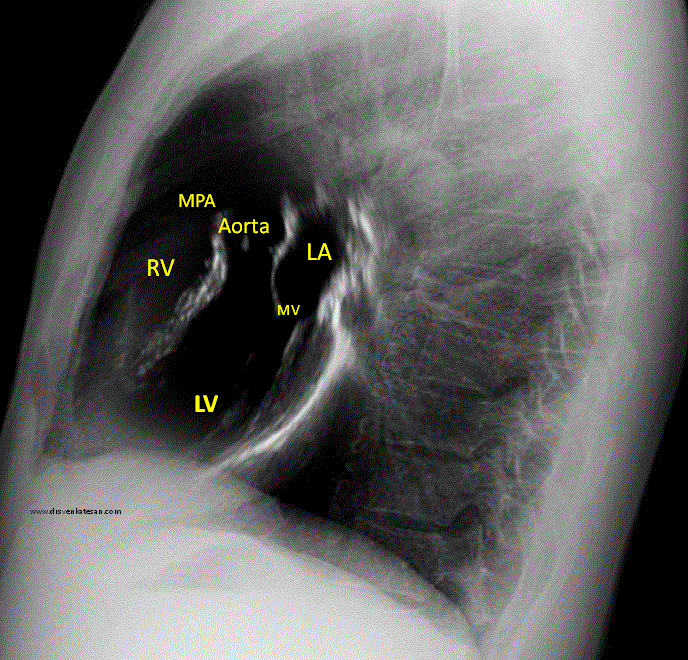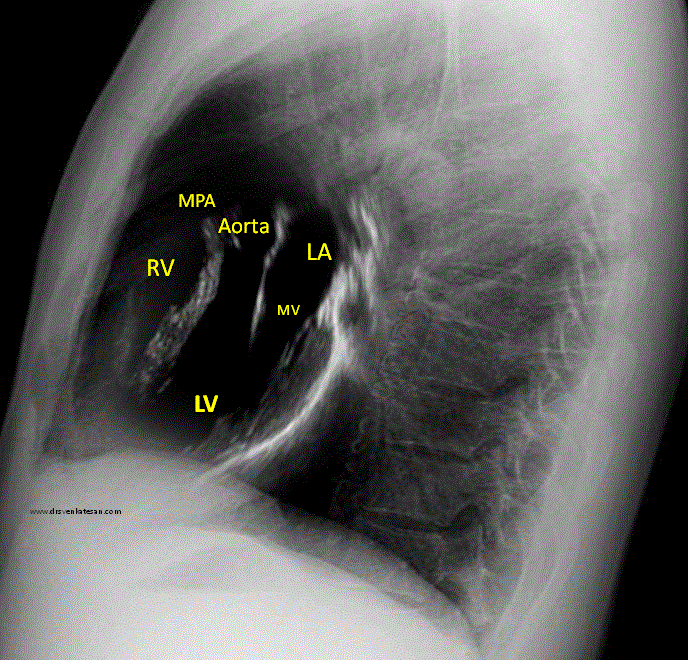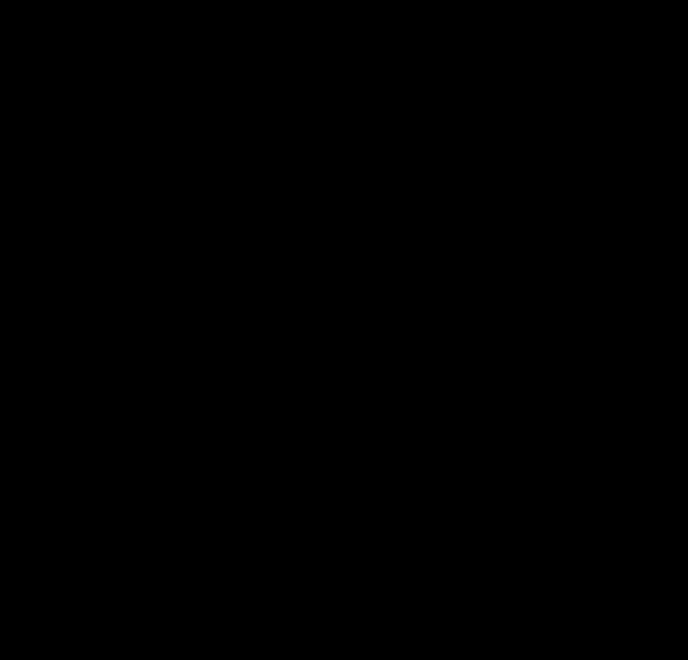
Reading X -ray chest can be as blind as a bat flying in the dark . It needs lots of Imagination . (Many times the blindness continues to cath lab as well during structural interventions is a different story !)

Yes ,its true any one can recognise a cardiomegaly in X-ray . . . but Which chamber is responsible for cardiomegaly ? and quantifying each ones contribution to the increased CTR is the critical question.

We know the 4 chambers in the heart are arranged in a complex pre-specified (Antero -superior and right to left orientation ) still , the CT ratio in X-RAY chest is based on the diameter formed by two chambers only ie right atrium and left ventricle.

However, any of the 4 chamber enlargement can increase CT ratio in pathological conditions.

  • LV enlargement is the most common cause for cardiomegaly as it is the normally border forming.(DCM, Aortic valve, HT diseases)
  • RV can do it when it enlarger grossly forming the left heart border(COPD, Severe pulmonary hypertension of any cause)
  • RA can enlarge to both pressure and volume overload.(CHF, with RVF)
  • LA is least likely to be border forming as it is midline structure .Since It tends to enlarge posteriorly and superiorly it rarely enlarges sideways. Occasionally In severe mitral stenosis it can enlarge to the right and cross the right heart border causing the classical shadow in shadow.

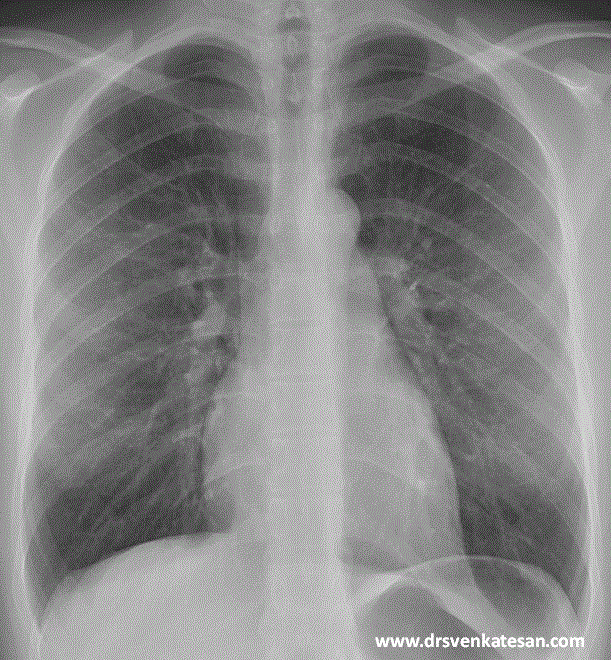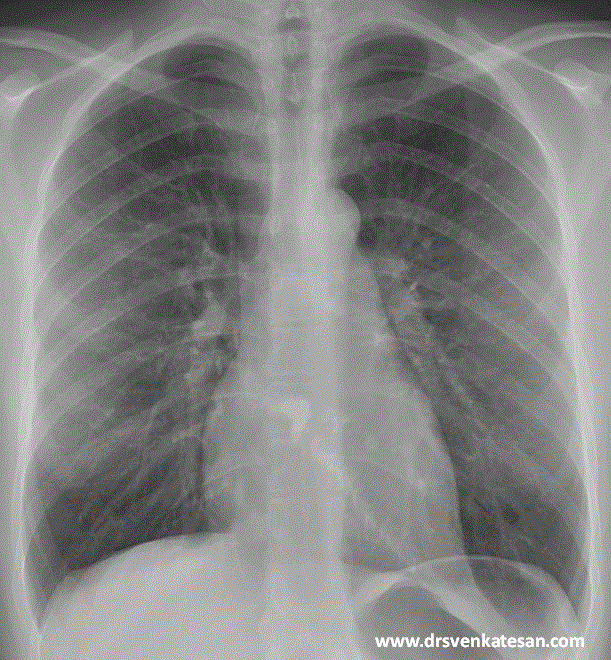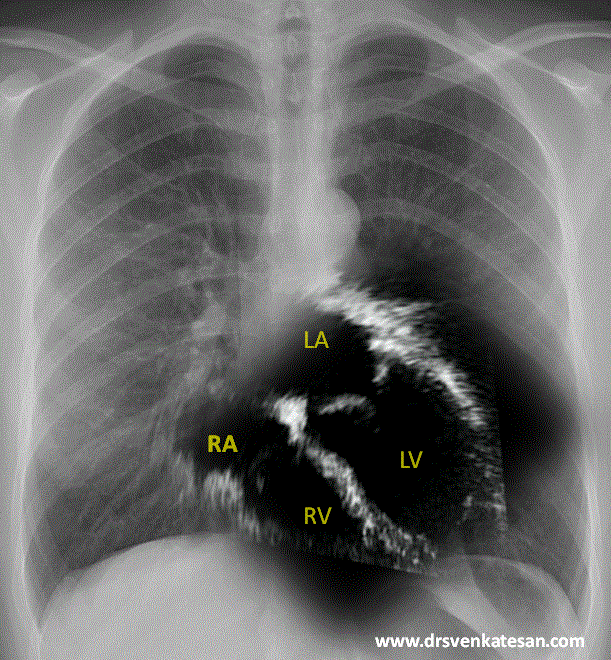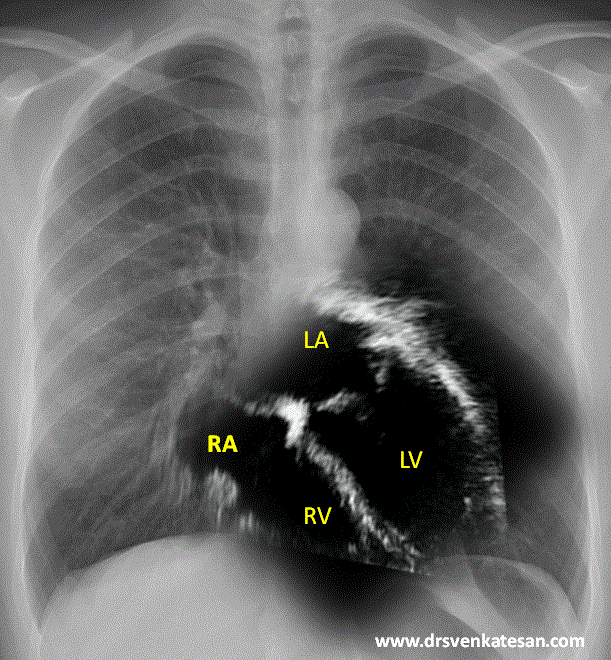
Since I have struggled with X ray orientation of heart chambers in my early days (Still i do sometimes!) Just thought , why we are not fusing a X-ray with a given patients echocardiogram that will help understand the chamber anatomy .

Fusion Image of X ray chest PA view with apical 4 chamber in ECHO. (Rotated to specified angle to match heart border)

Note : The Left atrium is not only left of RA , its also posterior and superior to RA.This makes the IAS not actually pure right left to relationship but also a slight infero to superior and antero posterior orientation.(This can be realised when we puncture the IAS from RA side the needle goes more of superior)

X ray chest left lateral view is fused with para- sternal long axis view. Please note this is not true anatomical correlates. The RV shown in echo is actually RVOT but in X-ray its more of RV body .

* A note of caution : The fused Images are rough attempt to co-register x-ray with echo. There is sophisticated software in some new generation cath labs to mix fluro images with live TEE data that aid in Interventions.

Postamble
A bedside Instant point of care echo is becoming a norm in clinical cardiology practice. Why bother about X-ray then ? Agreed to that point to a certain extent. But, I used to tell my (amused ) students that technology based lazy learning doesn’t help build a strong scientific foundation which would ultimately threaten the patient care one day !

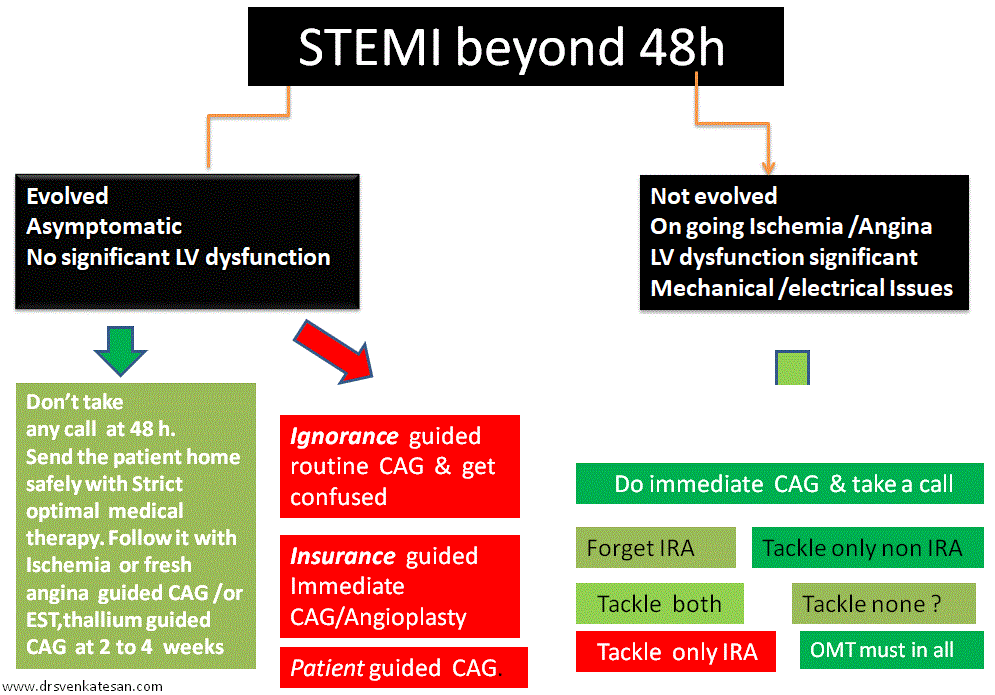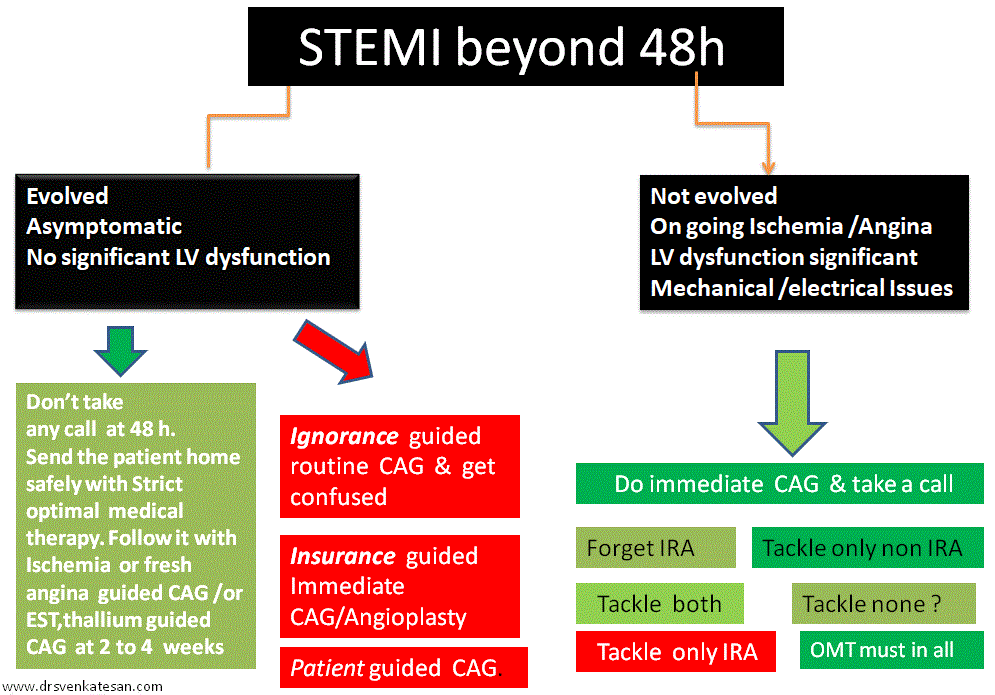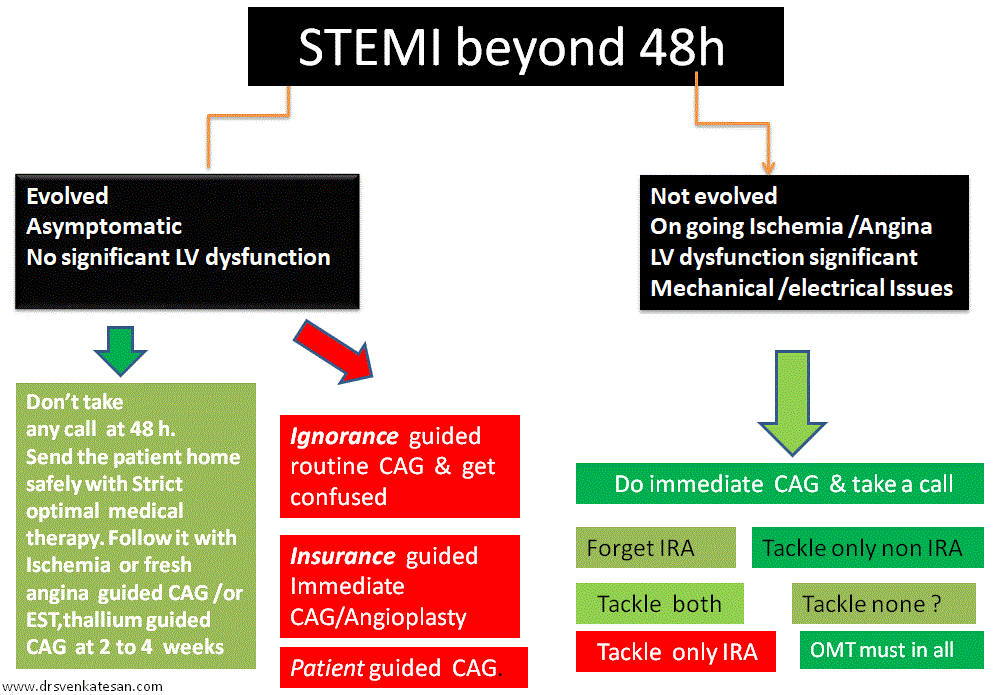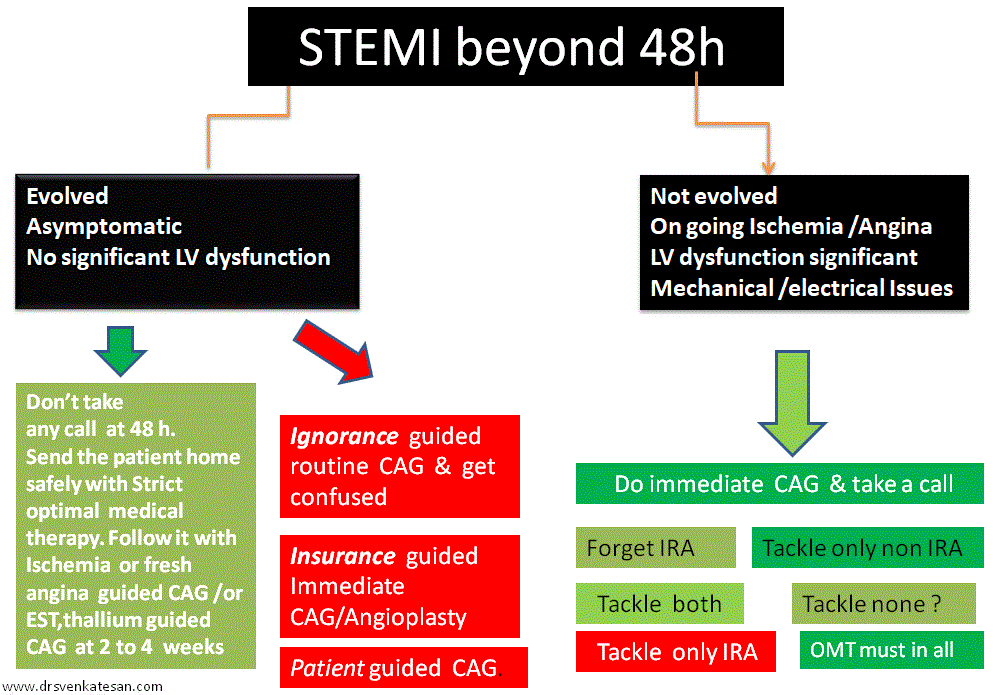
 When half a dozen guidelines from extremely evidence based “Esteemed cardiac societies”  decide to confront an Incomprehensive cardiologist , there is no other way , but to create  a personalised i-Guidelines on STEMI !

*(i-Idiotic)


Yes, Medicine is a funny science ( some don’t agree , Isn’t Art ?) Many of the noble professionals  are silently pursuing their job of saving lives and removing human suffering .Meanwhile, people like this author are needlessly bothered about some Imaginary Issues and write stuff like this one , . . that you are reading now !

Yes, there is an invisible  tectonic shift taking place in the name of  science.The way we practice  medicine currently, it fits in with any of the following descriptions . Divine, Godly,dramatic,miraculous , comical ,cruel or  even outright  brutal ! (I dare not quantify the weightage of each adjectives used above !)

The field of cardiology as I know personally for the past three decades is challenged by  uncontrolled growth (How about proposing 1000 dollar PCSK blocker Evolocumab for a meaningless reduction of few mg of LDL over and above Statin ) Further,the technology goes on to Implode at every corners of wall street ,(Mitra clip for mild MR of DCM ! TAVR for aged Aortic valve )  hijacking  commonsense and cost (where is the effectiveness ?) of every stake holder .

In the process ,the critical  healing power that resides within every biological system is ignored and ridiculed upon .(You become a fool if you say endothelial tissue plasminogen activator and lytic system will take care of a  bulk of the intravascular vascular thrombus if we wait, and  we shall permanently defer an Intervention! Current space aged physicians want to invade every existing (or non existing ) problem with multi pronged military strategy and guess what will happen to the humble  body which becomes the  battle ground.

Coming to the content proper

Sometimes I feel God throws some random truths at an unexpected  time through some extraordinary men ! Here is a most unusual study of its kind from the  Sanctum sanctorum of Medical science , namely  Harvard medical school and Massachusetts  General hospital .I think it was  presented  in ACC Scientific sessions 2018 , Orlando and published in Journal of American heart Association.

Cheers and congratulations to the lead author Dr.Anupam  B Jena* , Physician and professor , Department of health care policy , and Health economist

* A video profile of author is in the reference

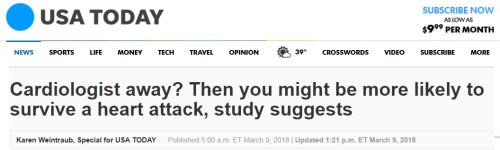
There is no surprise a paper with such a title had a huge  media backlash. USA today reacts  . . .

My observations and final message 

The paper from MGH,  Boston  dwells a sensitive area ,of course it has come with a gross conclusion (However,  I feel it has hit the bull’s eye.) Still, for the critics, I want to tell one thing , who can deny the fact ?  the massive evidence base with 100s and thousands of research papers created by cardiology scientific Industry over the decades is largely a damn squib.

(The problem with acquiring this sort of  ready to synthesise knowledge stuff  is, It sits right inside our brain and bonds irreversibly , refuse to leave even if these dubious practices are proven dangerous ultimately !)

It might appear , the only option  to tackle fake science would be through some dramatic ,less than ideal or mediocre research papers (Or even another fake!) As long as final outcome is good for the public don’t bother about methodology  of such studies.(Does it sound in any way I am a supporter of Donald Trump ,! No I am not !)

Reference 

Now have a look at this (a long post ) which I wrote some time  back. Find out whether  these  scribblings of mine seem to have grown some scientific backing now .

A brief Info about  the author of this unusual paper that has put the field of Interventional cardiology into tail spin and fluttering in cross winds !

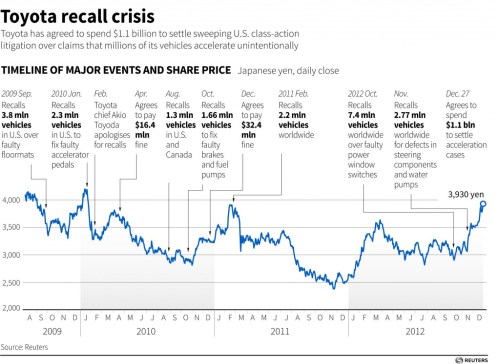
One car company  recalls 100s of  thousands of cars for faulty equipment  issues in recent years . It goes on to add , beware , it’s potentially dangerous  . . . please fix it and bring your car at the earliest !

Toyota-Gra

Mean while , scientific medical literature is flooded with dangerous articles, papers and guidelines . . . and  pose serious threat to your patients !

Please search for the junk knowledge and then go on to expose, erase and  ,  . . . and throw it to dustbin ! After all , research is searching for truth , again and again !

Let us welcome a new era , where we shall get alerts about wrong knowledge  withdrawals and reversal ! Let it challenge  the self proclaimed sancto-scientific medical world  and a new medical literature cleansing movement (MLCM) begin in every sub specialty.

One such paper from Yale is linked below .

medical reversal

Finally  . . . the forbidden message !

venkat quotes 2

Conquering  left main disease is considered as crowning glory for the Interventional cardiologists. For over three decades , CABG has remained the undisputed modality which is being challenged  today. Fortunately, the Incidence of true isolated  left main disease is  low .(If Medina bifurcation subset is excluded)


left main

With growing expertise , advanced hardware and Imaging ( like a 360 degree OCT fly through view ) one can virtually sit inside the left main and complete a PCI .

Still , coronary care is much . . . much  . . . more than a technology in transit !

Most importantly, these complex PCIs require rigorous maintenance protocol  with meticulous platelet knockout drugs , patient compliance and the genetic fate of drug efficacy . (Clopidogrel has since entered the final laps of inefficiency while Ticagrelor has some more time I guess !)

What is the current thinking  about  unprotected left main PCI ? Let us know it from real life experts !

For those answered , yes to  the above question please leave this page , as the following question might  trouble you much !

While competent surgeons are waiting to tackle left main by surgical means ,there are many centers which are Inclined towards  PCI though we lack long-term outcome (At least 10 years like CABG )

Why do you think this is happening ? Are you ready for another crooked poll ?!  

What exactly is left main disease ?

Some of  us also suffer from a knowledge gap and tend to think  Bifurcation lesions  and left main disease are two distinct entities .The fact of the matter is , significant subset of bifurcation lesions are Indeed either left main equivalents or true left mains ( Medina 1,1,1 would constitute > 50 % all  bifurc lesions )  If you include Invisible left main lesions in Medina ( 0,1,1 or 0,0,1 ) detected by IVUS/OCT  it might reach easily cross 90% (Scientific guess !)  Does that mean we have to think CABG even for all complex bifurcation lesions ? and reserve left main disease for isolated discrete mid shaft or ostial left main ?

Final message 

My observation (Sincere to my limited conscience !) at least in this part of the world is : Left main Interventions are  “perceived as pride” and its more related to “show of expertise” and is little to do with patient outcome.Unfortunately , cardiologists should not be blamed for it in isolation as the studies they follow are conflicted.

Forget SYNTAX/PRECOMBAT trials, the two famous studies EXCEL (Favor PCI) and NOBLE were published in 2016 made our life tough .One suggested PCI is acceptable /on par with CABG, while the  other one put CABG superior , ensuring clarity  replaced with confusion ! When we have a dispute , logic would suggest we should fall back on the status quo ie “CABG is superior” unless proved convincingly. Many sections of cardiology society failed to appreciate this.

Post PCI thoughts

*It may not be that hard to do a complex PCI . But, it’s never easier to understand current cardiology literature that is supposed to raise our intellect , which has a direct relevance to patient welfare. Note, many crucial , high stake studies  tend to play academic deceit games  with  linguistic and statistical hyperboles like Non Inferior , likely superiority , Never inferior , near equipoise , regression of hazards, virtual follow-up in  real vs trial world etc , etc !

I can only hope for a better scientific world !

Reference 

  1. Which is the best option for left main disease PCI or CABG ?  Journal of Individual wisdom and evidence based conscience : Volume 1 Chapter 1- Coronary Intellect : Pages 0 to ∞ Jan 2018.

Answer 

Though PTMC in the presence of LA clot is an option in low risk clots , my strategy would be the last one ,whenever feasible. Intensive, monitored Heparin /Oral anticoagulants ( Heparin 5000 units tds or qid  or Low molecular weight heparin Enoxaparin  40-60mg twice a day , Tablet Warfarin /Acitrom with an INR of 3 ) will dissolve  LA clot in  30-50% of times.(Our experience).

The percutaneous clot retrieval system is not available as on 2018.Aortic filters are FDA approved during TAVR. (Why not use the same in PTMC ?)  LA Catheter based regional lysis through PFO is can be an option if patient agrees to the risk.

How long to wait for clot dissolution with Heparin /OAC?

Most small clots or intermediate sized clots ((Up to 2 CM ?)  have been dissolved by 3  months. Even large clots gets dissolved at least in few Instances.Please note, this strategy is applicable only with valves that is fit for PTMC. All others are referred for surgery.

How does heparin lyse a clot  ?

Its a miracle to see it happen, though heparin / OAC are  never considered as thrombolytic agents .It happens because  both heparin and OAC tilts the local   endogenous fibrinolytic forces and thrombus melts , dissolves or disappear altogether. (I am waiting for the day , the scientific community to re-label heparin as a thrombolytic agent, Indirectly though !)

Is there a risk of dislodgement of LA clot during heparin /OAC therapy ?

This question shall be addressed to  God ! It all happens if bad luck strikes you and your patient.

Be wise  . . .  and call your surgeon Immediately when you encounter something like this !

Even if the valve is perfectly eligible for PTMC , high risk  mobile clots, history of  embolic episodes , probing and hyper-googling patients , its better to refer for surgery Immediately. Wait and watch game has a definite risk of stroke and it is especially bound to happen if your patient or their family is anxious !

Reference

Ventricular pressure volume loop is an Important concept (often fearsome !)  to learn for cardiology fellows . . . I would say , It is not that hard to understand !

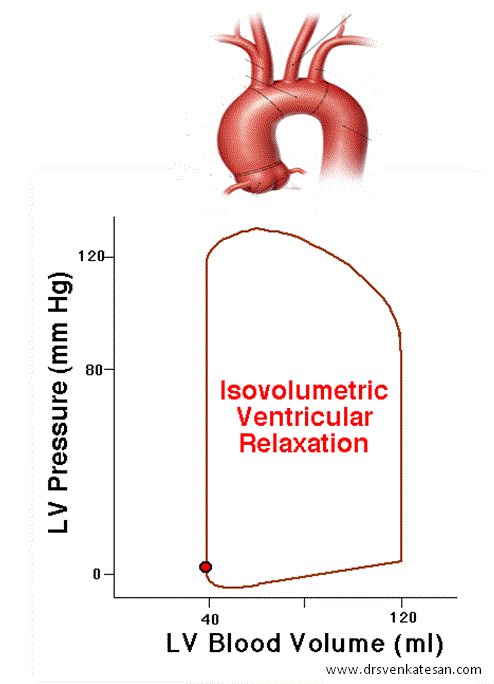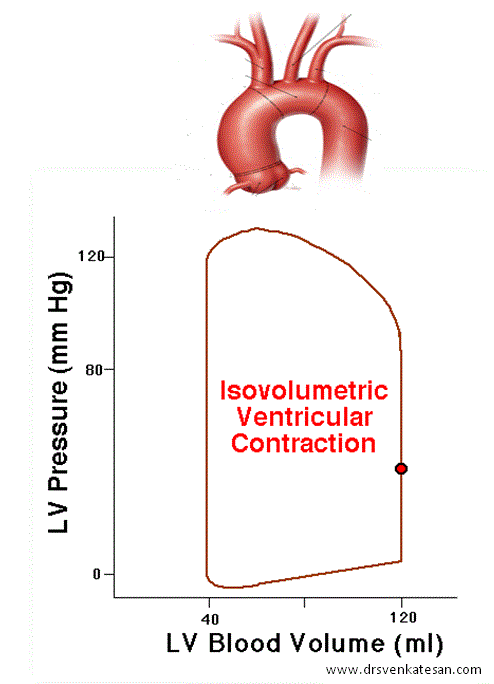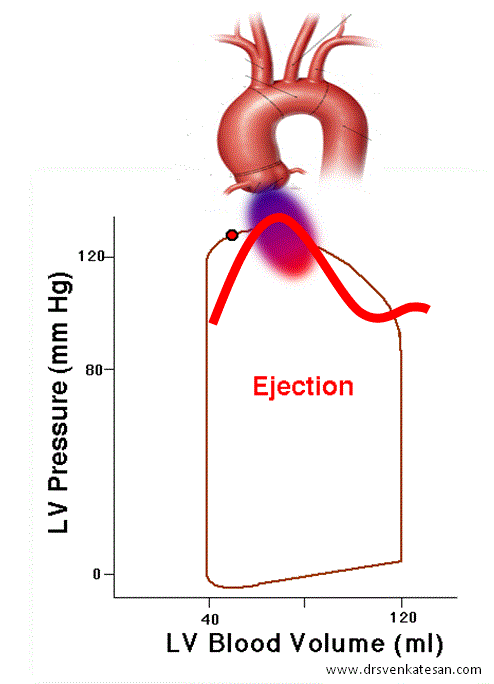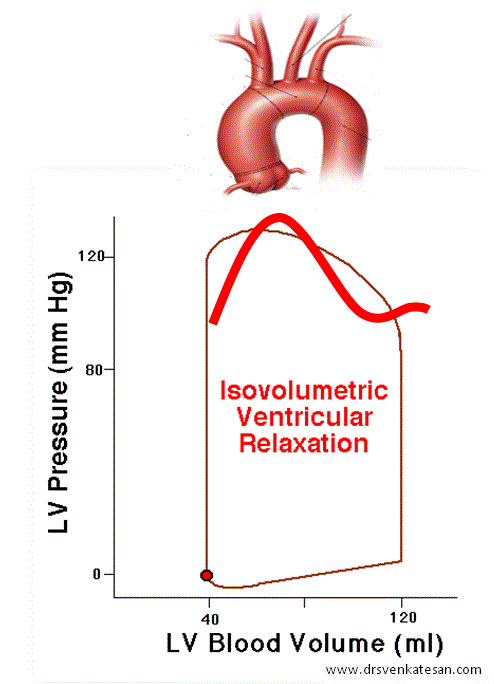
These loops tell us the secret  hemodynamic story of heart. Made  with 300 grams of mystery  muscle, the heart  handles about 100 ml of blood every beat, and successfully ejects around 70 ml into Aorta and Pulmonary artery * ·

108356heart_beating

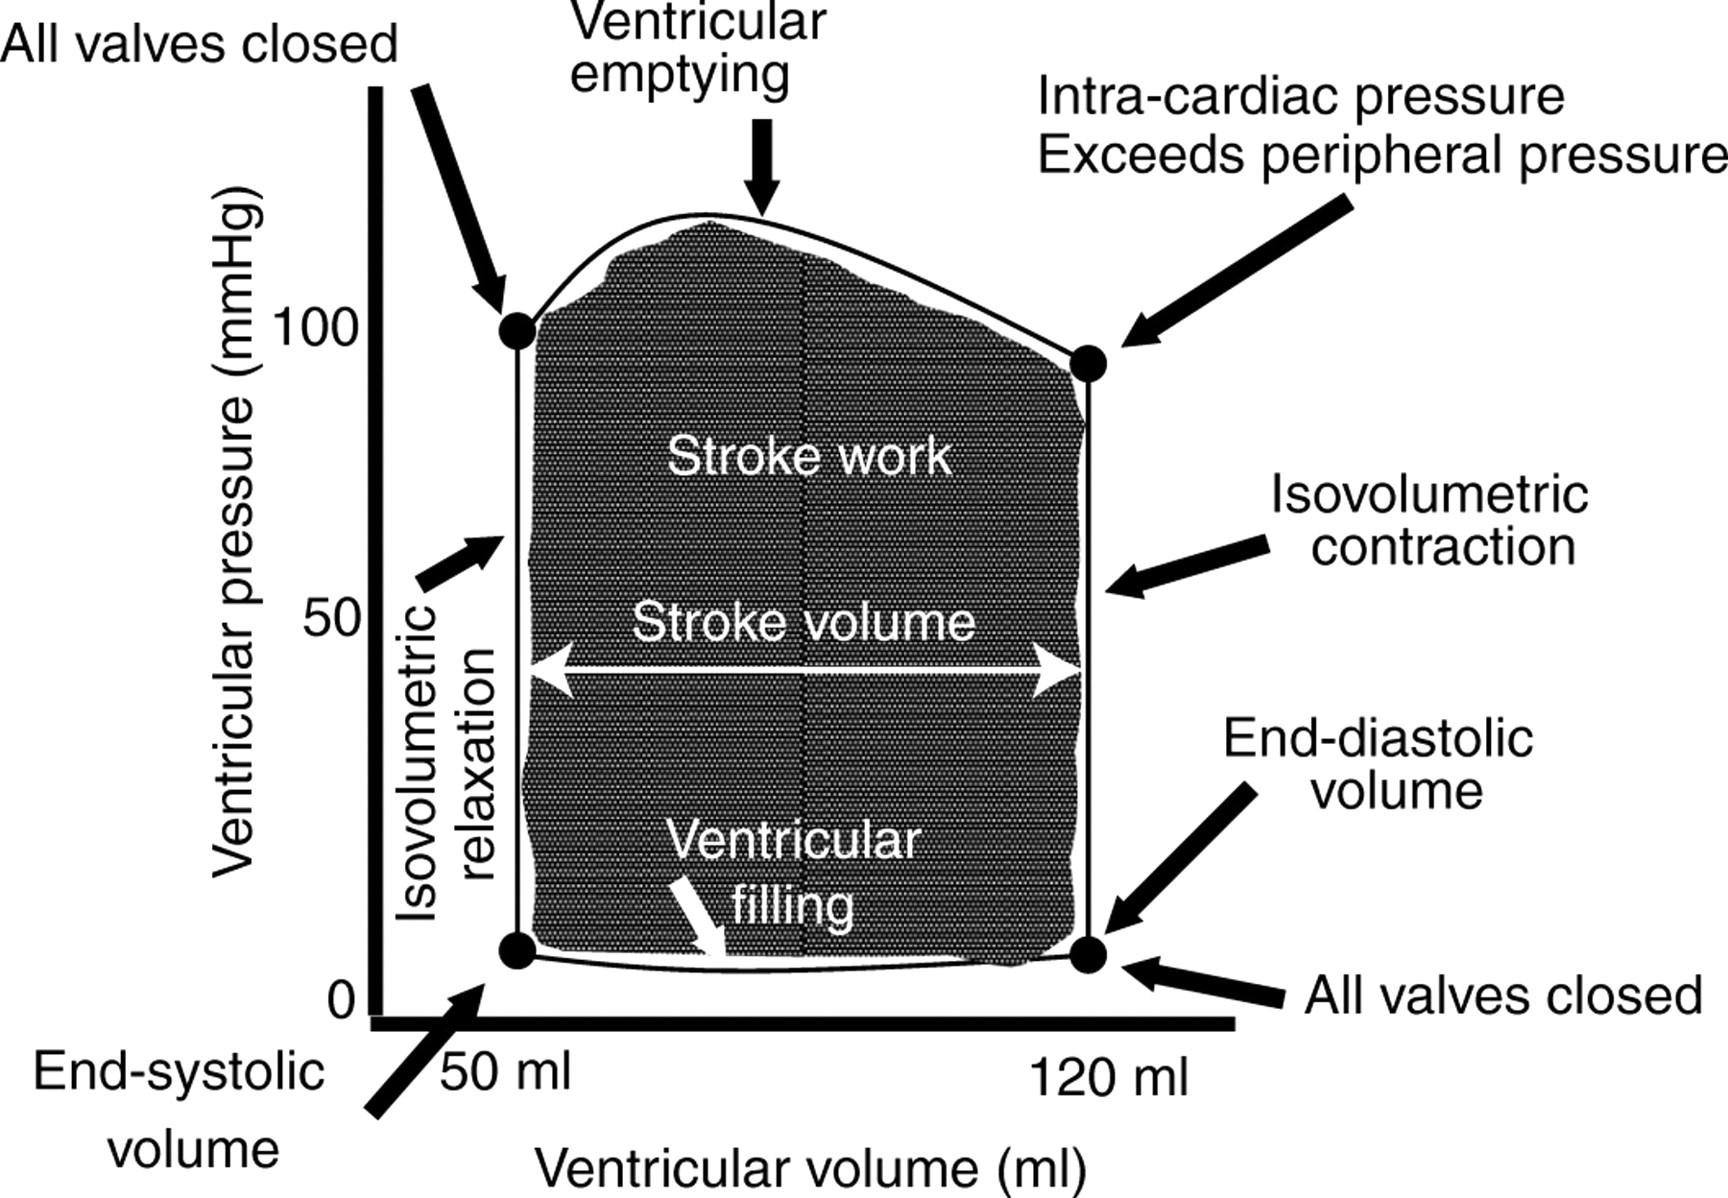
While doing this life sustaining job , It would seem the heart muscle  conducts a perfect, non stop, hemodynamic orchestra with 4 electro-mechanically coupled phases which is depicted as classical ventricular pressure volume  loop. Mind you, this loop is plotted from pressure volume data from a single heart beat and it can’t be time correlated with heart sounds or ECG as the two parameters loop around in the same time cycle.

Watch this animation , carefully and read the appearing annotation that come along with each phase.That should suffice to understand the basic. (For Audio version go the video link in the reference )

Modified from a clipping from Giphy.com.Original source of this Image is not located. Whoever has done this thanks and it’s a great attempt.(I have tried a fusion Image of doppler mitral Inflow in diastole and Aortic pressure curve during systole to bring PV loop an anatomical perspective.)

*Note: When we say PV loop it means about by LV by default . We do have seperate RV ,LA (even RA?) PV loops.

Is there clinical application for  PV loops ?

It may not have any direct use , but understanding  how a ventricle works in normal conditions or at distress especially during acute decompensations or after surgery  is vital. With modern gadgets like LV assist devices,  Impella used widely and to assess hemodynamic efficiency of transplanted (Very soon total artificial hearts) , PV loop analysis of both RV/LV will be critical.

Is there any simple Lab modality that can draw this Loop curve instantaneously ?

echocardiography lab methods for ventricular pressure volume loop

Very few companies make it . AdInstruments that make power lab monitors, enable us to visualise PV loops invasively .

Can we get PV loops non invasively by Echocardiography ?

Echocardiography  provide us both volume  and pressure data.With improving accuracy of data it should be possible to plot the loop manually with some effort. (Still , we can’t get pressure in all points of cardiac cycle )

I guess, sooner 3D volumetric machines with automated online doppler pressure data across the valves  can help us draw the ultimate LV functional  curve live on real time.If that happens cardiologists will be further enriched and hemodynamically enlightened !

Final message

The shape , size , timing and the slopes of this loop  givs us vital info about the functional aspects of ventricle. First one should understand the normal loop , then , we can dwell on the effects of acute and chronic lesions like regurgitations, cardiomyopathy ,cardiogenic shock etc.

Reference 

An excellent knwoledge base on the topic with a  video 

Dr. Richard E. Klabunde, PhD