Feeds:
Posts
Comments

Archive for the ‘Uncategorized’ Category

Great things happen in India nowadays  .Economy is growing    at  9% , the growth of  automobile industry is  fastest in the world. But in  scientific  research and development  it   has  been traditionally lagging behind . Things are set to change. The medical science , (If you want to call it as industry it is fine !)  especially  the imaging science is making rapid strides. The proliferation of  private and corporate hospitals and institutes   has helped us practice the latest .

Pulmonary atresia with VSD is a rare congenital disease where  there is partial or  total (chaotic  )pulmonary arterial blood supply .

When the pulmonary  artery becomes atretic , what will the lung do ?

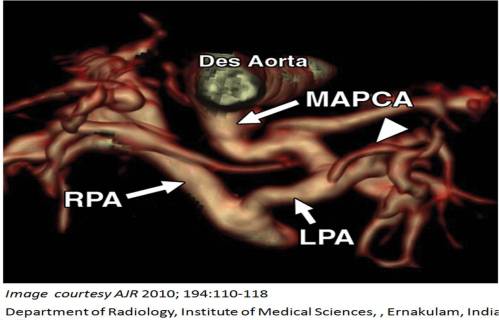
It has to get perfused somehow ! It tries to snatch the  blood from the aorta  in whatever  possible manner . Depending on the severity of pulmonary atresia  , there  can be  a total anomalous pulmonary  arterial supply (Type 4 ) .Here , few twigs directly originate  from Aorta, few from branches of  Aorta  and sometimes bilateral  PDA etc .These are collectively called major arotopulmonary collateral  (MAPCAS) .In fact differentiating a PDA from a MAPCA can be extremely difficult .(It has only academic purpose though !)

Hither to ,  visualising  the  MAPCAS was a  huge  task . Aortogram with selective cannulation of MAPCA  was  neccessary.Now,  with the advent of  MDCT we can get some stunning  images  of these collaterals non invasively.

Why is visualizing and delineating MAPCA anatomy important ?

This will facilitate the surgeon to plan  the  unification of pulmonary  arterial flow    and reenginnering the pulmonary circulation  (with or with  out  conduits)

Here is a rare  publication originating from India  in  American journal of radiology  . An  exclusive   article  with  CT scan  images of the  defect .

Amrita  Institute , from  the southern   Indian  state of  Kerala (  also known as God’s  own country )  is doing a phenomenal  cardiology  work  especially  in pediatric cardiology.

Three cheers to the team which published this  master piece . With the courtesy of   AJR the link to the article is placed here.
Read Full Post »

LVH is supposed to produce tall R waves . But , we know  often LVH is misdiagnosed as   myocardial infarction especially  anterior MI.  (With deep q waves*  in v1 to v3 and sometimes q in inferior leads as well)

Infarct tissue  is a  cluster of dead cells  , while  LVH is a bundle of live cells . How can the ECG produce similar changes  in both ?

One need to realise ,  ECG does not function  as  a tissue identifying  machine.  It’s job is to simply  tell which direction the current  is traveling with reference to the  recording electrode .

If it comes towards  the electrode ,  R  wave is recorded and  if it goes away Q is recorded.

In infarction it is obvious the dead cells  form a distinct electrically inert  window so that the  muscle  mass located in the opposite pole  (If viable ) will record  q waves.

In LVH  how the  direction of  current get reversed ?

We know,  cardiac muscle  is made  up of not only myocytes , it is enriched with, fibroblasts, interstitial cells, collagen and other extracellular matrix .These non contractile cells have little electrical energy to show off.  In physiological LVH there is  not much proliferation of interstitium . It simply  reflects hypertrophy of  individual contractile units. It robustly produce good quality electricity and the ECG inscribes a tall r waves

Causes of  physiological LVH include

  • Athletic heart
  • Many of the hypertensive patients
  • Early stages of Aortic stenosis
  • Any LVH due to increased loading conditions( In the initial stages )

Pathological LVH

Here  LVH  is predominately  due to  proliferation of fibroblasts  and interstitial cells  .This interferes with the alignment of sarcomeres of myocytes. When the  architecture of contractile units  are  altered ,  it finds difficult to generate good quality action potentials  . Since the ECG is the summation of action potentials  ,  it gets distorted  with local delay,   notch ,slur etc . Ultimately it many  cases q waves are inscribed .

Th  q waves ,  gets amplified by the fibrotic process which is  technically dead cells for the ECG machine at least !.

Note: Pathological LVH grows well with excellent nourishment from ACE gene dependent growth factors. In fact , who will develop pathological LVH  (and who will not  )  is  predetermined by our ancestral genes.  (Other wise called fate or destiny  !)

Conditions  causing pathological q waves

  • About 10% of  LVH due HT can manifest q waves
  • HOCM
  • Late stages of Aortic stenosis
  • Some cases of Diabetic HT combination
  • HT with CKD

* There is one more cause for q in LVH .This is technical .   As  the  heart rotates counterclockwise ,  septal activity instead of  recording a r wave  ,  merges  with the s wave mimicking q waves. In fact this could be very common cause for labeling LVH as MI.

Final message

Q waves are not sacred to diagnose MI.It can be generated  even by live myocytes  when it behaves like an  electrically dead ones.

Read Full Post »

Sharing and caring for  others  is the  unique human nature . Some believe this is  now gradually   becoming  rare in human domain ,   but still  found in plenty among  animal species. While modern human  likes to live independently  wants to stand on his own legs  our  biological system still  think differently .

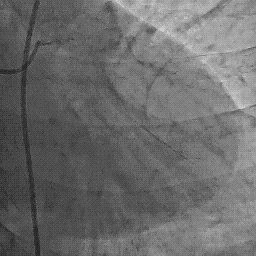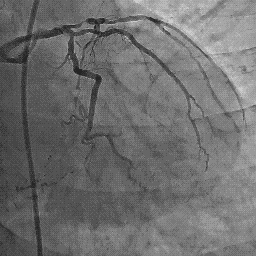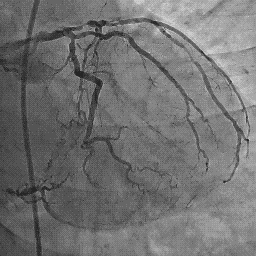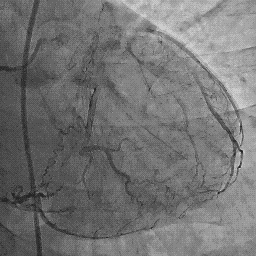
A 40-year-old man with diabetes and hypertension with class 3 angina had this angiogram

RCA to LAD collaterals

A different view

RCA to LAD in RAO caudal view

See , how a  pair of  human coronary arteries  mutually  help   their  colleague  at times of distress !

The astonishing observation is ,  the  RCA even as its suffering  with  a severe,   long segment disease it  helps out-of-the-way ,  with a long arm  of  support to  the entire LAD . While , the LCX reciprocates  the RCA by sending  thank you twigs to distal RCA

LCX sending reciprocating twigs to RCA

By the way , this patient was referred  for CABG after an   intense  debate in the cath meeting  .The argument ranged from medical management /PCI/CABG.

The key question were

  • How good is the collateral’s and what  are the chances of  graft flow  exceeding the collateral  blood flow ?
  • What is the effect of CABG on the existing collateral’s ?

Final message

Coronary arteries  has unique sense of sharing and friendship at times of vascular crises.

This is the fundamental basis for   coronary collateral circulation .

Read Full Post »

Heart is the first organ to differentiate in the fetus.The first heart beat begins on the 22nd day of fetal life ! . From that day , it’s function is linearly determine the   fetal growth  .It continues in the new-born,  infancy and  up to late child hood.

It is no surprise  then, to detect growth retardation in congenital heart disease. A proper evaluation begins right from fetal mass / birth weight estimation  .Motor and cognitive milestones should be assessed meticulously .

The pattern of growth affliction is  complex  and poorly understood.Few  working rules are  often taught in cardiology classrooms.

Caution : This is a too simplified version. Discerned readers should consult all sources cited here.

Acyanotic heart disease

ASD, VSD, PDA  tend to affect weight gain  more but generally do not affect height  much  . But, the onset of pulmonary  hypertension early in the course will severely  affect height as well.

Co arctation of  Aorta and other Aortic interruptive   diseases  can have a differential  affection of growth . (Upper part of body > Lower part)

Cyanotic heart disease

CHD  affects both height and weight proportionately. Cyanotic  heart disease with increased pulmonary blood flow  the overall survival is less ,  recurrent failure is common  and hence growth and development is more affected.

The mechanism of stunted  growth.

The often used terminology  ‘failure to thrive” , may not be attributed to heart disease per-se. It has to be multi factorial and  is related to  social well-being  ,  feeding habits , and mother’s effort  , interruptions due to co existing illness , effects of surgery  etc. Obviously these factors operate  more  in infants with increased pulmonary blood flow.

Effect  on cognitive function

Contrary  to the expectations  even chronic hypoxia and cyanosis has no compelling effects  on the child’s intelligence . Unless there is co existing  neurological defects severe compromise of cognition  is  uncommon.

However now we realise , brain development do  suffer   in hypoxic environment.In fact, the damage  to cognition could start right from the fetus .

New evidence is coming  up.

*Recurrent hypoxia spells and convulsions in TOF  can lead to reduced cognition

Is the normal  growth  and development   restored after complete correction of the disease by  cardiac surgery ?

The expected benefit is usually achieved  . The catch up occurs . But it is not guaranteed,   especially in  cyanotic heart disease. As , many times the  destined growth of a child   is  reprogrammed and  predetermined  in the fetus itself.


Link to a rare review article on the topic

References  on Growth impairment in congenital heart disease


R. L. Naeye, “Anatomic features of growth failure in congenital heart disease,” Pediatrics, vol. 39, no. 3, pp. 433–440, 1967.

A. Mehrizi and A. Drash, “Birth weight of infants with cyanotic and acyanotic congenital malformations of the heart,” Journal of Pediatrics, vol. 59, no. 5, pp. 715–718, 1961.

R. J. Levy, A. Rosenthal, D. C. Fyler, and A. S. Nadas, “Birthweight of infants with congenital heart disease,” American Journal of Diseases of Children, vol. 132, no. 3, pp. 249–254, 1978.

H. H. Kramer, H. J. Trampisch, S. Rammos, and A. Giese, “Birth weight of children with congenital heart disease,” European Journal of Pediatrics, vol. 149, no. 11, pp. 752–757, 1990.

Read Full Post »

Mitral regurgitation jets can take many shapes

  • Symmetrical
  • Central
  • Eccentric

The direction of the jet depends upon

  • The angle of co-optation
  • The  plane of  orientation of regurgitant  orifice . It  can be entirely off track with  physiological  mitral orifice .
  • Degree of prolapse or shortening /subvalvular  fusion.
  • Flail valve tips can guide the jet selectively into anterior/superior  or posterior aspect of LV

Rheumatic mitral valve showing poor leaflet co-optation.Patient is having significant tachycardia


Perpendicular 90 degree MR jets


In rheumatic heart disease  eccentric jets are more common. In dilated cardiomyopathy MR jets are often symmetrical and central as the pathology is annular dilatation.

What are  the significance of eccentric MR jets ?

  • Anterior jets clinically mimic aortic stenosis as the murmur is  often well conducted to neck
  • Murmurs of  posterior jets well conduct to axilla .
  • Eccentric jets are often acute and compromise hemodynamics
  • Suspect early infective endocarditis.Carefully look for vegetation.
  • Eccentric jets make it difficult /risky  for PTMC (Note : In Mitral stenosis  +  grade 1  MR   with central jets  one can safely do PTMC)
  • Severe eccentric jets can flood one of the pulmonary veins and result in unilateral or regional pulmonary hypertension or even lobar /segmental pulmonary edema

Read Full Post »

It is well  recognised for STEMI  to get aborted   spontaneously or through intervention.

Can a glamorous procedure like  Primary PCI be redundant ?

Yes of course . This paper,  is about how a planned  Primary PCI  can go awry  . . . Presented in the Annual scientific sessions of cardiological society of India Kolkatta December 2010.

Down load full presentation  in PDF format (primary_pci_)

Summary of the presentation

ABORTED  AND     ABANDONED    PRIMARY PCI

S.Venkatesan  G.Gnanavelu.R.Subramanian .Geetha Subramaninan

Madras Medical College. Chennai

Primary PCI has become the  standard of care  for acute STEMI in all  those eligible patients. Apart from the individual & institutional expertise ,the  key  to success  lies in  expediting   the symptom to balloon time to less than an hour.

Even though  STEMI   is characterized  by  acute total obstruction , it  is also a fact during this critical time window , a less recognised   positive  phenomenon takes place within the  ill fated coronary artery. Intrinsic fibrinolytic activity gets activiated and begins to take on the thrombus head on .It should be recalled this is the  earliest intervention in STEMI by natural forces , with zero time window . The power of this natural lytic process has  never  been easy to predict and quantiate . But  we  have  often realised  such a phenomenon do occur often and  is referred  by  various  terminologies like spontaneuous  thrombolyis, aboted MI etc .The exact incidence  is not estimated .In this era of  primary PCI we have found a new opportunity to confirm  this concept.

It has been  observed during  primary PCI ,  an occasional patient  may  have  either  a totally  patent IRA  or a minimal &  insignificant lesion  like luminal irregularity .This has  subsequently led on to cancellation of the procedure .We report our experience with  two patients with  this particular situation .One patient with IWMI with a time window   of  6hours had a totally patent  RCA.  Even , the luminal irregularities were difficult to locate .The other patient had anterior MI with ongoing ischemic pain.He was taken up for primary PCI.The initial angiogram  showed a total mid LAD  obstruction . As soon as the  guidewire reached the thrombotic lesion the  artery opened up   wth a TIMI  3 flow .There was no residual lesion or thrombus  noted. Both of the above  patients  were  young , smokers . 2b 3a antagonists were not administered. We infered, both had thrombotic STEMI and   presumed  to  had either spontaneous reperfusion , or  reperfusion assisted by dye injection & guidewire manipulation. They were  shifted out of cath lab with a new code of aborted primary PCI and  were discharged with normal LV function .It need  to be  realised here, a   distinction must me made between  aborted PCI  and   abandoned or failed  primary PCI  as  the later  connote a negative outcome. The  causes for abandoning  primary PCI are due to complex  lesions like bifurcation /Trifurcation lesions , triple vessel disease  with difficulty in identifying culprit lesions.A  Primary PCI is  considered failed  when the  IRA patency  is not accomplished or  failure to  sustain myocardial flow inspite of  IRA patency (No-Reflow) . These patients may end up in CABG or occasionally fall back on  thrombolysis  which was considered a inferior modality just few hours earlier !

.                                         We conclude , in the management of STEMI ,  primary PCI once contemplated need not always reach it’s  logical conclusion. There are situations  it can  get  aborted or abandoned  at various levels . Aborted  primary PCI  due to spontaneous  lysis though uncommon ,  can be a therapeutically and financially rewarding concept for the patient  and  physician .

Read Full Post »

Squatting is an excellent hemodynamic adaptation in patients with TOF. Children with TOF assume this posture   in  a natural and effortless manner . For years cardiologists are fascinated by this maneuver  and the mechanism by which it gives relief  to those patients with TOF.

Now , we have realised  this posture  has a new diagnostic role in echocardiography ! This paper was presented in the recently concluded  Annual scientific sessions of cardiological society of India held in Kolkatta December 2010

Download  the full   presentation in PDF  format  (  Squat Echo)

Read Full Post »

Myocardial scars remain forever ! It forms the focus for many chronic  ventricular tachycardias following MI. A healed scar is not often benign . It blocks the electrical wavelets and deflects into multiple directions some of them may reenter and form re-entrant VT .

This scar fascinated  one man from Holland -De Bakker . . . his quest for myocardial  scars produced this excellent paper .

No one  can do  such a meticulous work  today !

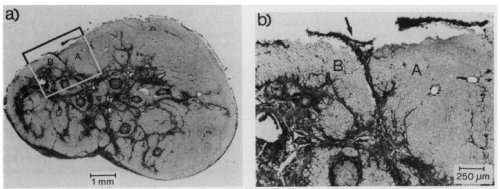
He did a extraordinary  study with the scarred  papillary muscle of infarcted myocardium . It included stunning histo-pathological analysis .He found for the first time , how the scar  even though mechanically idle conducts in multiple directions that precipitate the arrhythmias


We need to classify myocardial scar for understanding better the VT circuits. The newer imaging like Carto system can help us in imaging the ventricular scars.


A rough approach for myocardial scar classification could be .

Location

  • Epicardial
  • Endocardial
  • Transmural

Combined

  • Predominantly endocardial
  • Predominately epicardial

Septal scars

Anterior

Apical

Posterior scars

*With or with out Pap Muscle

Based on thickness and volume**

Small< 2CC  >5CC

Intermediate up to 10cc

Large >20cc

**Scar volume

Based on electro-physiological properties

  • Inert
  • Inducible
  • Spontaneous with clinical VT

Based on Metabolic activity

PET matched

Mismatched

Scars with reference to vascularity

  • Vascularised scars
  • Avascular scars
  • Revascularised scars

Further modification of the scheme by the readers are welcome


Clinical implication of scars apart from arrhythmias ?

CRT lead positioning


Read Full Post »

Coronary circulation is an enigma . This is true even after 50 years of coronary angiography.  What we visualise  in CAG is  only a  fraction ,  when  compared with what we do not see !  The intricacies of  coronary collateral circulation and micro circulation is comparable only to the  ultimate force of   invisibility “The  God ”

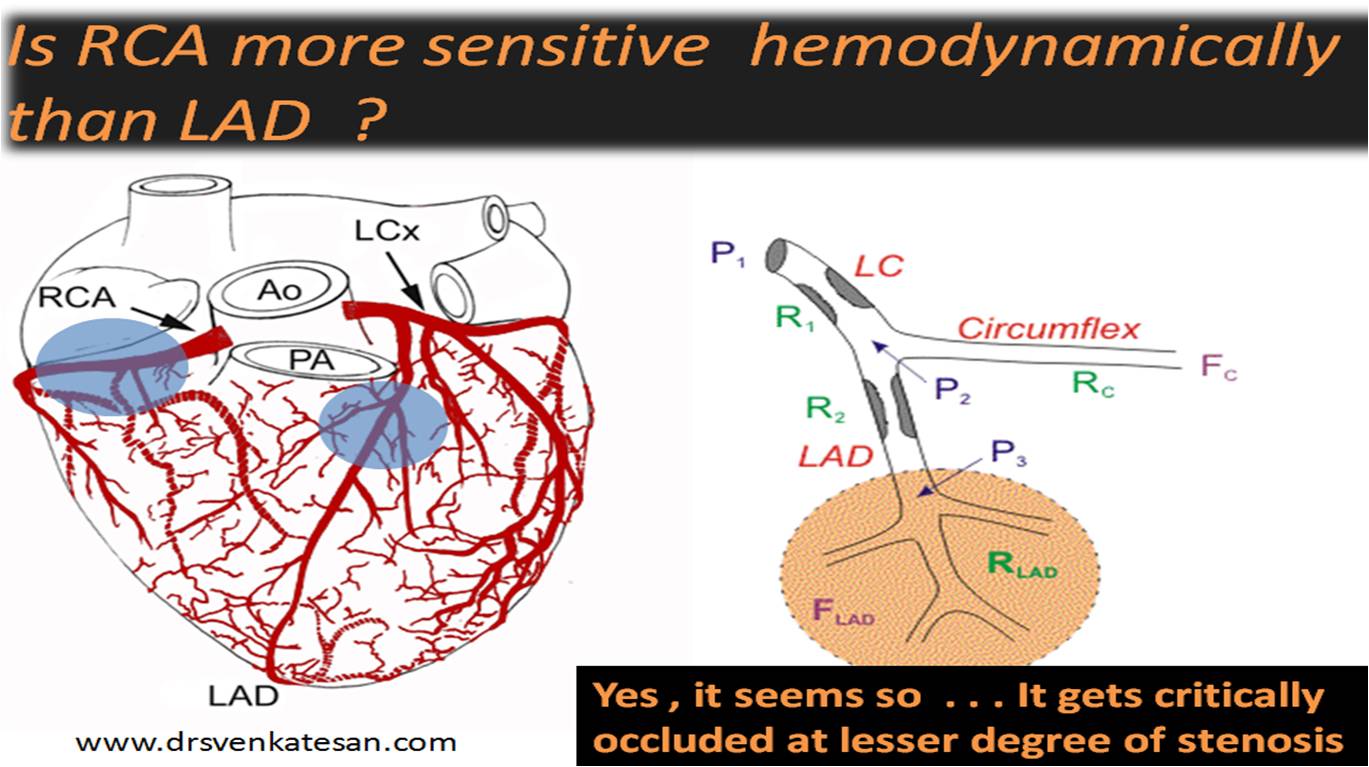
But , we will never ever believe what we do not see  . . .  but we have to accept the following  fact . How is it possible   for  some of the coronary  arteries  to maintain  a near normal blood flow from a donor (Contralateral ) coronary  artery  in spite of  100 % occlusion ?  Is it not common to see TIMI 3 flow even with 99 % occlusion .(Link to related article in  this blog  and  video ) . This is because the coronary  vascular bed has an extraordinary capacity to drop its distal pressure to negate the effects of obstruction.

Does the distal vascular bed anatomy and physiology same in RCA and LCA ?

We presume it so . The problem in medical science  is , these   presumptions  often  become  facts in due course  ! Now we have (It is in fact 30 years old !) RCA has lesser ability to withstand the stress  of stenosis than LCA.

The prime reason for this observed difference could be the LCA has a well developed microvascular bed which can reduce the distal coronary resistance .(Again , this is my  presumption  . . . !!! )

This interesting article was published in Circulation 1980 .


Read Full Post »

Great people  do not boast  . While there are thousands of hyped up publications in cardiology ,

This one form Qatar excels , which  I  stumbled upon recently  contains very useful information about wide ranging issues in cardiology .

Let us congratulate the   Hamad medical corporation for  their unique  academic vision  .

http://www.hmc.org.qa/hmc/heartviews/ARCHIVES/ARCHIVES.HTM

Read Full Post »

« Newer Posts - Older Posts »