I don’t know the answer, rather I am afraid to answer that question.
Read this article , that may help find answer to this forbidden question.

I don’t know the answer, rather I am afraid to answer that question.
Read this article , that may help find answer to this forbidden question.
Posted in Uncategorized | Tagged ethics in modern medicine | Leave a Comment »
100% occlusion of a coronary artery result in STEMI.This includes both thrombus and mechanical component .We are very much blinded till we touch , feel and see the lesion with a wire or IVUS to quantify the mechanical component’s contribution in the genesis of STEMI.It is generally believed (True as well ) thrombus is the chief culprit .It can even be 100 % thrombotic STEMI with just a residual endothelial erosion and hence
zero mechanical component .However , the point of contention that non flow limiting lesion is more likely to cause a thrombotic STEMI than a flow liming
lesion seems to be biased and misunderstood scientific fact .
What happens once 100 % occlusion take place ?
Sudden occlusion , is expected to evoke a strong fire fighting response within the coronary artery.The immediate reaction is the activation of tissue plasminogen system. In this aftermath few succumb . ( Re-perfusion arrhythmia generated as VF ) .The TPA system activates and tries to lyse the clot.The volume , morphology, attachment, content of thrombus , and the elasticity of fibrin mesh , location of platelet core would determine the life and dissolvablity of thrombus. Even a trickle flow can keep the distal vessel patent .(Please note a timely TIMI 2 flow can be a greater achievement than a delayed TIMI 3 flow !)
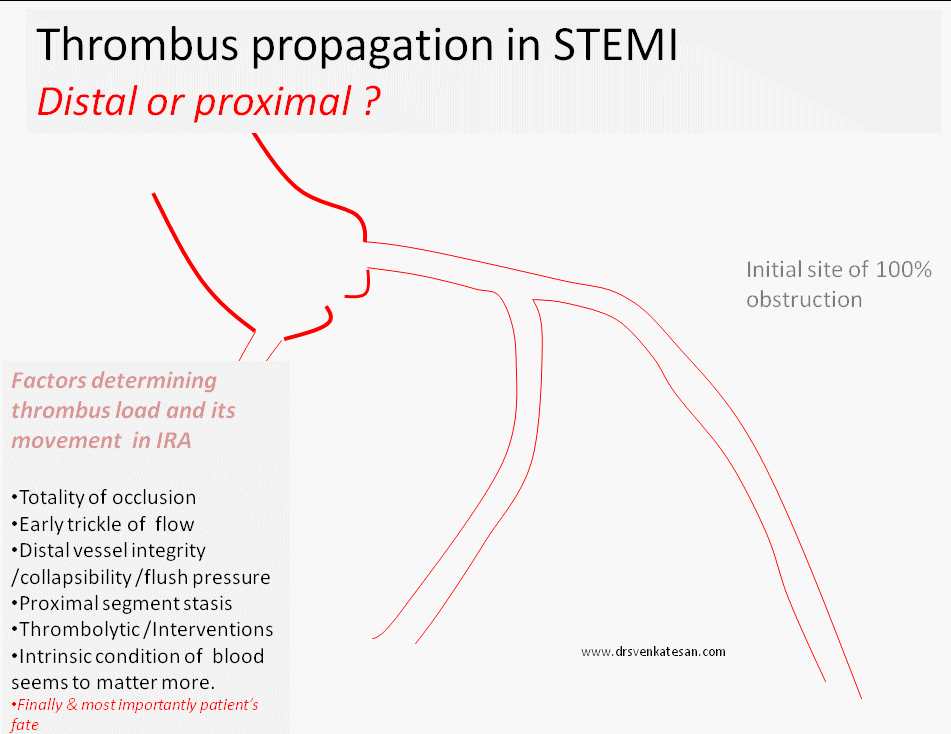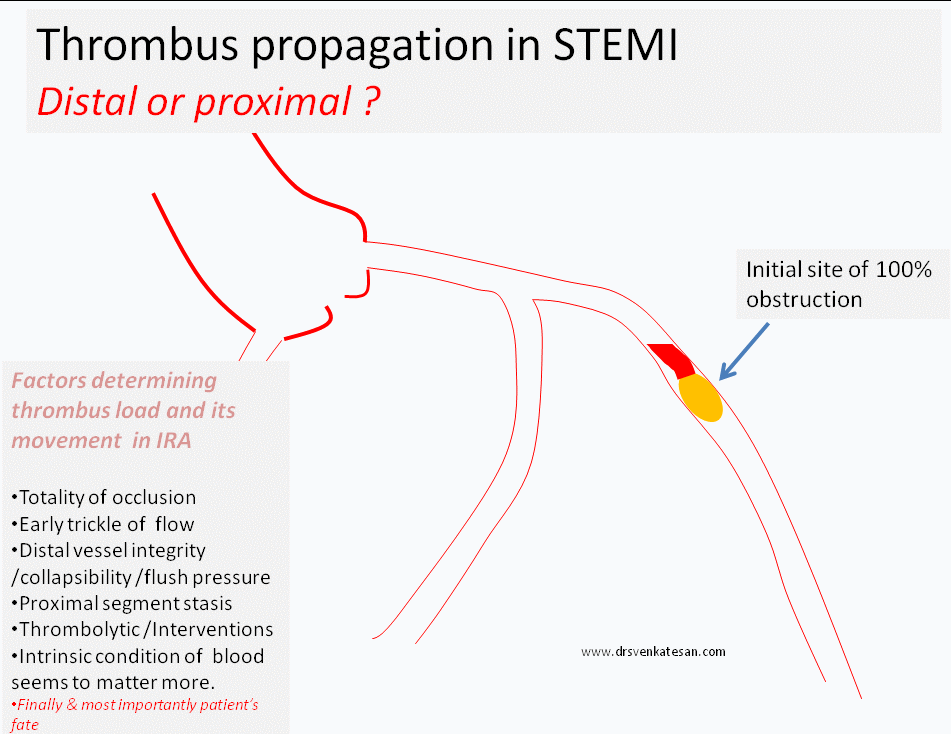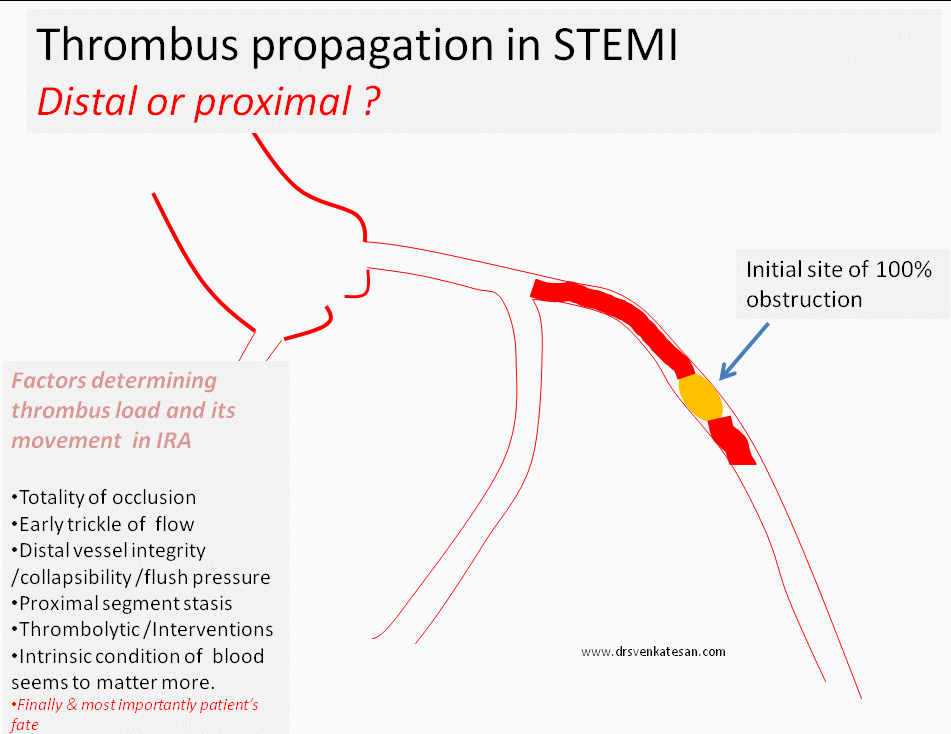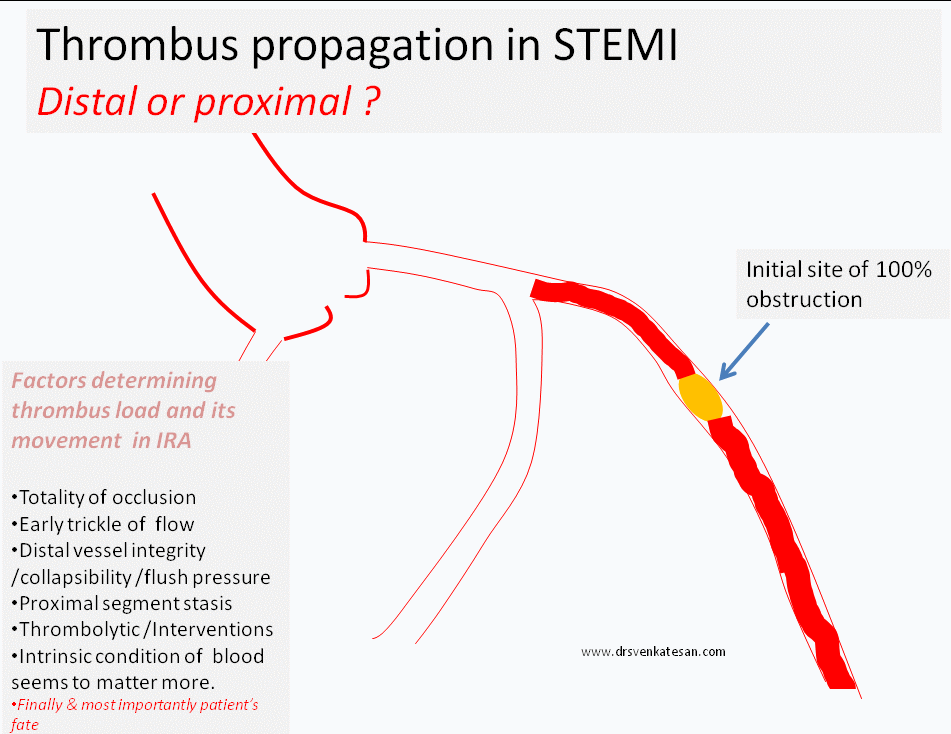
What happens to the natural history of thrombus in STEMI ?
Thrombus formed over the culprit lesion can follow any of the following course
Factors determining thrombus migration
The interaction between the hemodynamic forces that push a thrombus distally and hemo-rheological factors that promote fresh proximal thrombus formation are poorly understood. The altered intra-coronary milieu with a fissured plaque covered by platelet vs RBC / fibrin core, totally of obstruction, reperfusing forces , re-exposure of raw areas and the distal vessel integrity all matters.
While, logic would tell us, thrombus more often migrates distally assisted by the direction of blood flow, an opposite concept also seeks attention , ie since the blood flow is sluggish in the proximal (to obstruction site )more thrombus forms in segments proximal to obstruction.
(In fact, its presumed in any acute massive proximal LAD STEMI , it takes hardly few minutes for the thrombus to queue up proximaly and clog the bifurcation and spill over to LCX or even reach left main and result in instant mechanical death.)
What is the significance of length and longitudinal resistance of the thrombotic segment in STEMI ?
If thrombus is the culprit let us get rid of it , this concept looks nice on paper , but still we don’t know why thrombus aspiration in STEMI is not consistently useful. We also know little about the length of the thrombotic segment .When a guide wire is passed over a STEMI ATO it may cross smoothly like “cutting a slice of butter” in some , while in few we struggle and end up with severe no-reflow inspite of great efforts .Why ?
What is the Impact of distal collateral flow in flushing fresh thrombus ?
The efficacy of collateral flow in salvaging myocardium is underestimated. Distal vessel flow if perfused partially by acute collaterals the thrombus load is not only less it’s soft and fail to get organised early that would help cross the lesion easily.
Posted in acute coroanry syndrome, STEMI, STEMI -Managment | Tagged device migration, distal vs proxial migration of thrombus, FAILED THROMOLYSIS, primary pci total study, thrombus stemi | Leave a Comment »
Answer : I guess all mechanisms contribute.Though E appears unlikely, its backed by evidence (Ref 5)
Balloon pericardiotomy is done as a drainage procedure in recurrent pericardial effusion. It is actually a replication of surgical pericardial window by Interventional cardiologist.The window not only drains the effusion , it also act as a continuous drain. Though the benefits are real (Pericardial fluid is shunted away from the pericardial space) the exact mechanism of its benefit is not clear .
By concept , the catheter and balloon should not cross the pleural space , (As pneumothorax may ensue) but still pleural effusion is a common consequence of this procedure .How is this possible ? One probable explanation is, the pleural space has some hidden communication with pericardial space .The other possibility is that, balloon creates virtual tissue channels in the para-cardiac spaces of mediastinum .The extra-cardiac lymphatics does the drainage job without true shunting pericardial space into the pleural space..
There is an article from Annals of thoracic surgery which specifically looked into the mechanism of benefit of surgical pericardial window and came to a surprise conclusion, ie, it is not the continuous drainage that keeps the space dry , rather it is likely the window somehow obliterates the pericardial space permanently.(Sugimoto 1990,Annals of thoracic surgery )
Future Innovation : A technical add-on to balloon pericarditomy could be , delivering a covered stent across the pericardial space into peritoneal space like a VP shunt done by Neurosurgeons.(If no body has done this , Can I claim the patency for this !)
The procedure

Image used from Daniel A. Jones & Ajay K. Jain, Journal of thoracic Oncology , 2011
Risk of procedure
The procedure carries a definite risk especially if done in an emergency fashion. The aim of procedure is two fold one to drain pericardial effusion second to prevent recurrence of effusion .Since procedure carries considerable risk its to be performed only in malignant effusion that are documented to be recurrent.
Surgical vs Balloon window and other alternatives
Surgical window creation is well known procedure , ever since Palacios (Ref 1) in 1991 described this per cutaneous approach as an alternative to surgery has become less popular. The risk of anesthesia and co-morbidity makes balloon pericardiotomy attractive. But surgical window creation still may have a role. A video assisted pericardiotomy by thoracoscopy is also possible .Another option is injecting sclerosing agents into pericardial space .This time tested simple modality probably requires more attention.
Need for subsequent pleural tapping
It should be realised this procedure may just shift the fluid from pericardium to pleural space. Some of them become significant effusion that requires pleural space drainage.
Concern of risk of dissemination of malignancy
Its a real issue , there has been instances of accelerated death after the procedure. Hence this procedure is a trade-of between patient comfort and quality of life with a potential risk of dissemination impacting the longevity of life .
Posted in cardiac tamponade, Cardiology -Therapeutic dilemma, Pericardium | Tagged balloon pericardiotomy, percutaneous baloon pericardiocentesis |
The field of cardiology has seen great men over the centuries. Few women have permanently stamped their presence in that history .Jane Somerville can be termed mother of pediatric cardiology along with Maude Abbott She has a fascinating life history , having worked in Royal Brompton , Imperial and Guys London.She was mentored by pioneers like Paul wood , Blalock and others .She is primarily interested in the pediatric cardiology especially congenital heart surgeries .The classification of pulmonary atresia with VSD goes with her name.

Dr. Jane Somerville : British cardiologist , (b-1933 )
She carries the credit of starting the Pediatric cardiology world congress in 1990 ,is the founder of GUCH (Grown up children with congenital heart disease.) .
Here is a rare interview from he to Dr Robert Califf for Heart.org. For those,who like to have a glimpse of cardiology in its vintage times , don’t miss it.Dr Jane addresses the past treasures , explores specific issues of facing pediatric cardiology and frank expression about the issues of women being a cardiologist in a man’s world.
She has a foundation in her name that helps the children and adults with congenital heart disease.

Reference
The landmark paper in BHJ 1970

Posted in congenital heart disease, history of cardiology | Tagged history of cardiology, Jane somerville, pulmonary atresia jane somerville | Leave a Comment »
“Men are from Mars , and Women are from Venus ” . . . Do you agree ?
Many probably witness the much talked differential behavior among the gender every day. Its argued , men take more risk in life ( often senseless !) , some go to the extreme to suggest Men are Idiots and decorate them with a provocative title MIT (Men Idiot Theory ) (Mcpherson 2011).Risk taking is important in life, but at what cost ? Does women (Who are caring by nature ) help themselves and the society by less risk taking behavior ?
I stumbled upon this rare piece of writing from BMJ which would demand in depth analysis into this gender phenomenon based on evolutionary biology and genetics.
This article concludes, Yes, men . . . indeed tend to take some foolish risks in various life situations that result in potential harm.

What is the influence of MIT on medical profession and patient outcome ?
Now , Iam compelled to ask a hypothetical question .Does women medical professionals take less aggressive stance and low risk taking behavior ?
If it’s true, It may have some striking advantage too.
Reference
1.Harris CR, Jenkins M, Glaser D. Gender differences in risk assessment: why do women take fewer risks than men? Judgm Decis Mak2006;1(1): p. 48-63.
2.Eckel CC, Grossman PJ. Men, women and risk aversion: experimental evidence. In: Plott CR, Smith VL, eds. Handbook of experimental economics results. Vol 1. North-Holland, 2008:1061-73.
3.McPherson J. Women are from Venus, men are idiots. Andrews McMeel, 2011
4.Northcutt W. The Darwin Awards: The official Darwin Awards: 180 bizarre true stories of how dumb humans have met their maker. Orion, 2004.
Posted in bio ethics, Gender issues in medicine, Hippocratic oath, history of cardiology, Histroy of medicine, medical quotes, Wintage cardiology | Tagged medical ethics gender issues | 1 Comment »

Posted in Uncategorized | Tagged evidence based medicine, future of medicine, inappropriate scientific growth, medical education, medical ethics | 2 Comments »
Dizzines , giddiness , light headedness , fear of fall or true fall (Syncope) are the most common symptoms beyond middle age .They usually end up with consulting physicians , neurologists and cardiologists .Cervical disc is commonly blamed for this.While all these symptoms can be a manifestation of cervical disc , true syncope seems to be rare with cervical spinal disorder.
 Why true is syncope rare with cervical spinal narrowing ?
There is a fundamental ignorance here. We are not yet clear whether giddiness /dizziness is neural or vascular .(Or combinations of both ) in cervical spinal disease.
Many of the patients experience momentary unsteadiness and feel like falling but very rarely end up in a fall or syncope.By definition syncope requires global transient hypoperfusion of brain to trigger a fall .
Cervical canal carries only the vertebral artery .Both internal carotids are no where near the spine. So, however severe the vascular compromise within the cervical canal , syncope is unlikely as anterior cerebral circulation compensates at the level of circle of Willis. Is that the correct way of reasoning ? Unilateral vertebral compromise rarely matters as other side takes care.It is very unlikely both vertebral artery get compromised by cervical spinal spurs simultaneously.
How many seconds of vascular compromise is required to produce syncope ?
Brain seems to be a funny and sensitive organ .In erect posture it is very sensitive. It reacts in a fraction of time for any transient reduction of blood flow.The same cardiac events which can cause symptoms of impending syncope in erect posture is quiet comfortably tackled in recumbent posture .
In erect posture , blood pressure need to much higher to get it pumped above the heart against the gravity. Though , it seems absolute blood pressure and cerebral perfusion that matters, there is something more we are missing. The brain-stem -vestibular system perceives differently when a recumbent person develop cerebral ischemia than when he is erect . The reflex circuit that activates on/off switch for abrubt loss generalised muscular tone is not yet been identified .
It is a biologically heartening irony that syncope is a natural counter mechanism by which the organism assumes instant recumbent position to maintain perfusion of brain .A fall promptly does this.(Ofcourse with a risk of Injury )
We think more than 3 second pause will initiate a syncope circuit .But it is not a fixed number. Some can tolerate up to 5sec or even more especially in lying posture.
Final message
Syncope , as such in isolated cervical spondylosis is rare even though it can potentially interfere with the vertebro basilar system .Why the vascular compromise almost always fall short of syncope and end up with just momentry unsteadiness is not clear.
Further queries to be addressed
Is dizziness, giddiness , presyncope are vascular or neural event?
Can vertigo occur with cervival spine disease ?
Posted in Syncope | Tagged cervical vertigo, mechansim of syncope in cervical spondylosis, syncope evaluation, syncope in neck compression | Leave a Comment »

Posted in acute coronary syndrome, atherosclerosis, platelet function | Tagged platelet adhesion and aggrgation and fatty meal briyani, platelet stickyness and dietery fat, platlet anf fat ldl and triglycerides, tgl mediated platlet aggregation | Leave a Comment »
What are the mechanisms of cyanosis in cyanotic heart disease ?
Most of my fellows have difficulty in answering this question. (It is not the lack of knowledge though !) In my view ,cyanosis can occur , by six different modes
* Essentially Atrial admixture is more complete than when it happens at ventricular or great vessel level
For advanced readers only
Now, is it possible for “Net” left to right shunt to result in cyanosis ?
Yes*.Very much possible. The bulk of this group is referred to as admixture lesions with certain caveats.There should be an obligatory mixing without contribution from RVOT obstruction or raised PVR( *Please note theoretically admixture can either be right to left or left to right shunt )
All pure admixture lesions are in fact net left to right shunts. (TAPVC, Single ventricle , Common atrium , Common AV canal ,Truncus, ) This is the group we have been traditionally calling cyanosis with increased pulmonary flow.
Its may also to be noted with surprise some admixture lesions often has less intense cyanosis than other forms as long as pulmonary blood flow is normal and the lung does its job perfectly .
*Please note Isolated classical left to right shunts , ASD, VSD, PDA can never cause significant cyanosis unless there is reversal of flow .However ,many Eisenmenger physiology show net Left to right shunting only ( 1.2-1.5 : 1 or so ) but with a definite right to left component .What we call as typically bi-directional shunt .
How can cyanosis be minimal even in some cases of single ventricle ?
Is single ventricle with PS admixture lesion or TOF physiology ?
Though single ventricle in isolation is an admixture lesion, when it has associated RVOT obstruction it ceases to be admixture by definition as mixing is augmented by the obstruction rather than by simple mixing.The complexity could be understood in certain situations where admixture lesions like common AV canal go for raised PVR .Here the various quantum of contribution to cyanosis is mind boggling. (Original admixture, augmented by RVOT resistance, differential mixing at atrial and ventricular level , hypoxia at lung level due micro pulmonary AV fistulas in grade 4 heath Edwards etc )
Role of streaming in Admixture lesions
Streaming is selective flow of venous blood into PA and arterial blood into Aorta even in the presence of large septal defects. Favorable streaming implies good systemic saturation. Unfavorable streaming would mean PA saturation more than aorta.(It should be noted streaming and good admixture don’t go together. If good admixture has happened there can’t be any streaming and vice versa)
Streaming is common in which situations?
Inspite of absence of IVS, streaming has been noted in some cases of single ventricle with minimal cyanosis with good saturation in Aorta.
Streaming in TAPVC has some unique features.
Fetal circulation has certain preformed pathways. IVC blood deflects to LA through ASD/PFO .SVC blood preferentially enter RV-PA. In Infradiaphragmatic TAPVC where it drains into IVC highly saturated PV blood may stream into LA thorough ASD and reach LV nd result in higher Aortic saturation.(This is in contrast the classical type of TAPVC draining into RA with little favorable streaming and hence O2 saturation equilibrates between PA/Aorta.)
In Supra cardiac TAPVC that drains into SVC or coronary sinus the streaming is unfavorable as it may preferentially cross tricuspid valve and enter PA making the saturation higher than Aorta.
Streaming is less common in which lesions ?
In common atrium and TAPVC draining into RA streaming is less common.In tricuspid atresia streaming is almost impossible as TV is non existent and this ensures complete mixing in the atria and hence cyanosis is likely to be severe.
Can TOF behave like an admixture lesions ?
Technically yes.If the RVOT obstruction is minimal ,(What was called then as pink Fallot ) We haven’t understood this entity properly for so long. Atleast I was baffled to read when J.K Perloff mentioned in his book during my DM fellowship days, that TOF can manifest with predominant left to right shunt with little or absent cyanosis.
The aortic override in TOF facilitated by large malaligned VSD make it a sort of admixture situation as RVOT resistance is too little to offer any resistance, (rather it welcomes more blood from left side ! ) So , should we call it simple VSD physiology , admixture physiology or just acyanotic forms of TOF ?)
Key points
Though admixure lesions are discussed separately , bulk of them actually represent cyanosis with increased pulmonary blood flow situations.
The net pulmonary blood flow is much more important than the quantum of admixture in determining the degree cyanosis
Finally , one should appreciate there can be combination admixture lesions with obstructive RVOT components . (Tricupid atresia+Pulmonary stenois )
Further reading
An excellent review article on this rare topic of admixture physiology
Posted in admixture lesions in cyanotic heart disease, cardiology -congenital heart disease, Tetrology of Fallot | Tagged admixture lesions in congenital heart disease, can left to right shunt cause cyanosis ?, mechansim of cyanosis, mechansim of cyanotic heart disease, what is admixture lesion | Leave a Comment »
On this special day , wishing all the readers and followers of this blog an energetic, creative , insightful and of-course a happy new year 2016 !
Just wanted to share the 2015 annual report of this site with the readers.

Posted in Uncategorized | Tagged 2015 annual report dr s venkatesan | 1 Comment »




 Dr.S.Venkatesan MD
