Feeds:
Posts
Comments

Posts Tagged ‘nstemi’

Localising the infarct-related artery (IRA) In NSTEMI , when there is multi-vessel coronary artery disease (CAD) is a classic clinical dilemma. Because NSTEMI lacks the clear, localising markers as in STEMI, identifying the “culprit” among multiple chronic blockages requires a more careful approach. It requires combined analysis of electrocardiographic clues , Echocardiographic WMA, angiographic analysis, and finally as a last resort intracoronary Imaging. Note : In UA,without NSTEMI it can be called as ARA-Angina related artery.
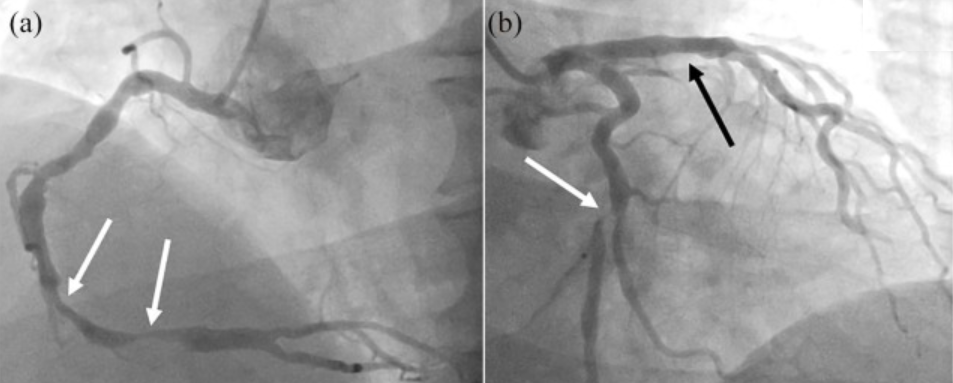
Image source : Baumann et al. Ther Adv Chronic Dis. 2020 Jul 1;11:2040622320938527

A meticulous review of the invasive coronary angiogram (ICA) will identify the culprit lesion in the majority of cases. Look for these specific features

  • Plaque Morphology: Eccentric , hazy lesions, irregular borders, or filling defects indicative of an intraluminal thrombus
  • Lesion Ulceration: Look for ulcerated edges, aneurysmal segments, or evidence of a dissection flap. Any vessel showing TIMI-1 or TIMI-2 flow, or prolonged contrast stasis during washout suggest microvascular plugging downstream from a fresh rupture.

ECG -ECHO correlation of WMA is the key

  • Wall motion defect correlation: Matching the distribution territory of the suspected culprit vessel LADcs LCX or RCA can be most useful . Still extensive collaterals can prevents us, to make a rule of thumb
  • Typical patterns like Wellens can help localise the IRA. Transient ST-depressions or deep T-wave inversions
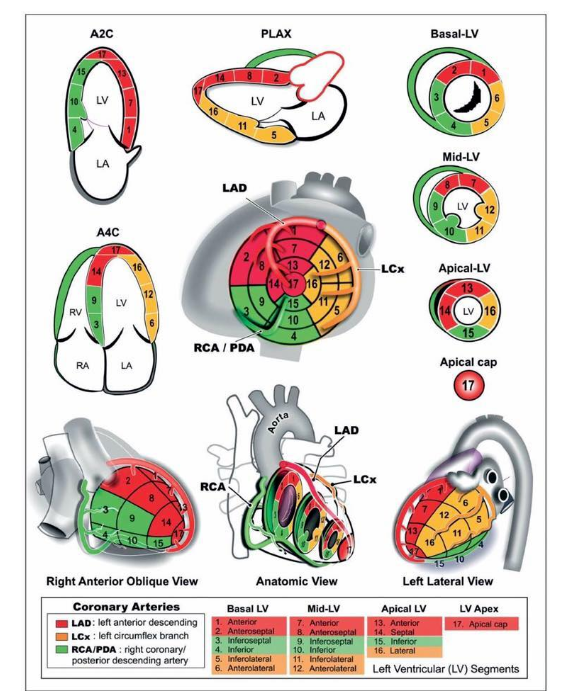
The most important illustration in coronary artery disease

Note* WMA can be deceptive as well, due to old MI, remote ischemia , or either due to collateral support or lack of it

Intra coronary Imaging

When angiography shows multiple severe lesions with no obvious acute features, coronary imaging like OCT/IVUS can be helpful. It visualises plaque rupture, thin-capped fibroatheromas (TCFA), red/white thrombi, and superficial plaque erosions. IVUS can help identify ruptured fibrous caps, and intramural haematomas.However, the temptation to do imaging should be resisited as performing this in ACS adds its own risk.
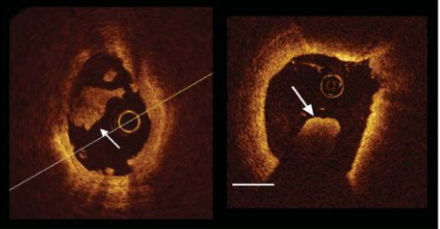
Thromotic lesion in ACS revealed by OCT . Image source Francesco Prati et al European Heart Journal 31(4):401-415

What about FFR & iFR ?

Physiological tools like FFR / iFR / iFR are less useful to identify culprit lesion rather it tell us about the flow across the lesion.

Final messsage

Identifying IRA in NSTEMI/UA is more challenging than in STEMI, relying on basic ECG and ECHO tests. It is good to realise, this effort may be redundant if we are considering only medical management.(Which is often the case in many low risk patients)

Reference

1.Baumann AAW, Mishra A, Worthley MI, Nelson AJ, Psaltis PJ. Management of multivessel coronary artery disease in patients with non-ST-elevation myocardial infarction: a complex path to precision medicine. Ther Adv Chronic Dis. 2020 Jul 1;11:2040622320938527. doi: 10.1177/2040622320938527. PMID: 32655848; PMCID: PMC7331770.

Read Full Post »

How can we use AI as a tool of knowledge distillation ?

Here is a deep discussion with Grok 3, on the merits, limitations & validity of DANAMI 2 and PRAGUE 2 , the two old studies on pPCI. Curiously , we don’t have any other studies to quote. As on 2025 , superiority of pPCI hangs precariously on these two decade old studies, which has some serious omissions in the primary end point and its Interpretation. To get into the facts , please go through the following link.

https://grok.com/Is primary PCI really superior to lysis in a global perspective /

It is a long chat, I am sure most of you can’t spare your vital time. But, the truth comes out only at the fag end of the conversation.

Read Full Post »

As the medical literature expands exponentially, the quality and intent of the research questions sound awry. There are only a handful of journals like JAMA that are bold enough to ask some tough and pragmatic questions in this glitzy world of medical extravaganza.

The current issue wants to set the pace for an important debate, on a topic that is rarely discussed.

The question is

Link to the article

Check whether your answers concur with this crucial query from Harvard Medical School and Massachusetts General Hospital. Three questions this article wishes to address.

1.What is the reason it is happening?

2. What are the implications?

3. What can be done for it?

My thoughts

“It is indeed over diagnosed. Once labeled, a chain reaction is set in. The cost, and resource consumption that follow a misdiagnosis are nearly identical to that of a true MI. More than that, the adversities of the tense investigative protocol can convert a misdiagnosis into a real one because that sadly includes even an overzealous poking right at the mouth of the coronary artery just o exclude a non existing MI . and ICU-related anxiety stand apart in this scientific comical game of ruling out a cardiac emergency.

The paper seems to blame mostly on the powerful screening test high sensitivity Troponin, Everyone will agree it has a major role in this. But, the more important reason is the cardiology community’s vigorous adoption of a universal definition of MI criteria (which is never intended to apply at the bedside) .Next factor is probably more important. The fear of missing a potential MI and legal consequences thereafter. I wish, the experts who sit on medical juries need to learn few extra lessons in the art of medical uncertainties.

Medical jurists, need to take some Intellectual cues from their criminal courts. How is it that, even well-planned criminal murders are successfully allowed to be argued and won in courts,…while inadvertent events such as missing an inconsequential MI by doctors are rarely pardoned?

How to avoid over diagnosis of MI ?

In this scenario, It is sad, that only very few cardiologists have the guts to ignore this omnipotent molecular sub-fraction of cardiac muscle Troponin, with their clinical skills. What we can do, at our level is to incorporate a new term “benign or micro myocardial Infarction” – akin to lacunar infarcts or TIA equivalents of the brain in the heart. We need to de-list the vast majority of chronic ischemic,non-ischemic, or systemic causes of Troponin leaks from the myocardial infarction chart. Physicians must realize, that protocol violation should not be deemed a crime always, rather it has a sure potential to benefit your patient if it is done properly and intelligently.

Final message

Recently one cardiologist in a sub-urban center was thrashed both physically and in social media ,for missing an ACS , which was subsequently recognised and treated well and good.

Doctors should be legally allowed,* (rather forgiven) to make permissible levels of errors in the medical decision-making process ” like any other profession .However, we must ensure our constant pursuit towards zero error, which may not be possible always. This should include overlooking apparently positive lab results if they have reasonably applied their clinical acumen. *Until this happens, the unquantifiable suffering of our patients* due to over-diagnosis and inappropriate interventions can not be reigned in.

*Maybe, this sounds more controversial statement in my 15 years of writing. Beloved patients shall note, it is a rare for me to make what probably, look like an anti-patient statement. Till now, I have been blamed my many of our colleagues, as self slandering my own profession for too many errors in many of the posts. Nothing can be done for this. When you search for truths , you need to tolerate all these.

Reference

1.McCarthy CP, Wasfy JH, Januzzi JL. Is Myocardial Infarction Overdiagnosed? JAMA. Published online April 24, 2024. doi:10.1001/jama.2024.5235

2.Shah  ASV, Sandoval  Y, Noaman  A,  et al.  Patient selection for high sensitivity cardiac troponin testing and diagnosis of myocardial infarction: prospective cohort study.   BMJ. 2017;359:

Read Full Post »

It was April 15th 1912, Titanic, the Invincible, had just sunk into the dark waters of the Atlantic coast off Newfoundland. Exactly same time around, Dr. James Herrick, In Chicago, Illinois was busy documenting the first diagnosed case of acute coronary thrombosis. A new disease was born ie Myocardial Infarction. This was also the era of the Noble Prize-winning  Invention of the ECG machine by Waller, Einthoven, and Thomas Lewis & co that sow the seeds for the specialty of electro-cardiology.

Though much was studied about MI with pathological specimens in the subsequent decades, there was a lull in the efforts to define the entity of myocardial Infarction till WHO  defined in the early 1970s. It was dogmatic, still fair enough. (Clinical, Enzymes, ECG criteria, with  any two feature, must be present to diagnose )

Since then, the field of cardiology has seen unprecedented development in both the diagnosis and treatment of ACS. We now have a universal definition( EHJ 2019 Thygesen K ) that asks us to triage based on high sensitive troponin followed by clinical and other parameters. STEMI usually doesn’t have much diagnostic confusion.

Nomenclature Issues in NSTEMI/UA

The definition of NSTEMI  refuses to settle, though we have come a long way since the times  UA/NSTEMI were clubbed together as siblings. The term unstable angina was coined by one of the most revered cardiologists of our times  Dr. Noble O Fowler in 1978. They are the same one hitherto referred to as Intermediate coronary syndrome/Pre Infarction angina. Later, if enzymes were raised it was labeled as non-transmural/Non-Q  MI. This became the classical NSTEMI later changed to NSTEACS (Still it is valid)

The semantics surrounding the NSTEMI  is unlikely to end as long as we depend largely on ECG to diagnose and treat complex coronary obstructive syndromes. This, by no means, undermine the importance of ECG in this setting. It will remain the gold standard as far as, I can look into the future.

Some observation about the new ESC 2020 NSTEMI guidelines

Anyway, ESC 2020 has addressed this issue. It suggests a new term “ACS without persistent ST elevation” for NSTEMI (Ideally they should have used this abbreviation  NP-STEACS)

(*I guess, the current ESC 2020 guidelines really wanted to get rid of both NSTEMI/NSTEACS for a very valid reason but still it was worried about the confusion it might create so retained the old term NSTEMI/NSTEACS  )

The categories included in the current NSTEMI scheme are

1.Transient ST elevation (How transient ? Prinzmetal/ Non Prinzmetal ?)

2.Persistent ST depression

3.T inversion

4.Flat (Absent ) T wave

5.Pseudo normalization of T

It may include the following as well (Not in official ESC 20220 guidelines)

6*.Hyperacute T (Very early STEMI ? or NSTEMI?

7*.Wellen/Dewinter or its variants

I think ESC is to be appreciated for recognizing an off ignored observation that UA may have a transient ST elevation and end up later as NSTEMI/NSTACS. This group of ACS still poses a challenge for us to understand the overlap between total and subtotal coronary occlusion (Non-Prinzmetal ST elevation)

Final message 

Does this nomenclature issue create problems in management? 

  • Yes, it does. The major implication is in the diagnosis ACS with dynamic ST segments ( ST-elevation / /depression or any combination)
  • If a probable STEMI after spontaneous lysis presents as NSTEMI, Is it the baby STEMI or neo NSTEMI ? One may not rush such NSTEMI patients to cath labs.
  • Of course, many of us are conditioned to follow a “single point agenda “ that dictates all ACS shall reach the cath lab and managed thereafter based on coronary anatomy. If that is the case, I am sure the bulk of this 79-page new NSTEMI guideline appears redundant.(Ref 1)

Reference

1.Jean-Philippe Collet,  ESC Scientific Document Group, 2020 ESC Guidelines for the management of acute coronary syndromes in patients presenting without persistent ST-segment elevation: The Task Force for the management of acute coronary syndromes in patients presenting without persistent ST-segment elevation of the European Society of Cardiology (ESC), European Heart Journal, , ehaa575https://doi.org/10.1093/eurheartj/ehaa575

2 Fourth Universal Definition of Myocardial Infarction (2018). Eur Heart J 2019;40:237-269. 

Read Full Post »

Read Full Post »

This question always creeps in any coronary care unit.

Often times , there is a significant  histo-pathological overlap between severe degrees of  Ischemia* and  myocyte necrosis . (What is called micro infarcts, lacunar infarcts,  make us over diagnose MI). It is not yet clear , whether leaky myocyte cell membrane can release free cytoplasmic enzymes without actual cell necrosis.
Clinical Implication
Fortunately , there is not much .These bio markers are primarily used as prognostication tools .Many of these patients  need to  undergo early revascularisation. However , It is unwise ,to get alarmed by  just  Troponin positivity  in an other wise comfortable ACS patient.
* Some call severe degrees of Ischemia as Injury ! It is an old thought based entirely on ECG  .There is no specific cellular equivalent of electrical injury current !

Read Full Post »

This is a true story  . . . happened  many years  ago under my direct  vision.

A  48 year old women came with significant breathlessness and catchy  sub -sternal chest pain .

“I  was exerting too much in recent days  doctor” , she said .

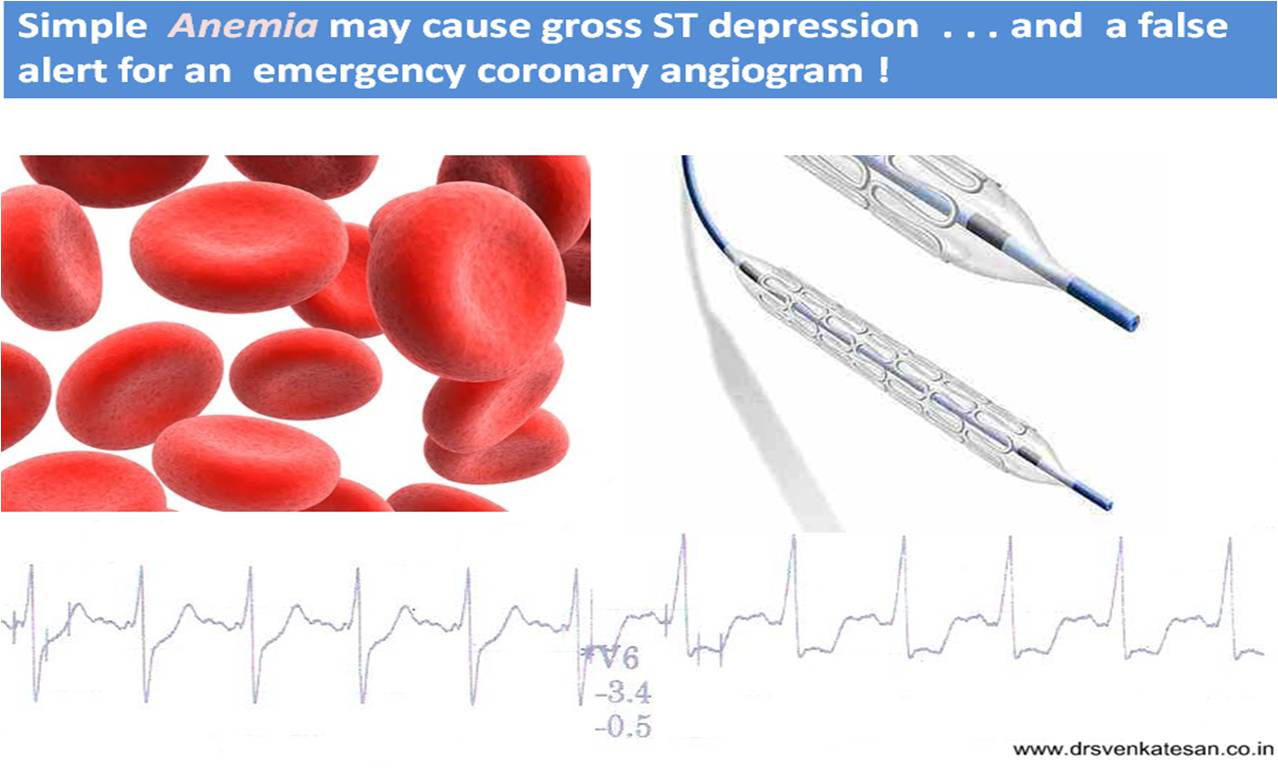
Her ECG  showed  a tachycardia and dramatic ST depression in most leads .

The ER in charge promptly texted the cardiologist .

The moment he saw the ECG ,he  had no hesitation , to order for an emergency angioplasty  (  How can he plan a angioplasty  , without even  knowing the coroanry anatomy . some one murmured  . May be   . . what he probably  meant was emergency angiogram   the other explained )    Further , he was telling his    fellows  . . . that  this is going top be  tough case and a possible  left main PCI .

An emergency  angiogram was done .  On table  it was a huge  surprise for every one ,  it was a  a classical  text book   look alike normal coronary arteries !

The moment normal CAG was  visualized  the consultant  concealed his momentary  surprise    and went on to say  it is classical case of syndrome  X   with severe micro- vascular disease causing ECG changes !

As  the patient did not give any opportunity to poke her coronaries   she was wheeled out of  wheeled out of cath lab.

Meanwhile ,  first year  fellow came rushing with the blood reports and biochemistry .

Is everything  alright ?   Yeh sir ,  except her Hb %  . . .  it is  5.6  Grams !

The bewildered  consultant *  realized   the  high  coronary drama , that is  been enacted  over the  past 2 hours !  and  learnt  (and taught) a most important  lesson to their fellows !

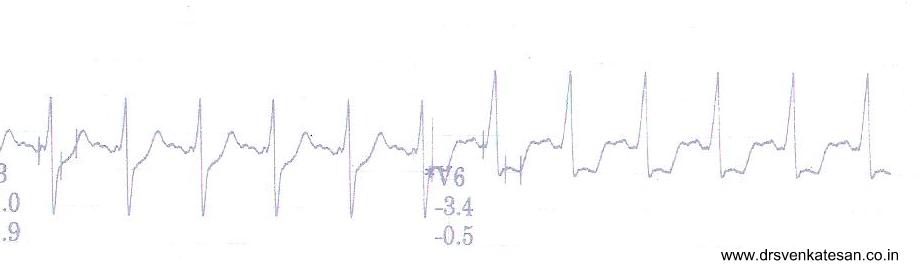
Hi guys , this is neither  a NSTEMI nor  a microvascular syndrome X  . . . this is simply anemia related  extreme  ECG changes !  We have erred in our reasoning and  our pre cath clinical scrutiny has  gone awry ! 

He went on to say  ,  don’t worry  many times medicine is learnt in  hard ways  . After all nothing adverse has  happened here .

The women was subsequently investigated and handed over to  gynecologist for a probable hysterectomy .

Final message

Please be reminded  , anemia  can produce  variety  of  ECG changes.  In extreme anemia  global ST depression is  common especially if  tachycardia is associated .

The lesson here  is ,  whenever  gross  ST depression is witnessed  with vague chest pain  check the hemoglobin first . This is an unusual story of a women  ,  with simple  anemia  (due to   chronic mennorhagia )   landed in cath table in an acute fashion .  Luckily  she  did not have any  incidental coronary  lesions  that prevented her becoming a  greater cath lab  victim !

* The bewildered consultant is none other than the author  of this blog.

Read Full Post »

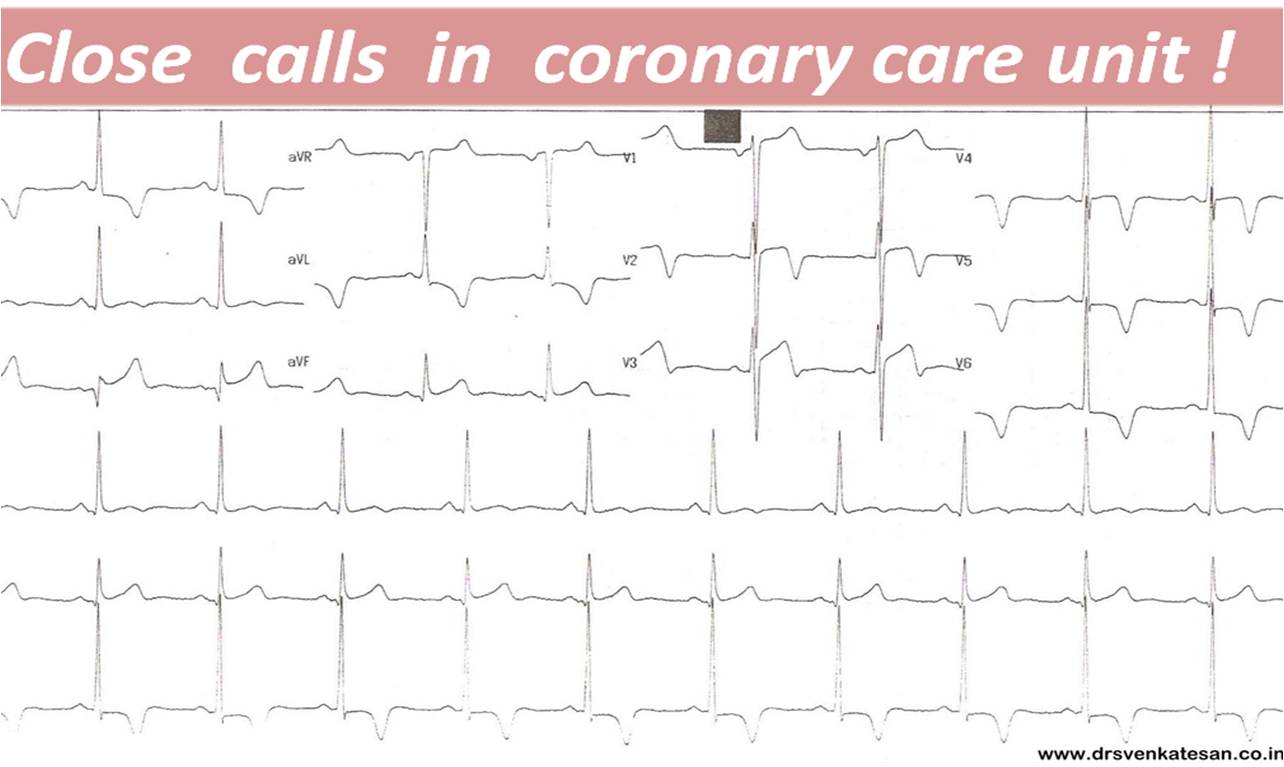
This  is the ECG  of  a  45 year old man with  H/O hypertension  and  chest pain .The general practitioner who first saw him alerted this  patient about a possible  heart  attack  asked to meet a cardiologist immediately. The cardiologist who  saw  this ECG   tended to confirm  the diagnosis  and advised admission in  a coronary  care unit .

The patient   defied  both  and  somehow landed in my echo lab  .  Looking at the ECG   I also  expected  it to be a  STEMI  evolving into a  Non Q  MI .

I was surprised  to find  only LVH with absolutely no wall motion defect  . There was no evidence of ASH,  HOCM or apical cardiomyoapthy as one of my fellows initially  suspected . His  EF was 70 %.   Cardiac enzymes were sent by then. When  I spent few minutes  with him ,  listening the history , it was very clear  what  he had was  non cardiac pain . In the anxiety ,  no one  got it right  about the character of pain ,which  was localised , lasted  for few seconds and  least suggesed angina.

The moral of the story is   listen to the patient  however dramatic the ECG may look !

What is special in this ECG ?

It is common for LVH with ST depression to be  mistaken for  ACS/NSTEMI

Here , there were  other  observations that  added  more  complexity .

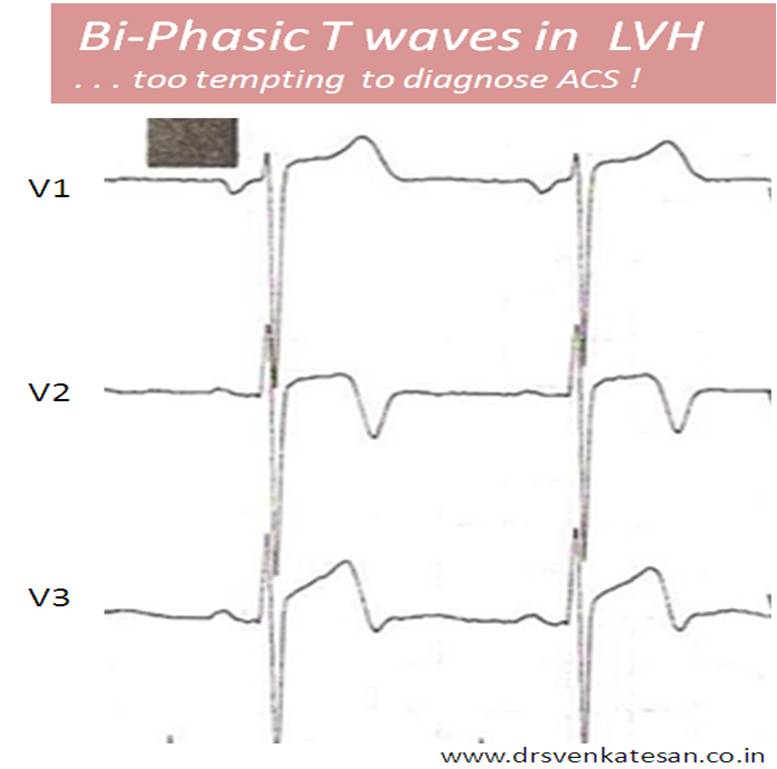
  • Presence  of  ST/T changes in inferior leads(ST elevation in lead 3)
  • Bi-phasic  T wave in v1 to v3
  • ST elevation  in precardial leads

In LVH  it is usual  to note  ST depresion , how do you explain ST elevation in LVH ?

ST elevation in LVH   may occur in  leads  v1 to v3   . It is very rare  for LVH to inscribe  ST  elevation in   v4 v5 v6  .   Why certain  leads elevate the ST segment while others depress  in LVH  is not clear. It may represent  incomplete LBBB pattern where the ST segment deviates opposite to the  dominant QRS  complex. Septal  hypertrophy often elevate  while free  wall  hypertrophy depress the ST segment . Since V5,V6 leads are free wall oriented , these leads  record  classical  ST depression .

Importance of Bi-Phasic T waves

Please remember  Bi phasic T waves are notorious for it’s  unpredictability. An  innocuous looking bi-phasic T waves  (especially  with dynamic behavior )   is a  harbinger of proximal  LAD or even left main disease.

Finally , what will be ECG  changes if a patient with classical  LVH  who  develops a  real  STEMI ?

  • LV strain  pattern normalises ?
  • Further ST depression  occurs ?
  • No great changes . ECG  Looks near normal ?

Answer : ?

What is the significance  of   Bi-phasic T  waves : A  link to  a related post

Read Full Post »

Acute STEMI is the numero uno of  all medical emergencies. Hundreds of life are lost every few hours in our planet.Significant  chunk of them  do not   even reach the hospital alive  . While the emergency crew has many vital responsibilities , the cardiologist job starts only after the patient reaches the hospital .  Hence  the ambulance  crew  need to act much more sharper. Please remember even the  skills   of the driver  will have a direct impact on the myocyte survival.

The symptom to first  medical ( or second  hospital ) contact could be as vital  as a primary PCI procedure itself . A 3 minute traffic jam can kill 3 thousand myocytes ! One could imagine the importance of  decision making process here.

Distance from  the point of contact to PCI lab , the anticipated delay ,   intensity of traffic  matters .

Is it not funny ,  to realise  when   we  have  a reperfusing agent on hand , within the ambulance and the vehicle stuck in  the traffic jam  waiting to reach a  reperfusion  room situated  50  km down the high way !

( One may wonder why can’t we thrombolyse every one  routinely  in the ambulance  and do  the PCI later in  . . . But surprisingly  this    concept  simply does  not work  !)

When we realise , even in  a well developed country like Netherlands ,  time to shift  to cath lab is a big issue (Read the following article )  we will never ever know , how much of myocardium  is consumed  by traffic jams  in  a  country like India  , where   the traffic   scenarios   can be  more chaotic  than a  VF  !

Events  that unfold following a STEMI  are crucial

It begins with chest pain recognition.

Call for first help Spouse/Family doctor /Neighbor

Call for 911/108 . Ambulance arrival time and boarding

Administration of  Aspirin + clopidogrel*

Meanwhile spontaneous thrombolysis will begin in most of them !

A promptly administered Aspirin and clopidogrel   a shot of heparin and a lytic agent within 30 minutes is distinctly possible and may be more  effective  at a fraction of cost.

Highway thrombolysis

Even though current studies still  . . .do not  favor primary PCI over thrombolyiss in the first hour ,  most of the cardiologist  do show some  favoritism  towards pPCI for some unknown reasons.

So by default ,  many of the   ill fated  STEMI patients    enter  an  unrealistic  hemodynamic   race  in the deadly highways and urban lanes our country !

For every minute  that goes by ,  the patient  not only loses  his  muscle but also the  golden opportunity to get salvaged by the thrombolytic agents .

Since ,  a delay  beyond  one hour eliminates the indication of thrombolysis  (if a cath lab is available in the vicinity  ) many times   traffic delays  convert a potential   hyperacute  thrombolysis  into a say . . .    3-6 hour old  PCI .(Should we feel happy about it ?)

Here , we need to know TIMI 2 flow achieved easily by thrombolytic  agents is  quiet effective in preventing myocyte death.

Fast  track   shift to PCI

Helicopter drop over cath lab -( Distant dream ?  or better to be in dreams )  It has been noticed even a helicopter was squarely beaten by the  thrombolysis  in terms of  early  and  timely  reperfusion.

Fast -Slow track PCI ?  (Like fast slow AVNRT !)

Unexpected delays on  road  , in  many countries  financial issues  /Insurance sanction etc  contribute to the time delay significantly . What starts as a fast track  protocol  peters out  into  slow race (Late primary PCI ) and may even  end  in a grinding halt.(No primary PCI )

Worse still  . . . some of these patients  are made   unsuitable  for  thrombolysis  as well !

Final message

Management of STEMI  is gradually becoming a team effort.  The emergency crew , the command , the destination hospital all need to be  alert  and proactive. When the  initial  anticipated delay  is getting prolonged , get the ground staff  in  cath lab  ready for  an  emergency landing .

A word of  advice  for  the ambulance crew .Involve them  more   in the decision making  as  they   are in a better position to calculate the  possible delay.  If delays  are anticipated  propose a thrombolytic order and get clearance from the command and administer the lytic agent as early as possible.

It is highly likely , restoration of   TIMI   2  flow  right in the middle of   national highways  is much  . . .   better than a   TIMI 3 flow  that  is going to come  later   . . .in  a distant  cath lab .

Finally use the common sense  liberally  before you  act   . . . unfortunately it has become  the most elusive  sense for man kind  !

References :

Here is a study that gives a fresh insight into this  enigmatic issue of pre-hospital thrombolysis vs primary PCI

http://www.ncbi.nlm.nih.gov/pubmed/21315205

Read Full Post »

NSTEMI is a  common clinical problems in CCU.

When we say  NSTEMI it can mean any of the following

  • NSTEMI with ST depression
  • NSTEMI with T  wave Inversion
  • NSTEMI with Biphasic T wave
  • NSTEMI with normal ECG
  • The irony   called STEMI evolving as  NSTEMI**

By default most of  us think ,  if it is NSTEMI  . . . there  must be ST depression. This thinking is  not logical but traditional. Still,   ST depression may be the  common presentation. NSTEMI with ST depression  has much worse outcome than other forms.

The following ECG is from a 45 year old man with a vague mid sternal  chest pain for 48 hours.

The unusual type of NSTEMI with Bi-phasic T waves

His echo showed wall motion defect in LCX territory .A diagnosis of NSTEMI was made.The predominant finding was biphasic T waves .

**One may wonder  why can’t we call this ECG as a  Classical STEMI ?

There is a 2mm  ST elevation ,  with a infarct as well  ? But , the point  here  is there is no business for T waves to get bi-phasic or inverted in the early hours  of  a  classical STEMI .

This  exactly has happened here. Hence we can not call  the above event as  STEMI . Instead it  is ,  STEMI   evolving into NSTEMI . So  a combination of  features of STEMI/NSTEMI occur together. The best description for above  entity is  STEMI in transition to Non Q MI

Read the related article in my site  Is the terminology of Non Q MI still relevant or obsolete ?

Read Full Post »

Older Posts »