Posts Tagged ‘bmj’
What is the greatest medical breakthrough since 1840?
Posted in cardiology-ethics, Uncategorized, tagged Add new tag, bmj, COMMON SENSE, ethics, INTERHEART on October 14, 2008| Leave a Comment »


How is the blood volume distributed in normal human body ?
Posted in Cardiology - Clinical, cardiology -Therapeutics, Infrequently asked questions in cardiology (iFAQs), tagged autonomic dysfunction, blood volume, bmj, capillary, cardiac output, cardiology, drsvenkatesan, effective circulatory volume, fludrocortisone, heart, Hemodynamics, lnacet, lvedp, nejm, ortho static hypotension, pcwp, physiology of circulation, pulmonary edema, syncope, venous circulation, venous insufficiency, venous pooling on October 9, 2008| Leave a Comment »
Humans have roughly 5 to 6 liters of blood at any given time in their body . Out of this*
50% (2500ml) is located in the systemic venous compartment. 18% is within the pulmonary circulation participating in the vital oxygenation 12% (500-600ml) is within the cardiac chambers. 8% is in the arterial tree of the body. 5% is within the capillaries. 2% is in the aorta.* Source : Best & Taylor Physiological basis of medical practice 1966, 8th edition
What is the implication of this predominantly venous distribution of blood at rest ?
- A competent venous tone is essential for the human beings to maintain the erect posture.
- Bulk of the cause of syncope in humans is due to peripheral mechanism like loss of vascular tone and resultant venous pooling.
- The concept of venous reservoir is so important in emergency situations like hypotension as simple elevation of legs is equivalent to infusing 500 -800 ml of intravenous saline .
- Similarly during acute left ventricular failure trunk elevation and legs dangling down can reduce the pulmonary congestion very significantly and reduce pulmonary capillary wedge pressure (LVEDP)
Autonomic dysfunction and venous insufficiency
Autonomic dysfunction and resultant orthostatic hypotension is directly related to venous reservoir dysfunction.Increasing effective circulatory volume by elastic stockings or administration of mineralocorticosteroids like fludrocortisone (.5mg/day ) can be useful in this condition
What determines hemodynamic stability in ventricular tachycardia ?
Posted in Cardiology - Electrophysiology -Pacemaker, cardiology- coronary care, Infrequently asked questions in cardiology (iFAQs), tagged bmj, fasicular tachycardia, heart rhythm, Hemodynamics, ischemic vt, jama, lancet, lvot vt, myocardial VT, nrjm, pace, ventricular tachycardia, verapamil sensitive vt on October 3, 2008| Leave a Comment »
Ventricular tachycardia is considered as one of the most dangerous cardiac arrhythmia .Rather , it is the label VT that spreads more fear than the arrhythmia itself. It is a fact many patients with VT walk into hospital , still VT will always be a sinister arrhythmia as long as it carries a risk of degenerating into ventricular fibrillation.
What determines hemodynamic stability in VT ?
- Origin and location of VT
- The ventricular rate
- Presence or absence of AV dissociation
- Impact on mitral inflow pattern
- Associated left ventricular dysfunction or valvular heart disease.
- VT in the setting of acute coronary syndrome.(Ischemic VT)
- Inappropriate drug selection
Origin and location
VTs originating high up in the ventricle( High septal VT,Proximal VTs) have more organised ventricular contraction and they are more stable.Distal VT originating in the myocardium away from the conducting system has chaotic myocyte to myocyte conduction.These are very unstable.
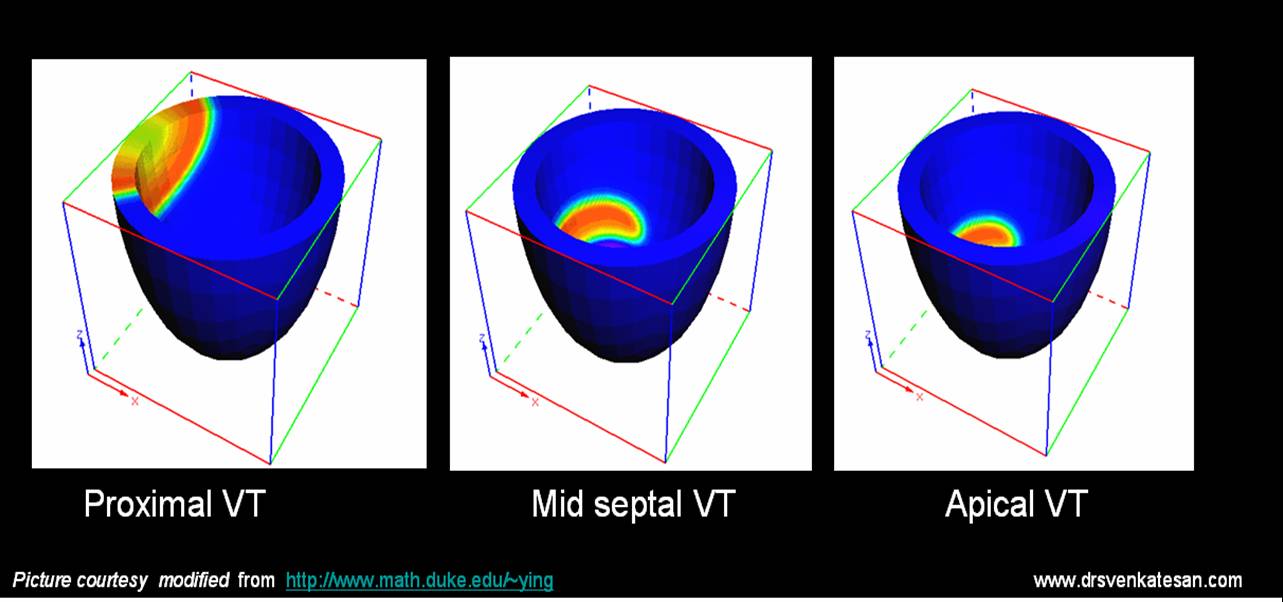
The term fascicular VT is nothing but VTs originating in the His bundle and it’s branches( Can also be termed Septal VT ).These VTs are also stable and some of them respond well to calcium blockers indicating that they are very close to the AV junction and carry the properties of junctional tachycardia. QRS width gives a rough estimate about the location of VT. Narrower the VT higher it’s origin.( But remember even in VT , qrs can further widen on it’s way downhill !)
LV dysfunction.
This is probably the most important determinant of the outcome in VT. Patients with severe LV dysfunction (EF <30%) fare badly .Hence the land mark concepts from MADIT 1& 2 demanded ICDs in these patients.The most common clinical setting is dilated cardiomyopathy.SomE of them have bundle branch re entry(BBR).This particular VT can be stable for many hours.
Ventricular rate.
Usually VT has a rate between 120-200.Higher the rate of VT more the chances of instability .This rule is also not always true as fascicular VT can be well tolerated at high rates.So location of VT focus and LV dysfunction usually over rides the impact of ventricular rate.
Mitral inflow pattern
Proper left ventricular filling is the key to hemodynamic stability in VT. In proximal, septal,fascicular, LVOT VTs doppler studies suggest (ACC /AHA Type C evidence : Personal observations in CCU during VT) near normal preservation of bi modal filling of mitral valve inflow.In ischemic myocardial VT the mitral inflow profile is critically affected . There is no distinctive forward filling was observed .In fact at rapid rates a short pulsatile MR jets are noted instead.
Associated valvular diseases
It is obvious, aortic and mitral valve disorders can aggravate the hemodyanmic instability.
Final message
The clinical behavior of ventricular tachycardia is widely variable and dependent on multiple factors.
Associated LV dysfunction and structural heart disease ultimately determine the outcome.
How do you grade pulmonary arterial hypertension ?
Posted in Cardiology - Clinical, Infrequently asked questions in cardiology (iFAQs), tagged annals of internal medicine, bmj, cardiology, chest, drsvenkatesans, eisenmenger, grading of pah, grading of pulmonary hypertension, jama, lancet, lungs, mitral stenosis, nejm, pah, pulmonary arterial hypertension, pulmonary hypertension, rabinovitch, rubin on October 3, 2008| 1 Comment »
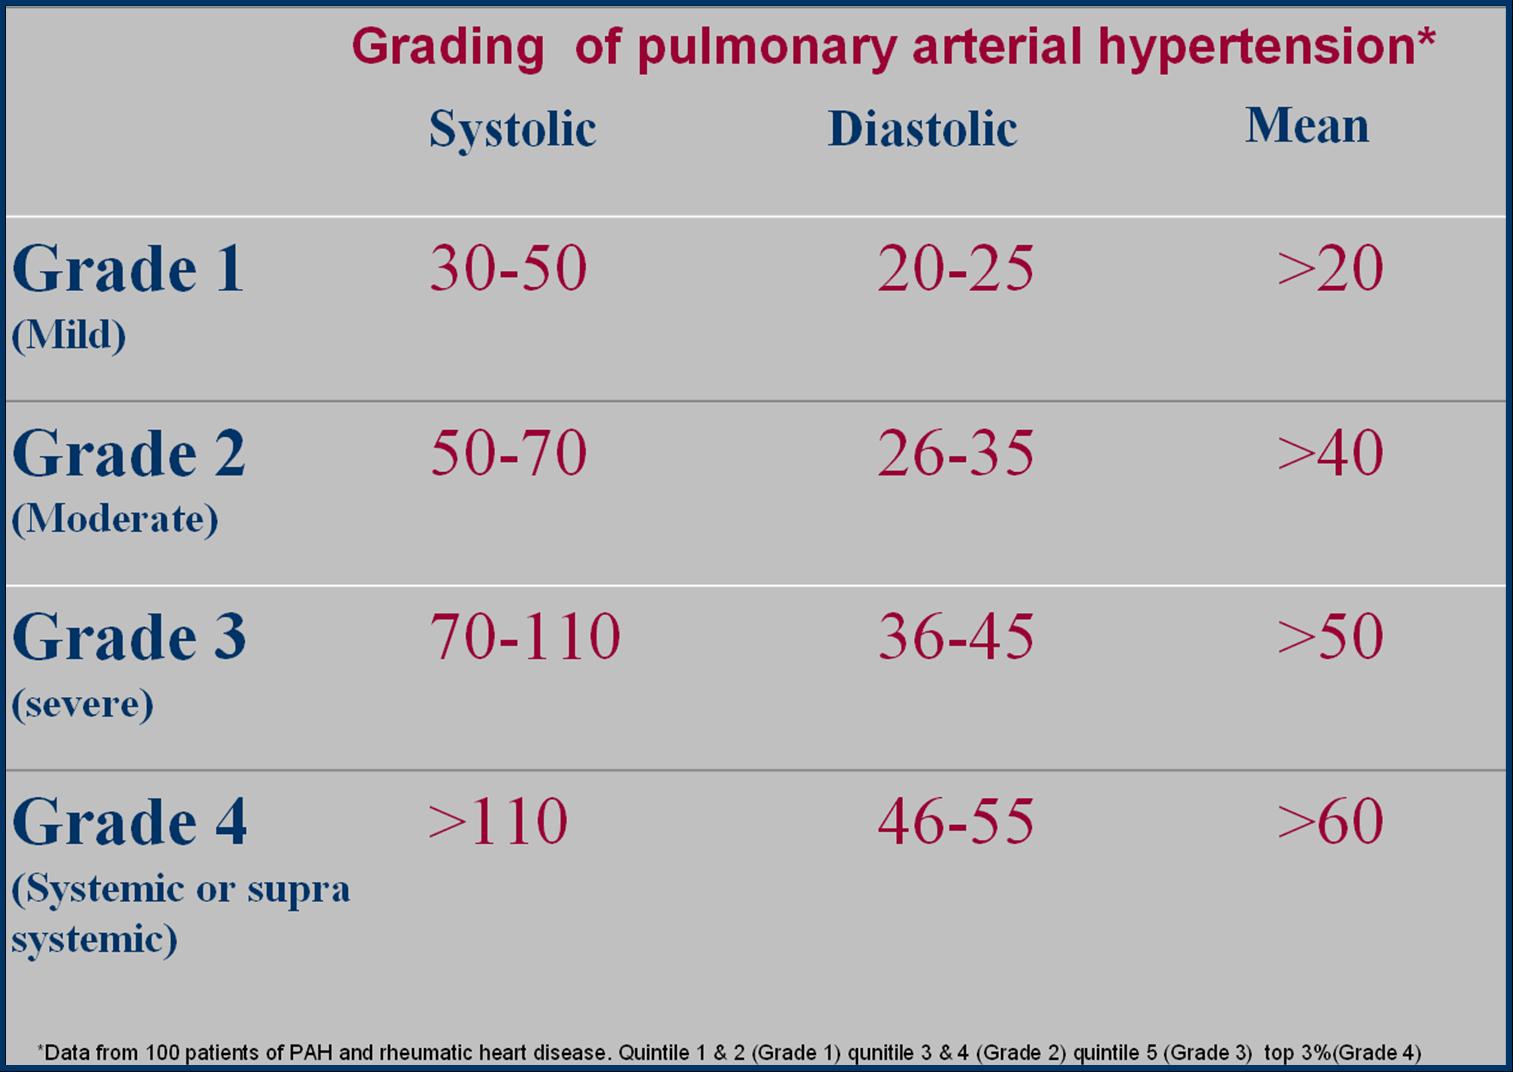
Even as cardiology community is preoccupied with systemic hypertension & CAD , pulmonary arterial hypertension(PAH) is a much neglected , still an important clinical cardiac problem encountered . The irony is self evident , there are half a dozen methods to grade systemic hypertension not even a single stadardised grading available for pulmonary arterial hypertension. The WHO working group defined pulmonary hypertension few decades ago and was not clinically graded .The only grading available is based on the pulmonary vascular biopsy changes (Heath Edwards)
Currently PAH management has gone through revolutionary changes. There is an urgent need for grading this entity .This will facilitate to diagnose , manage and assess the efficacy of the currently available treatment.
Developing countries like ours have a great number of PAH due to rampant rheumatic heart disease. A simple study was done in 100 patients with PAH .Bulk of the study population had RHD .Few had primary pulmonary hypertension .Systolic , diastolic, and mean pressure was assessed by doppler echocardiographic analysis of tricuspid regurgitation (TR) and pulmonary regurgitaion(PR) jets. TR jet provided the systolic PA pressure , PR jet provided mean as well as diastolic PA pressure .TR jet was available in all patients. PR jet was available only in 60 patients .Hence the diastolic andmean PA pressure data has been extrapolated in some and was plotted in a scatter diagram. Five equal quintiles were divided. Patients in first and 2nd quintiles were graded 1 and third and 4th quintile were graded 2 , 5 th was graded 3 respectively. From this cut off points for various grades of PAH were identified .The top 3% of patients with highest PAP were graded as grade 4 and all of them had supra systemic PAH.
The following grading is suggested for PAH*
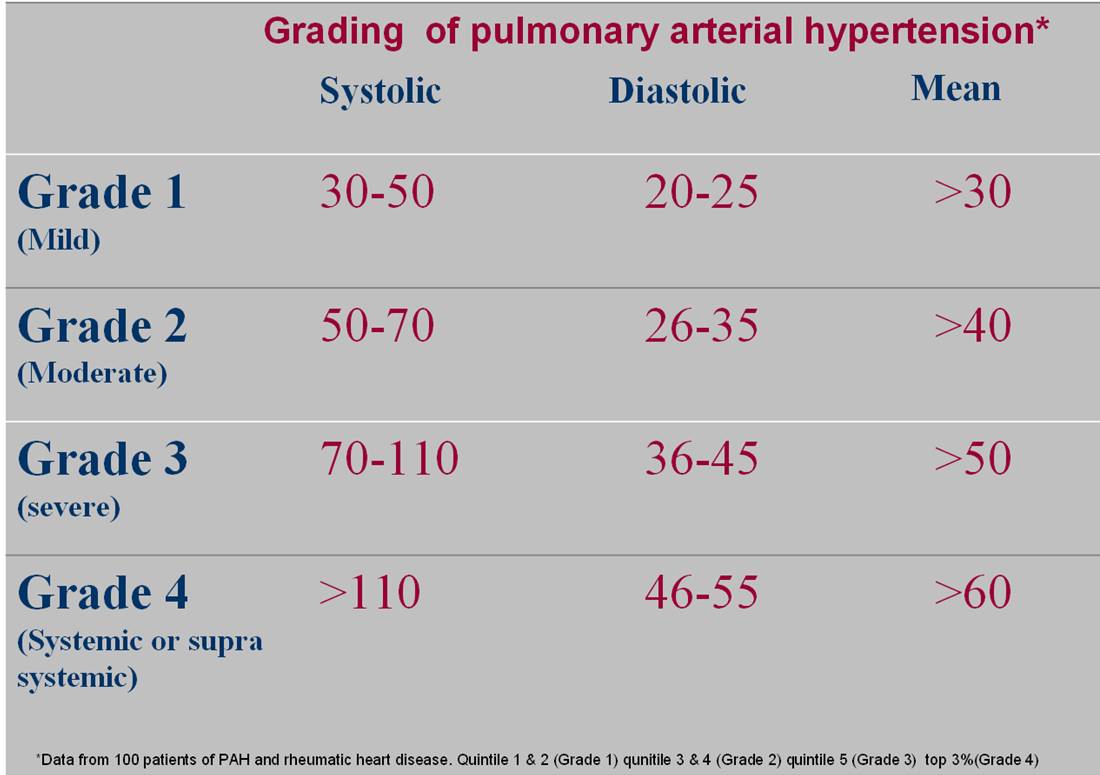 *This is a preliminary attempt to grade PAH. This could be applicable mainly in rheumatic heart disese and primary pulmonary hypertension .Further refining of methodology is required.PAH grading may be little different in congenital left to right shunts.
Cardinal symptoms in cardiology : Palpitation , some observations
Posted in Cardiology - Clinical, Tutorial in clinical cardiology, tagged anxiety state, asd, bmj, bradycardia, cardiology, clincal cardiology, drsvenkatesan, hyper kinetic circulation, lancet, nejm, palpitation, Tachycardia on October 2, 2008| Leave a Comment »
- Palpitation is one of the common symptoms for which cardiac patients are referred. Like dyspnea , palpitation can either be a physiological expression of normally beating heart or a dangerous pathological state of the heart. This makes this symptom unique and warrants careful evaluation.
 By definition palpitation is abnormal awareness of ones own heart beat. Heart is a mechanical organ with multiple mobile anatomical structures. There is constant blood flow in multiple directions . Apart from this the heart has it’s unique translational, rotational movement . These intrinsic movements combined with proximity to chest wall generate vibratory motion signals .These signals are generally dampened by the encircling pericardial space .The neural signals responsible for perception of palpitation is not clear. If the heart hits against the chest wall it is the somatic nerves from the chest wall that carries the signal. Vibrations generated within the heart chambers, and and the valves are carried by the myocardial and intravascular sensors.( Autonomic)
What are causes of palpitation?
Cardiac
- All hyperdynamic circulatory states. It may be generated from either right or left ventricle or both.
- Regurgitant lesions ( Mainly Mitral and aortic regurgitation)
- MVPS*
- Congenital heart disese ( Mainly left to right shunts-ASD/VSD/etc)
- Apart from this patients with prosthetic heart valve, and pacemaker patients can feel their heart beats.
- Cardiac arrhythmia .Both tachycardia, and bradycardia . Ventricular ectopic beats are the very common cause .( It is often described as missed beat)
* Mitral valve prolapse, a very benign condition, over diagnosed in the last few decades raised considerable anxiety and palpitations for the patients (mainly after the diagnosis ! ).Now the cardiology community has sought to underplay this entity with strict diagnostic criteria.( Thickened mitral leaflet ,presence of MR both must be present to label a patient as MVPS)
Non cardiac
- Physiological
- Anxiety state
- Anemia
What is the relationship between ejection fraction and palpitation?
- Generally palpitation indicate a hyper kinetic state of heart .The commonest cause of palpitation is anxiety state .This also happens in hyper dynamic circulations like anemia , fever, thyrotoxicosis, pregnancy etc . In all these situations palpitation indicate increased force of contraction which generates high dp/dt(Rate of rise of ventricular pressure) . So the left ventricularejection fraction is normal or more than normal . So presence of palpitation could be an indirect evidence of reasonably good LV function.
“Patients with dilated cardiomyopathy or CHF rarely feel their heart beat during exertion , instead they have dyspnea as the LV force of contraction is less”
What is the significance of palpitation that occur during rest ?
- Palpitation occurring at rest indicate more often a pathology.It is invariably due to an cardiac arrhytmia either tachycardia or bradycardia. Intelligent patients can give accurate information about the regularity of rhythm , any extra beats or missed beats . Atrial fibrillation, VPDs could be diagnosed by history alone in them !
If palpitation is associated with visible chest pulsation what is the likely diagnosis ?
- If significant visible pulsation over chest wall pulsations are seen in young adults it could simply mean a hyper dynamic circulation and thin chest wall. Pulmonary arterial pulsations is not normally felt in left 2nd inter costal space.If felt one has to rule out shunt lesions like ASD or pulmonary hypertension.
- “ASD is the commonest cause of right ventricular palpitation “
Forgotten concepts in cardiology : Amlodipine as an anti anginal drug
Posted in Cardiology - Clinical, cardiology -Therapeutics, Infrequently asked questions in cardiology (iFAQs), tagged amlodipine, amlogard, angina, beta blckers, bmj, calcium channel blockers, cardiology, chronic stable angina, diltiazem, drsvenkatesan, jama, lancet, nejm, nifedipine, prinzmetal, unstable angina, vasospastic angina, verapamil on October 2, 2008| Leave a Comment »
Amlodipine , the most popular anti hypertensive drug used world wide has an very important action on coronary blood flow.When nifedipine was introduced three decades ago it was known for it’s powerful anti anginal properties. Subsequently amlodipine was introduced with almost similar action. But over the years, amlodipine was projected primarily as anti hypertensive drug and gradually many of the physicians are made to believe it is a drug that should be used only if the blood pressure is high.The fear of reflex tachycardia in few was exaggerated.
In fact a cross section of today’s general physicians were queried about amlodipine and none of them acknowledged using this drug as an anti anginal drug. And few of them went to the extent of withdrawing amlodipine if it was used for the purpose of angina relief !
Why amlodipine’s anti anginal action is in doldrums ?
The single word answer is unfortunate! Marketing bias ,coupled with the fact that mainstream cardiology texts have ignored this aspect.
Final message
Amlodipine , can still be used as a antianginal drug especially in a patient who has angina with associated bradycardia , significant LV dysfunction . Some reserve amlodipine and nifedipine exclusively for vasospastic angina where beta blockers alone are theoretically contraindicated .
Why syncope is rarely fatal ?
Posted in Cardiology - Clinical, Infrequently asked questions in cardiology (iFAQs), Uncategorized, tagged bmj, cardiac arrest, cardiology, cardiology lancet, drsvenkatesan, epilepsy, head up tilt test, holter, hut, hypoglycemia, jama, loop recorder, loss of consiouness, nejm, neuro cardiogenic syncope, stroke, sudden cardiac death, syncope, vaso vagal syncope, ventricular tachycardia on September 30, 2008| 1 Comment »


Syncope by definition is a transient loss of consciousness due to cerebral hypo perfusion and loss of muscular tone, and the patient falls but recovers fully and gets up either assisted or spontaneous.The cardiac and vascular counter response to syncope is most often intact .This makes syncope characteristically transient . If a patient does not recover from syncope it could either be a prolonged loss of consciousness( Stroke etc) or if he never gets up he will be called a victim of cardiac arrest or a SCD ! (Sudden cardiac death ) . So technically by defintion , all patients will have to survive the syncopal episode.
But the following questions need to be answered
- How prolonged a syncope can be ?
- Can syncope lead onto sudden cardiac death ?(SCD)
- What are life threatening syncope and non life threatening syncope ?
What is the link between, syncope and SCD in patients with ventricular arrhythmia’s ?
Some case of long QT syndromes could be life threatening especially in children as they inherit sudden death. A patient with a non sustained VT may develop syncope if the VT becomes sustained especially if there is underlying heart disease and LV dysfunction . Among this few , may degenerate into ventricular fibrillation and patient may die.
How common is syncope in acute myocardial infarction ?
Syncope is a very rare presentation of acute myocardial infarction.
Can syncope precipitate or precede a cerebro vascular accident ?
Prolonged syncope , TIA, stroke in evolution and completed stroke can be a continuous spectrum in patients with carotid and cerebrovascular disese . But when a syncope evolves in to a stroke the patient is not considered to be a victim of syncope but they enter the stroke protocol.
There is a big list for the causes of syncope
But to put it simply
A.Cardiac
- Purely electrical ( Arrhythmic- Brady, Tachycardia)
- Mechanical( Valvular obstruction, and other structural heart disease etc)
B. Non cardiac
- Vasovagal (Commonest 90% of all syncope)
C. Metabolic*
- Anemia
- Hypoglycemia
- Hypoxia
How to work up a patient with syncope ?
First , one need to confirm it is indeed a syncope . If the initial examination is not clearcut one need to go back to the history and ask for circumstances under which the syncope occured and details of prodromal symptoms if any . Patient’s family members who witnessed the event can give useful information . It is the most cost effective ( Comes free of cost infact !) investigative tool available .Cardiac syncopes are usually sudden, vasovagal often have environmental or emotional factor. Apart from routine investigations , ECG, Echocardiography, holter are done generally, head up tilt test, Loop, event recorders may be reuired in few.
Final message
Syncope is one of the common symptoms in cardiology and general medical practice. Many times the diagnosis is easy . Common syncope is never fatal but , ruling out dangerous tachy and bradyarrhythmias is a key aim. In a significant number (20-30%) identifying the cause could be really difficult and may never be made in spite of the modern diagnostic tools. These syncope of unknown origin is grouped along with the neurocardiogenic category.
The one, positive thing about syncope is (unlike chest pain) , it is rarely fatal in it’s first episode , gives the physicians to investigate and correct the underlying problem.
What is the mechanism of pericardial rub ?
Posted in Cardiology - Clinical, Tutorial in clinical cardiology, tagged auscultation, bmj, clinical cardiology, drsvenkatesan, epicardium, lancet, parietal pericardium, pericardial effusion, pericardial rub, pericarditis, spodick, to and fro murmur, venkatesan sangareddi, visceral pericardium on September 28, 2008| 6 Comments »
Heart is externally covered by two layers of pericardium . Pericardial space is formed between parietal and visceral layers of pericardium . It is a narrow space which is normally lubricated with pericardial fluid up to 25ml. When these two tissue surfaces come into contact , pathological rub takes place.It is heard whenever the pericardium is inflammed . Pericardial rub is a distinctive but uncommon clinical sign .
Common clinical conditions
- Acute pericarditis
- Uremic pericarditis.
- Rheumatic pericarditis
- Post myocardial infarction
Pericardium has two layers .
There are four possibilities for pericardial rub to take place.
The rub can occur
1.Between the two layers of pericardium
2.Between the visceral pericardium and the epicardial layer of heart*.
3.Between parietal pericardium and the chest wall
4.Pericardium can rub with the adjacent pleura( Pleuro pericardial rub )
The second and third mechanisms are very rare.
An update
We have realized one more possibility . Diaphragm forms the floor of the heart on which the hanging heart rests . Rubbing of pericardium over diaphragmatic surface is a beat to beat affair that lasts the entire life !. In inflammatory states of diaphragm especially the contagious ones from abdomen , can result in pericardio- diaphragmatic rubs .These rubs are almost impossible to hear clinically.
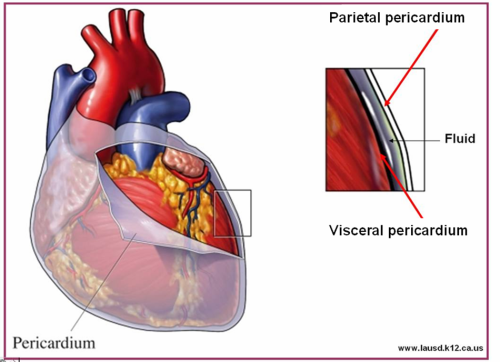
*The anatomic mystery : Is epicardium same as visceral layer of pericardium ?
Some anatomist feel that both are same entities. If that is the case myocardium can never split its relationship with visceral pericardium.But it is also a anatomical fact visceral pericardium engulfs the coronary artery and are located sub epicardially.

How many components of pericardial rub are clincally heard ?
Pericardial rub classically has three components. Systolic, mid diastolic, and pressytolic atrial components. Pericardial rubs are typically described as to and fro rub. Systolic component is most consistent. In atrial fibrillation mono component pericardial rub is heard.
Quality
Superficial , scratchy, high pitched ( Can also be low pitched)
Location
Left sternal border , left 2nd or 3rd space .Best heard in sitting , leaning forward in inspiration. Many times the rubs are transient and evanescent . Since it has multiple components it may be mistaken for added heart sound like S 3 or S 4.
What is the mechanism of pericardial rub in the immediate post MI phase ?
Presence of pericardial rub post MI indicate a transmural involvement or atleast significant epicardial involvement . Recognition of this is important as presence of pericardial rub increases the risk of rupture and hemorrhagic effusion if anticoagulants are used.
What is the relationship between pericardial effusion and pericardial rub ?
Generally it is said with the onset of effusion pericardial rub disappear.But this is not necessarily true.
Rubs after contusion chest and fracture ribs can be with the chest wall and may have no relationship with effusion.
Is pericardial rub a painful condition ?
Pericardial rub associated with acute inflammatory pathology is severely painful (like a pleuritis).But pericarditis associated with chronic inflammatory conditions are less often generate pain.The exact reason is not known.
What is pleuro pericardial rub ?
This clinical entity is poorly defined , often taught by veteran professors in clinical auscultation classes.It can be heard in the mid segment or diaphragmatic pleuritis with or without pericardial effusion in patients with atypical pneumonias.
Why thrombolysis rarely fails in right coronary artery ?
Posted in Cardiology -Interventional -PCI, cardiology- coronary care, Infrequently asked questions in cardiology (iFAQs), tagged acs, acute myocardial infarction, angiogram, bmj, cardiology, ccu, circulation, coronary, coronary circulation, failed thrombolysis, lancet, left anterior descending, nejm, nstemi, persistent st elevation, stemi, streptokinase, successful thrombolysis, thrombolysis, tissue plasminogen activator, tpa on September 22, 2008| 7 Comments »
Differential response of thrombolysis between left and right coronary system
- Thrombolysis is the specific treatment for acute myocardial infarction. ( Privileged few , get primary PCI))
- Failed thrombolysis occurs in significant number of patients ( 30-40%).
- Persistent ST elevation 120 minutes after thrombolysis is best indicator of failed thrombolysis.
- It has been a consistent observation failed thromolysis is more frequent in anterior or LAD myocardial infarction.
In a simple study we have documented patients with inferior MI rarely had persistent ST elevation and thrombolysis was successful in vast majority of patients ( Except in few patients associated lateral MI)
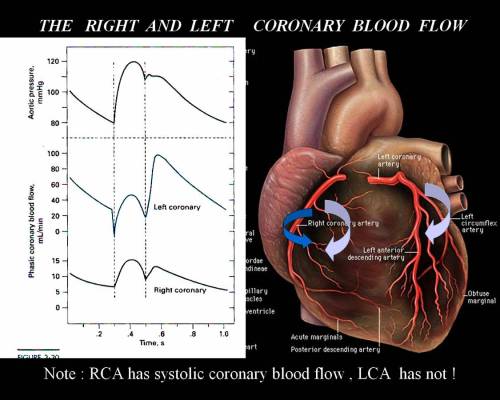
The mechanism of better thrombolysis in right coronary artery is simple.The success of thrombolysis , apart from early time window , is directly correlated with pressure head and the duration of contact between the thrombolytic agent and the thrombus. In right coronary circulation the blood flow is continuous , occurs both in systole and diastole that facilitates the maximum delivery of the thrombolytic agent . Further there is a favorable pressure gradient across RV myocardium as the transmural occluding pressure across RV is considerably less then LV myocardium.

This paper was presented in the “Annual cardiological society of India scientific sessions”
at Chennai, Tamil Nadu.India December 2000
Click to down load PPT full presentation
In which tachycardias electrical cardioversion is ineffective or rather contraindicated ?
Posted in Cardiology - Clinical, cardiology- coronary care, Infrequently asked questions in cardiology (iFAQs), tagged atrial fibrillation, binphasic shocks, bmj, cardiology, cardioversion, ccu, coronary, dc shock, digoxin, heart rhythm, jama, lancet, nejm, pace, svt, ventricular arrhythmias, ventricular tachycardia on September 20, 2008| 4 Comments »
Cardioversion with DC shock offers immediate cure in many of the dangerous ventricular and atrial tachycardias. It is often taught , any hemodynamically unstable tachycardia refractory to medical therapy respond to electrical cardioversion. One should also remember electricity is in fact be called as a drug ! and it should be delivered in proper form and dose. Here it is the paddle size, paddle position and the axis of current flow all are important. Now we have bi phasic currents for better efficacy.

While it is true, most of cardiac arrhythmias respond to shock, there are few which do not respond or respond very transiently.There are few arrhythmias in which ,DC shock is not only ineffective but may precipitate a ventricular fibrillation.
Generally arrhythmias of reentrant etiology respond well to DC shock were interuption of electrical circuit by external current is easily possible. In arrhythmia’s of enhanced automaticity , and ectopic tachycardia it is difficult to extinguish the tachycardia focus with DC shock .
Arrhythmias where DC shock is not going to work are
A. Mutifocal atrial tachycardia(MAT)
B. Digoxin induced arrhythmias.Patients who are on digoxin, has enhanced ventricular automaticity.These patients if they get a DC shock will unmask the ectopic foci.
C. In elderly with atrial fibrillation and sinus node dysfunction it may be dangerous to shock them with out temporary pacing support as sinus node goes for prolonged sleep mode.
D.In electrical storm with VT , if more than three shocks are required within a minute, the VT will most often going to be permanent and the electrical therapy can be termed as a failure. These patients will require intensive pharmacological management( Including magnesium, bretyllium etc)
E. And finally , sinus tachycardia (whatever the rate) is an absolute contraindication for DC shock.
Verapmil is often effective in MAT but correction of hypoxia and acidosis may be critical.For digoxin induced arrhythmias phenytoin may be tried.
What to do when the DC shock fails?
- It will be a tricky situation and one wonder what to do next when the so called universal antidote for cardiac arrhythmia fails !
- Cellular internal millieu is altered by hypoxia and acidosis .It may prevent the effectiveness of cardioversion.So try to correct them .
- Over dirve atrial pacing is one option for automatic tachycardia.
- And now ablation of arrhythmic focus is possible with radio frequency waves in some of these patients.( Diffiuclt as an emergency procedure)
Categories
-

-
The contents of the this blog is being published as Kindle E book , as per the request of many of the readers. Every article will continue to be open source in this site. Again I shall reiterate the book format is not aimed at any commercial intent. It is only to facilitate learning in a single book format Here is the link to book
https://amzn.in/d/euhL5vu Archives
- September 2026 (9)
- August 2026 (8)
- July 2026 (6)
- June 2026 (9)
- May 2026 (6)
- April 2026 (11)
- March 2026 (10)
- February 2026 (8)
- January 2026 (8)
- December 2025 (11)
- November 2025 (7)
- October 2025 (8)
- September 2025 (7)
- August 2025 (9)
- July 2025 (10)
- June 2025 (8)
- May 2025 (9)
- April 2025 (7)
- March 2025 (10)
- February 2025 (4)
- January 2025 (9)
- December 2024 (11)
- November 2024 (8)
- October 2024 (10)
- September 2024 (5)
- August 2024 (5)
- July 2024 (6)
- June 2024 (5)
- May 2024 (4)
- April 2024 (7)
- March 2024 (4)
- February 2024 (8)
- January 2024 (6)
- December 2023 (8)
- November 2023 (13)
- October 2023 (14)
- September 2023 (5)
- August 2023 (6)
- July 2023 (10)
- June 2023 (5)
- May 2023 (5)
- April 2023 (4)
- March 2023 (5)
- February 2023 (2)
- January 2023 (7)
- December 2022 (3)
- November 2022 (5)
- October 2022 (5)
- September 2022 (4)
- August 2022 (3)
- July 2022 (9)
- June 2022 (2)
- May 2022 (1)
- April 2022 (2)
- March 2022 (1)
- February 2022 (3)
- January 2022 (7)
- December 2021 (3)
- November 2021 (5)
- October 2021 (8)
- September 2021 (4)
- August 2021 (6)
- July 2021 (6)
- June 2021 (7)
- May 2021 (5)
- April 2021 (4)
- March 2021 (3)
- February 2021 (6)
- January 2021 (8)
- December 2020 (4)
- November 2020 (5)
- October 2020 (7)
- September 2020 (7)
- August 2020 (10)
- July 2020 (6)
- June 2020 (9)
- May 2020 (9)
- April 2020 (5)
- March 2020 (7)
- February 2020 (3)
- January 2020 (4)
- December 2019 (4)
- November 2019 (6)
- October 2019 (3)
- September 2019 (6)
- August 2019 (3)
- July 2019 (1)
- June 2019 (3)
- May 2019 (2)
- April 2019 (2)
- March 2019 (2)
- February 2019 (4)
- January 2019 (2)
- December 2018 (2)
- November 2018 (2)
- October 2018 (2)
- September 2018 (1)
- August 2018 (2)
- July 2018 (3)
- June 2018 (1)
- May 2018 (3)
- April 2018 (1)
- March 2018 (3)
- February 2018 (3)
- January 2018 (1)
- December 2017 (3)
- November 2017 (3)
- October 2017 (3)
- September 2017 (2)
- August 2017 (2)
- July 2017 (2)
- June 2017 (2)
- May 2017 (4)
- April 2017 (3)
- March 2017 (3)
- February 2017 (5)
- January 2017 (3)
- December 2016 (2)
- November 2016 (5)
- October 2016 (4)
- September 2016 (3)
- August 2016 (5)
- July 2016 (3)
- June 2016 (4)
- May 2016 (3)
- April 2016 (6)
- March 2016 (4)
- February 2016 (3)
- January 2016 (5)
- December 2015 (6)
- November 2015 (5)
- October 2015 (8)
- September 2015 (2)
- August 2015 (5)
- July 2015 (7)
- June 2015 (4)
- May 2015 (6)
- April 2015 (5)
- March 2015 (7)
- February 2015 (15)
- January 2015 (8)
- December 2014 (5)
- November 2014 (9)
- October 2014 (7)
- September 2014 (9)
- August 2014 (5)
- July 2014 (11)
- June 2014 (5)
- May 2014 (4)
- April 2014 (5)
- March 2014 (8)
- February 2014 (8)
- January 2014 (5)
- December 2013 (7)
- November 2013 (7)
- October 2013 (14)
- September 2013 (12)
- August 2013 (15)
- July 2013 (15)
- June 2013 (15)
- May 2013 (15)
- April 2013 (15)
- March 2013 (15)
- February 2013 (15)
- January 2013 (15)
- December 2012 (15)
- November 2012 (15)
- October 2012 (15)
- September 2012 (15)
- August 2012 (15)
- July 2012 (15)
- June 2012 (15)
- May 2012 (15)
- April 2012 (15)
- March 2012 (15)
- February 2012 (15)
- January 2012 (15)
- December 2011 (15)
- November 2011 (17)
- October 2011 (17)
- September 2011 (17)
- August 2011 (21)
- July 2011 (20)
- June 2011 (17)
- May 2011 (15)
- April 2011 (17)
- March 2011 (25)
- February 2011 (20)
- January 2011 (20)
- December 2010 (18)
- November 2010 (21)
- October 2010 (21)
- September 2010 (25)
- August 2010 (20)
- July 2010 (10)
- June 2010 (11)
- May 2010 (19)
- April 2010 (16)
- March 2010 (14)
- February 2010 (22)
- January 2010 (18)
- December 2009 (20)
- November 2009 (20)
- October 2009 (3)
- September 2009 (21)
- August 2009 (19)
- July 2009 (12)
- June 2009 (12)
- May 2009 (11)
- April 2009 (15)
- March 2009 (21)
- February 2009 (4)
- January 2009 (12)
- December 2008 (13)
- November 2008 (9)
- October 2008 (22)
- September 2008 (20)
- August 2008 (16)
- July 2008 (14)
- June 2008 (7)
Blog Stats
- 6,747,930 hits
Please give your feed back .
Click below to see who is watching this website live !

- This site will never aim for profit. Still ,this donation link is added at the request of few visitors who wanted to contribute and of-course that will help make it sustainable .

Please Note