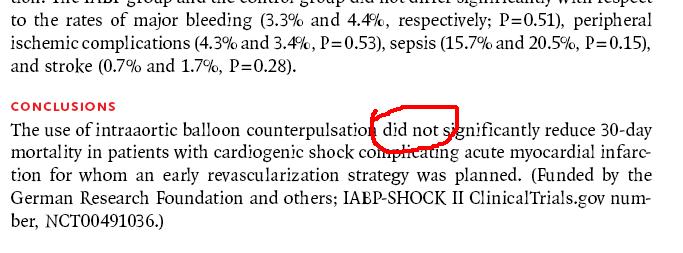Feeds:
Posts
Comments

The primary determinant of pulmonary artery systolic pressure is . . . ?

  1. Pulmonary arterial tone
  2. Pulmonary venous pressure
  3. RV contractility
  4. Pulmonary blood flow

Answer : All of the above

But what is the relative contribution of each ?

I am  100 %  sure  ,  no  one can answer this question  correctly !

It is  true  , in some  pathological situations  one can  be  fairly certain about  cause of   elevated pulmonary arterial pressure .

When we confront a patient  with left heart disease  it is the transmission of  mean venous pressure .

Whatever be  our understanding ( Pre/Post capillary pulmonary hyper tension and the related stuff !  ), the one parameter that makes mystery contribution  to PA pressure is RV contractility !
In physiology  RV   generates  about 30mmhg systolic pressure that becomes the  pulmonary systolic  pressure .The  diastolic pressure  will be around 15 and mean around 20 . During exercise  contractility of both RV and LV increase .There has been documented PASP up to 50 mmhg in normal healthy adults during   exertion .

Here one can assume RV contractility is causing  a entity called transient Isolated  systolic  pulmonary arterial  hypertension.(ISPAH)

Consider a entirely different situation

A patient with COPD  with raised  PASP .  The right ventricle pressure has to equilibrate with PASP  during systole .For this to happen   it has to generate the 60mmhg .  If the RV fails  to augment it’s contractility for some reason ,  will the  ineffective RV contraction will  lower the  PASP  ? This is the perplexing question !

While the popular understanding is ,  RV dysfunction will under- estimate the severity of   pulmonary hypertension   . . . still  . . .  we are not sure whether RV dysfunction will  reduce the PASP   per-se  ( and  subsequently PA  diastolic pressure as well )

We often see a  good example  . A patient who develops tricuspid valve disease and RV  dysfunction get symptomatic relief  from  lung congestion .

Final message

The relationship between RV function and pulmonary artery pressure is a real enigma. Though hyper functioning  RV is expected to elevate PASP  and hypo functioning  RV would pull  it down  , the relationship  is not that simple. If only we decode this  mysteries   we can try  specific  RV negative inotropic  agents  as a  modality to treat pulmonary hypertension .

After thought

Total artificial hearts  are going to come in a big way in the coming decades .It  will specifically address this issue  ,  as RV and LV contractility  need to  be individually tuned to avoid pulmonary congestion.

Coming soon

While  RV function is critical for human survival  ,  Fontan  principle  simply says entire RV is dispensable . How ?

I was stunned to read this article regarding the proliferation of open access , author paid scientific literature   from “The Hindu ” dated 27th  September 2012 .

It only shows how the scientific world is being consumed by  commercial interests .

It seems at every level of journal creating and publishing  there is vested interest .

I wonder   peer reviewed journals  could mean nothing in the near feature .

Let us   join the new movement  called  “Paid science”

What   are the factors other than EF %  that determine  functional capacity in cardiac failure ?

In our experience we have found the following factors  contribute immensely to the functional capacity of cardiac failure patients

  1. LV  filling  defects  (30 % of DCM have significant LV relaxation defects )*
  2. Integrity of  RV  function
  3. Mitral valve  competence(Even a mild MR can be important .It lowers the threshold for pulmonary congestion  )
  4. Severity of Pulmonary hypertension
  5. Lung Function *(Restrictive PFT common , gross cardiomegaly can reduce lung space )
  6. Basal exercise capacity .
  7. Skeletal muscle  function (Mitochondrial training )*
  8. High body weight
  9. Will power and self esteem *
  10. Spouse support and motivation

* May  have  major Impact on functional capacity

Final message

Physicians and even cardiologists are   obsessed  with EF %  to a large extent . My guess is , it   is not likely to end in the near future . The irony is ,  we have passed it  to our  colleagues  (Like anesthetists !)  and patients as well .(  for various reasons )

                        Please remember  , there are at-least 10 factors  that are  important  in the genesis of  symptoms of heart failure  . The list can extend  further  if we include  like associated renal  dysfunction , hemoglobin concentration  , etc .

Even though LV pump primarily determines  the ultimate outcome in cardiac failure ,  it is unwise  to  blame the EF %  for all the suffering  . If only  we realise this fact , one  can take  appropriate  measures .

**   Paradoxically modalities aimed to improve LVEF by positive inotropics has never been shown to improve the outcome .In-fact , there is more evidence for the contrary !

Ironically  , in medicine we need to peep into the  past for updating and scrutinizing current knowledge .   Here is free ticket for   a  retro journey   to  the  the Electro-physiology Laboratory of  the  University of Wisconsin-Milwaukee  .  This article  , which was published in 1990 ,    still  can explain many  intriguing   concepts  of VT succinctly .

Thanks to   circulation  for sharing this article free !

Akhtar M . Clinical spectrum of ventricular tachycardia. Circulation 1990;82:1561-73.

That’s how  one of   the patient  presented  to our hospital .  An echo documented  severe aortic stenosis with a  peak aortic gradient of 80mmhg  and  a  bounding  systolic blood pressure of  180 mmhg . Is that an exception ?

I recall the early days of medical school when  we are fervently   taught  that  systolic  blood pressure is primarily determined by stroke volume and LV contractility .

The above example clearly proves this  is  explicitly wrong  .

Now , we understand  systolic blood pressure have many determinants   . Stroke volume is  just one of them .

The tone  , distensibility  of major blood vessels arising from aorta determine how a pressure wave is going to get amplified .

If you  say stroke volume is not  major determinate of systolic blood pressure   . . . .  does it  imply ,   the antique  bed side cardiac sign  Pulsus parvus  et- tardus  a myth ?

No ,  it still holds good . But it is not a hard sign .  We realise now , a patient with a well felt carotid can have a severe Aortic stenosis .

  • Pre- existing systemic hypertension is a  valid explanation.
  • The other popular explanation for  loss of systolic decapitation due to associated  aortic  regurgitation   may be  acceptable . (Not really proven though ! )

What will be the central aortic  pressure  in critical Aortic stenosis ?

It is definitely lower than brachial cuff pressure .This will explain the systolic blood pressure is actually an amplified signal .

Rescue PCI rescues

  1. Myocardium
  2. Patient’s life
  3. Both
  4. None
  5. Cardiologist pride

Answer:

All of the above can be a correct response in varying situations.

Which is  the most important factor that determines thrombolysis failure in STEMI  ?

  1. Thrombus load .
  2. Drug efficiency
  3. Time delay
  4. Presence of a mechanical lesion
  5. Hemodynamic instability

Answer : 3 .(Though all 5 factors operate )

Failed thrmbolysis occur in about 40-50% after streptokinase and slightly less with TPA   and TNK-TPA . Delayed arrival and late thrombolysis are  most common cause of failed thrombolysis. As the time flies , the  myocardium gets damaged and the intra coronary  thrombus gets organised .Both these processes make delayed thrombolysis a futile exercise.

               Not all STEMI patients have large thrombus burden. There need to be a critical load of thrombus for thrombolytic to be effective

Some may have a major mechanical lesion in the form of plaque fissure, prolapse and it simply blocks the coronary artery mechanically like a boulder on the road  . The poor  streptokinse  or the rich Tenekteplace !  nothing can move this boulder .The only option here is emergency PCI .

How will you know when the patient  arrives in ER with STEMI whether his/ her coronary artery is blocked with soft thrombus or hard mechanical boulder ?

It is impossible to know.That’s why primary PCI has a huge advantage.  But still thrombolysis is useful as some amount of thrombus will be there in all patients with STEMI.Lysing this will provide at least a  trickle of  blood flow that will jeep the myocardium viable and enable us to take for early PCI.

Final message

The commonest cause for thrombolytic failure is the time of administration and the degree of underlying mechanical lesion  . So  it does not make sense  to blame  streptokinase always !

The right to left shunt  in TOF  occurs by  which of the the following route ?

  1. RV- VSD- LV -Aorta

  2. RV-  Aorta

  3. RV – VSD- Aorta

  4. All of the above can occur

    Answer : 2   Most shunting occur by direct streaming of RV blood into Aorta . If the aortic  override  is near 50 %  it need not even cross the VSD in it’s  circuit. (Although theoretically all of the above can occur)


The last rites for routine   Swan Ganz catheterisation ( In STEMI ) was  performed  by a  land mark JAMA article  in 1996 .

Now . . .  is the turn for intra aortic balloon counter pulsation (IABP) .

A conceptually attractive concept  was laid to rest in Munich ,West Germany , this week at annual  European society of cardiology ,  Scientific Sessions  .August 2012 .

What a crash for a great  hemo-dynamic  principle    in acute MI which ruled the roost for over three  decades !
Just Imagine ,   how many man hours , millions of  worth of consumables  wasted  . . .  better  not to talk about  associated   aortic injuries .

This is what we call   “premature evidence based harm”

I  wonder  . . .  whether  I am  justified in making this extreme comment .

Please read for yourself  , this early online release alert  from  NEJM .

http://www.nejm.org/doi/pdf/10.1056/NEJMoa1208410

Reference

Connors A, Speroff T, Dawson N, Thomas C, Harrell FE Jr, Wagner D, etal. The effectiveness of right heart catheterization in the initial care of critically ill patients. JAMA 1996;276:  889-97.

http://www.ncbi.nlm.nih.gov/pmc/articles/PMC2352214/pdf/bmj00561-0005.pdf

The principles of pre-discharge EST  

This concept came about 20 years ago (1980s) to risk stratify patients following  ACS to triage early coronary angiogram and revascualrisation. Generally patients are discharged by 5-7 days after an MI  (May be  3-5 days in some hospitals)  . Doing an exercise stress test  early within  2 weeks has not been very popular with many cardiologist even though it was recommended by many guidelines.The type of stress recommended  here  , is heart rate limited sub maximal 70% of  THR (Usually around  140 /mt )  is performed . This is due fear of precipitation another ACS.

Still,  there are definite  advantages for  pre-discharge EST .It help us  identify  high risk  subsets of  STEMI and reduce the  intermediate term mortality .More importantly it  gives  us an opportunity  to  exclude  inappropriate  revascualriations  even without an angiogram . (The well known coronary dogma  ie  if a post STEMI patient performs > 10  METS ,  his  heart carries little  risk  for  future events  still holds good  !)

With the advent of liberal usage of CAG and improved techniques of revascularistion ,  most  patients  directly undergo pre-discharge CAG rather than EST !

Further reading

Does any cardiologist have guts to do a pre- discharge EST after  a successful primary PCI ?

Read a related article in this blog .