Feeds:
Posts
Comments

An awkward  argument for routine EST following primary PCI

Please remember,  primary PCI is not the end of the management of STEMI. Primary PCI is an IRA focused intervention. We need to study other lesions and their the flow pattern as well. Logically we need to do a test for adequacy of  baseline vascularity and the current revascularisation . Simple deployment of  a stent in IRA (without documentation of good flow during exertion ) is not acceptable to believers of  scientific medicine  . Resting TIMI 3 flow conveys no meaning for a patient who is going to be ambulant and active. A stress test will come in handy .

The micro-vascular integrity and resistance following an extensive STEMI is best studied by the adequacy of exercise induced  coronary hyperemia (This is physiologically equivalent to the much fancied FFR in cath lab ) . One can consider EST following a primary PCI as an non invasive substitute for the collective FFR of all three vessels including the IRA that is stented .

Does any cardiologist have guts to do a pre- discharge EST after a successful primary PCI ?

Typical responses would be

  • Why the hell I should do it ?
  • Do you know how risky it is to do a EST early after a primary PCI ?
  • If at all I have any doubt , I would prefer a non invasive PET or Thallium to study the adequacy of revascularisation.

If you think , it is too risky to exert a successfully revascularised patient early after a STEMI . . .   at the same time   argue  to do it in non revascularised patient routinely .  Do we not see a huge irony here ?

Other inference could be . . . we are still suspecting the quality of our revascularisation during PCI !

If  EST is contraindicated after a primary PCI , are we going to advice  these patients against indulging in any activity requiring moderate exertion fearing a stent occlusion ?

. . . What a way to interpret the aftermath  of a   ‘state of the art ‘ procedure called primary PCI !

In science ,  correctness is more important than politeness !

There are many wonderful books for learning clinical cardiology.J.K.Perlof’s clinical cardiology,  Jonathan Abrams , are popular ones. Clinical chapters in  Noble O  Fowler is a  wonderful reference .

My choice for the top slot is  by “Signs and symptoms in cardiology”   by Horwitz and Groves .They wrote this master piece

“

from a relatively  unassuming  US city, University of  Colorado.  Denver .Published by J.B.Lippincott company in 1985.

I am  not sure , any further edition of this book  has come .

Young cardiology residents  must first  identify  good  books    . . . reading comes next !

What to buy this book ? .Try  at Amazon .

http://www.amazon.com/Signs-Symptoms-Cardiology-Lawrence-Horwitz/dp/0397505124

When do you call a infected heart as healed ?

Should the vegetation disappear to call it a cure ?

Vegetation’s rarely disappear following treatment . Very small vegetation may dissolve – 20% . Many times it regress in size .

Often  our aim should be  restricted  to sterilise the vegetation. This invariably happens in most of the patients who receive complete course of antibiotic. But healing and sterilizing is not enough in many vulnerable patients.If the vegetation is large the embolic risk is still there even with a healed vegetation.

So if there is a relatively large  (>1.5cm) vegetation it is always better to remove by surgery.

Interventional  techniques may   soon  allow  capturing these vegetation by basket catheters .When technology is there to retrieve small bits of a thrombus inside a coronary artery it should be possible to remove a large vegetation with temporary aortic filters in place.

Also read

https://drsvenkatesan.wordpress.com/2011/01/12/what-is-the-natural-history-of-infective-endocarditis-vegetation/

Whatever  is your answer .   It will be   far off from the truth .

What causes  Atheroscerosis ?

The perception  that , circulating lipids directly damage  the coronary endothelium is an  ill proven concept.  Isolated hyperlipidemia  rarely leads to full blown Atherosclerois .

If  LDL moelcules  can penetrate the endothelium  , why the circulating LDL  at a normal concentration of 130mg/dl  fail to do so in vast number of humans   as they criss cross the human circulatory system  at-least a  trillion times  every year ?  So , there  must be something else  operating *It requires a high blood pressure, diabetes , smoking or some form of endothelial injury  (That includes chronic Inflammation )  for the  lipids to  enter the sub endothelial planes and start depositing.

The relationship between serum lipids and plaque burden lacks clarity.

* The argument that 130mg LDL is injurious to endothelium  while  100mg  is not  ,  can  easily be disputed !

Usually co -morbid conditions are  relative contraindication  for renal transplantation . LV Myocardial   dysfunction is a  fairly common  association  in CKD.

The uniqueness of   this  LV  dsyfunction is  , there is no primary   myocardial failure . Further  features observed are   . . .

  1. Structural damage is less
  2. LV is not much dilated
  3. Wall thinning is less common , In fact more often than not LVH is associated . (Laplace law at work to reduce LV wall stress !)
  4. The systemic Blood pressure is  well maintained (Chronic HT related ?)

Mechanism of reversible LV dysfunction in CKD

Chronic pressure overload result in After load mismatch . 

(Normally pre-load , after load , and contractility should be  sequentially matching parameters . After load mismatch is an important concept where myocardial contractility is temporarily is depressed due to  lack of adequate pre-load for a given level of after load )

Evidence for reversibility

Very often one can observe improvement of LV function significantly  24 hours after dialysis .The  concept of    uremic biochemical dysfunction is still valid .Though it can not be exactly quantified .

If significant coronary artery disease is excluded , these patients   do well ( after transplantation )  from a  cardiac point of  view !

(64 slice MDCT may be a simple screening test to rule our significant  CAD .)

Final message

How wise it is to do renal transplantation in DCM patients ? .

  • Most patients with LV dysfunction of CKD do well after transplantation .
  • Presence of severe LV dysfunction especially   with  normal  or increased wall thickness should not be a contraindication to  renal  transplantation .

AVRT is  a second commonest cause of  narrow qrs tachycardia.  While , all narrow qrs tachycardia in AVRT must be  ortho-dromic. wide qrs tachycardia in WPW  can either be ortho-dromic or anti-dromic ,

The classical one is the much popular and fancied Antidromic  AVRT . Please be reminded  AVRT can conduct  orthodromically  through AV nodal tissue  but still  become  aberrant , as it travel downwards thorough the bundles   and result in a wide qrs tachycardia .

Among the two which  is more common ?

My observation is  ortho-dromic  wide qrs  AVRT  is  more  prevalent . Do you agree ?

Final message

Not all wide qrs tachycardia  in WPW  is anti-dromic !

The fundamental difference between  accessory pathways (APs) and AV nodal tissue is the former lacks decremental properties . That is  , APs continue  to conduct whatever the  impulse   it receives. (Unlike  the AV node which has a filtering  mechanism , A heart rate sinker / Dampener) . This is what we were taught and we believe in that .

If it is true  , every episode of   atrial fibrillation should conduct with 400-600 ventricular responses . In reality it does not happen .  The usual ventricular rate in AF with WPW is  250-300 /mt .

What happens to the rest of atrial impulses ?

I am sure it must  get   blocked in APs . Of course it is possible the block need not be in a fixed ratio  .It  changes in a  dynamic   manner with  reference to the   refractory period . (Please note , blocks and increased refractory  periods  can be  used inter changeably in most  physiological situations .

Final message

All APs are not dangerous .They do have a   restrictive mechanism in place .This is evident in every patient with AF and WPW syndrome with a fairly controlled ventricular  response  . Hence  one can conclude   APs in WPW syndrome do have a physiological block in most episodes of  Antidromic AF . The cut off  for safe  refractory period is defined empirically as > 250 ms.

Coming to the title  question , Is  there a physiological  2 : 1  block  in accessory pathway  during AF and WPW syndrome  ?

Yes . It seems so !  A WPW  patient who has  just recovered from a  well tolerated AF ,  is  sort of a natural screening test which effectively rules out a future SCD .(Unless of course he has multiple APs with varying RPs  , one for AF other for VF !)

Is that a correct way of reasoning ?  Experts may provide further  input .

A 32 year old unmarried female with rheumatic heart disease   presented with class  3 dyspnea . She had severe mitral  stenosis with significant calcification , subvalvular fusion , and  a LA appendage clot . She had an aortic valve  which showed mild to moderate AR*  was  and  mild  Aortic stenosis ( Peak  Aoric gradient 30mmhg ).LV diastolic dimension was 40mm and systolic 26 mm .LA was huge 48 X 56 mm  EF was 66 % .

* The patient was having three echo reports done in various parts of the state ranging from mild  to severe  AR . I did the echo myself and I  was convinced  ,  it can at best termed as Mild AR . Let us take it as moderate AR for discussion  

To my surprise  , this patient  was   being planned for double valve replacement . (MVR  and AVR ) .

I agreed with MVR since the valve was completely  damaged and neither PTMC or mitral valve repair  is possible.

However  , I was taken aback   , how can  one  plan for a  AVR for mild aortic valve disease ? I  asked the surgeon  ?

The answer was even more a shocker to me .

Since we are  opening the chest for MVR it is better to replace Aortic valve as well . Since  repeat surgery can be avoided .

The surgeon seemed to be very much convinced about this argument .

I asked him ,   is the mortality /morbidity due to DVR is too high  to take a risk .

The LV dimension is absolutely  normal (In fact it is less than normal !)  so  the AR is definitely not significant .

The surgeon was in no mood to leave me . He argued ,  Since the mitral stenosis is severe , the AR is  probably underestimated .   ” We have quiet a few experience of AR worsening after MVR” ? he asserted !

I still fail to  understand  the reasoning of the surgeon .

How is that ,  indication for AVR could vary if it is  accompanied by  mitral valve disease . If the same patient has  isolated moderate AR  AVR is  forbidden  . Poor patient !

By the way , we have problems with our patients as well .I recall an event ,   a  disappointed  patient’s  spouse  arguing  with his the doctor for not fulfilling his Initial  promise of  replacing two valves . We are living in difficult times , I agreed with the surgeon !

Do we have  alternate solutions ?

  1. Assess on table after MVR by TEE if the AR seems worsen proceed with  AVR .
  2. Modern technology might answer .Let us dream  TAVR for rheumatic valve . . . not too far ?

*Transcutananeous Aortic vale replacement .

Final message

Cardiologists and cardiac surgeons should take extra care before finalizing a decision on DVR in any combined valve disease. It may seem  easier to replace two valves . Please spend few moments silently and think about these young men and women  . Valve replacements are  not like replacing  worn tires of your car.  Do not  burden the heart with multiple artificial valves without a real need for it !

The rate of progression of Aortic valve disease following MVR  can be slower than we think . With surgical techniques and  expertise   improving every year ,   repeat aortic surgery may be done safely in selected few ,  in case it becomes necessary !

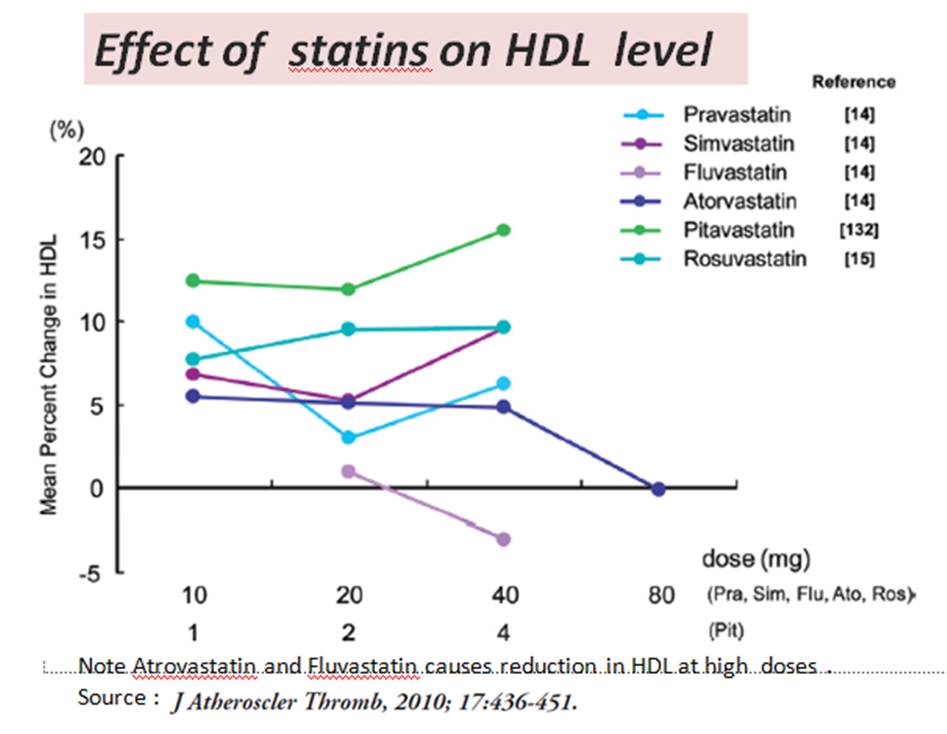
Statins have revolutionised the treatment of coronary artery disease .Intensive lipid lowering is the fundamental prerequisite in the management of both acute and chronic coronary syndromes. One question  is  always difficult to answer , ( rather reluctant to find the answer )  “The effect of statins on the HDL cholesterol”. Logic and the mechanisms of action would suggest HDL is not much affected , but in reality  I believe , in a given patient statins  do  reduce the HDL by at-least 10-20 % .This might have some significance. However ,  the marked  reduction in LDL  may nullify the adverse effects of lowering HDL.   Does this happen in all

What does the scientific evidence say ?

It says the opposite .  It seems  HDL is raised by statins that too significantly . The following paper also  suggests mechanism of  HDL  elevation by statins .It is Independent  to that of LDL reduction , I believe .

This JAMA article  adds more evidence

http://jama.jamanetwork.com/data/Journals/JAMA/5100/jpc70001_499_508.pdf

This paper  from  the  premier  Journal  of   Lipid research  agrees  to the   mechanism of  HDL reduction by statin  is a complex process  but still  it vouches for it .

http://www.ncbi.nlm.nih.gov/pmc/articles/PMC3035518/?report=printable

In spite of  all these  evidence . . .   it  remains a  huge suspect . . . from my personal point of  view ( My patients are  my evidence !  )

Coming soon

The above articles also raise an important  concept of dysfunctional HDL.  Simple raise  in HDL is not suffice . . .it should be functional as well !

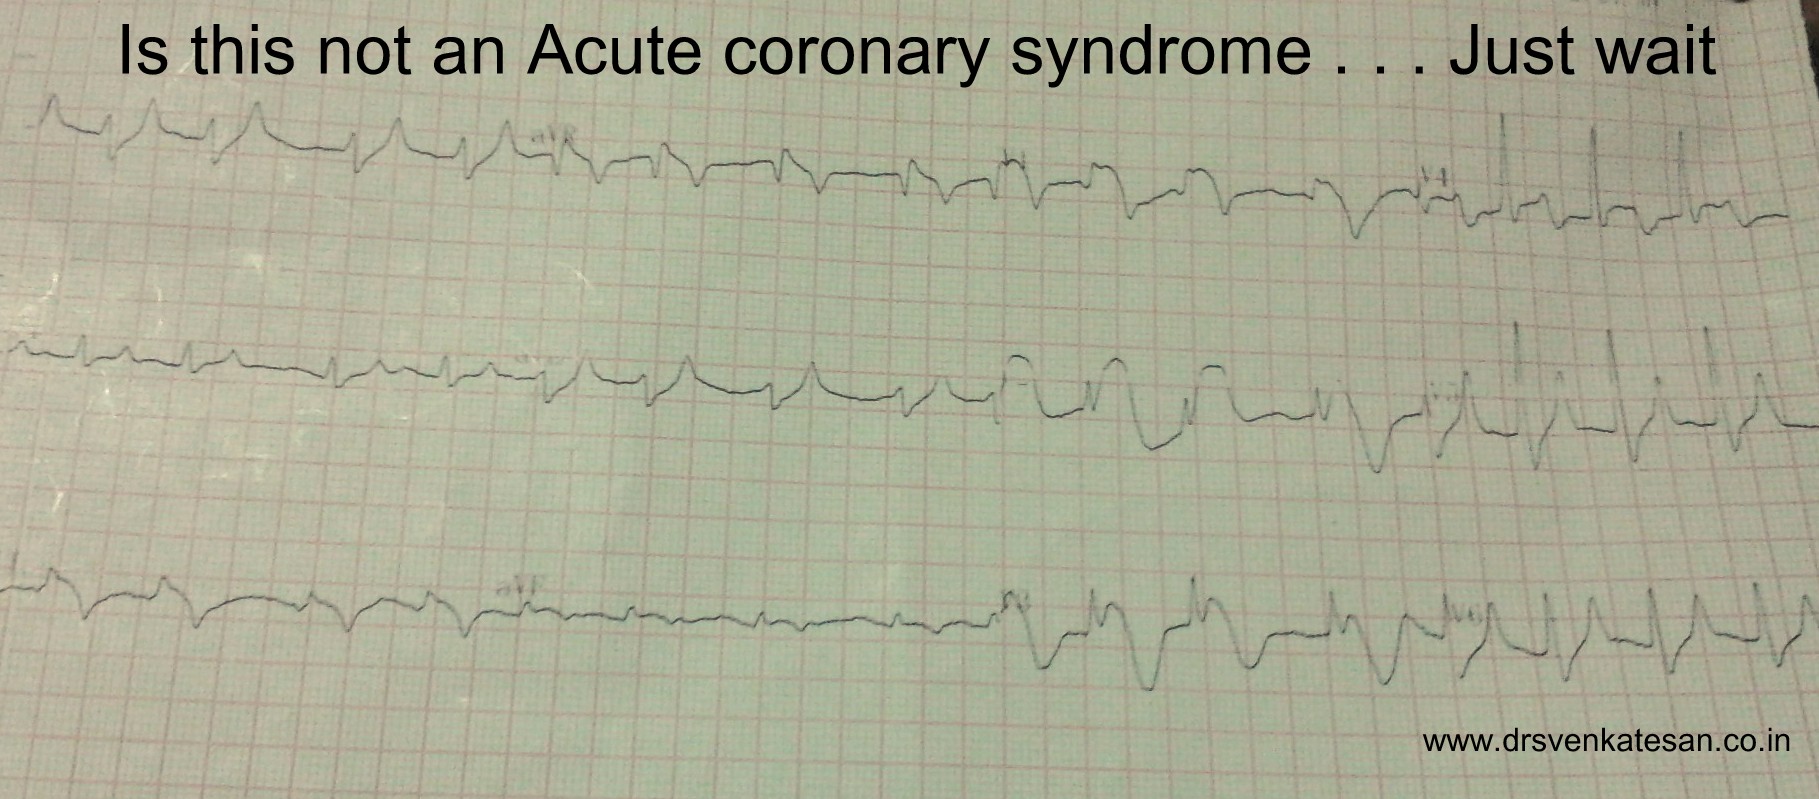
A 38 year old man presented with  acute breathlessness  and chest pain .His ECG is  posted  below . The ER in charge   medical officer promptly handed over the patient to   STEMI  alert    group (This is how  cardiologists are   referred to !   in one of the leading corporate hospital in India )

Note Atrial fibrillation , ST segment elevation, in pre-cardial leads

A team of  white coated  humans  in  various  gender and ages  swarmed the patient . ECGs and text where shared  among  the  STEMI alert group  through  I pad 3 which transmitted  HD  quality ST elevation with a  retinal  precision . A senior consultant   insisted   to shift the patient to cath lab direct  . Since he had  signs of cardiac failure , one of  the wise Junior fellow wanted  to correct the failure with Nitroglycerine  and  Dobutamine before rushing him to cath lab . Hence he was put on hold in the side room of ICU .

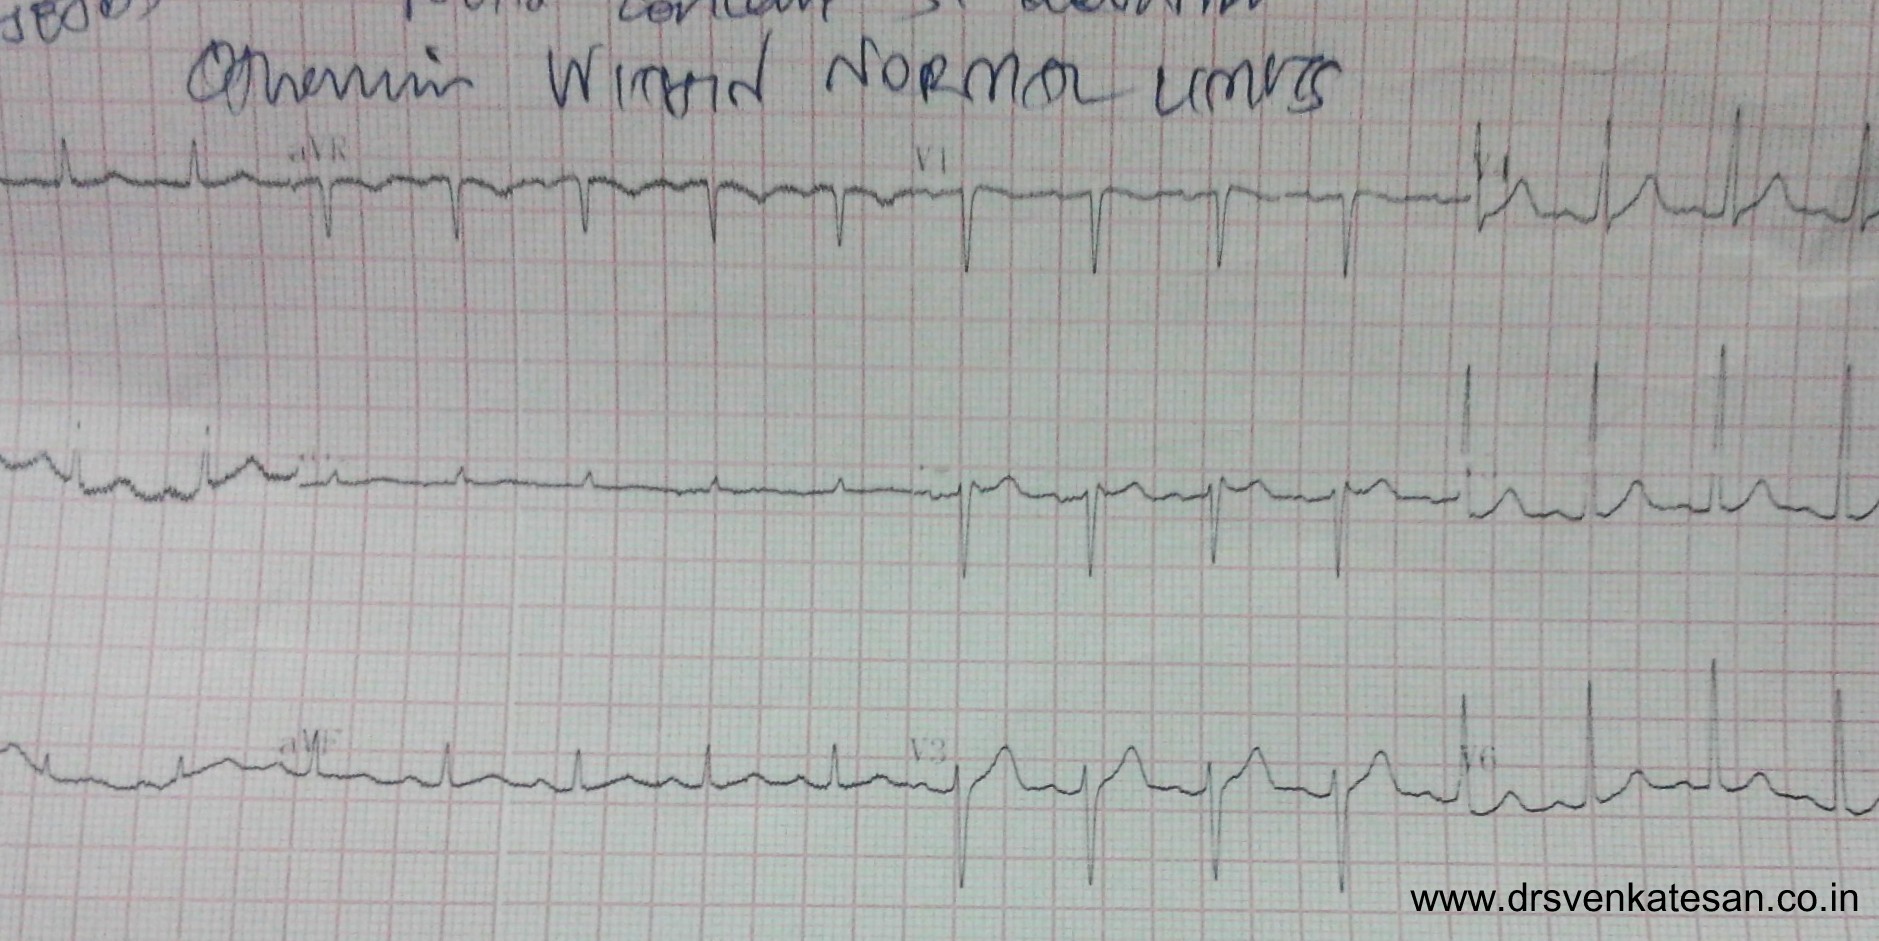
Echo examination showed LVH and wall motion defect could not  either confirmed or ruled out .  Initial  Troponin was negative . In the mean time the bio chemistry results came. He had a creatinine of  5.2 and Potassium of 6 meq . Hence the patient was diverted to Nephrology unit  and  dialysis was done. The next day morning  his ECG   looked like this .

It  may  sound a  pessimistic , but  still I would consider   the above  episode  is  a rare  example of appropriate care happening  ! This patient was diverted in a timely fashion from cardiology  care  to the  Nephrology . Please note , it is not the  the  clinical acumen that   helped  here.  If  he had  not presented with  LVF   he would have been a victim of inappropriate care  and landed on the cath-lab table directly  !

Final message

Every moment in clinical medicine is important , especially during the genesis of  diagnosis.  Where the patient lands  . . . in a frighteningly  large  hospital is as important  as the disease process itself. In this scientifically arrogant medial atmosphere  most of us, are  tuned  to view every problem as their own  ! This is  the default mode of modern medical  thinking process . How faulty  we are ?

The future is worrisome  as the field of  Internal medicine is  at risk of dying a premature death (or is it dead already !)

By the  way  what is the mechanism of ST elevation and Tall T waves in hyper-kalemia ?

Many factors contribute .

  1. Is it a true ST elevation  ? There is reason to believe   the tall T waves drag the fag end of ST segment along with it .
  2. Next is  related to QT interval . Hypo-kalemia widens while hypo-kalemia does  the opposite .(  though not classically) .
  3. When QT is shortened the segment gets squeezed in within a limited space ,  in order to accommodate the  ST segment it   gets rolled up and elevated . (Like an up sloping ST segment  in extreme tachycardia during stress  testing)
  4. Whatever  be the mechanism it is something to do with potassium ion flux .Transient intra-cellualr hyper-kalemia.
  5. Another possibility is diffuse uremic peri-carditis , which is a common accompaniment  of renal failure.In fact this patient did have a peri-cardial rub