Feeds:
Posts
Comments

The  OAT   extension study  ,   a  6 year follow-up study on total occlusion following STEMI has just out in circulation 2011  October , online first . http://circ.ahajournals.org

There were two  important conclusions  from this study

  1. Long term follow-up  to  6 years  confirmed  the  lack of benefit of routine PCI  in  post MI total occlusions.
  2. Inappropriately   done  PCIs convert   stable coronary occlusive  disease into potentially dangerous subsets  with  risk of re-occlusion (Which  could  very well be an acute coronary syndrome )

The second one is  of critical  important than the first  .In a nut shell ,  it  suggests  routine PCI in  CTOs  could  increase the   risk of ACS many fold in other wise stable patients.

Final message

This OAT extension study  should  not experience the same fate  of  COURAGE and OAT -1  which  were  successful bitten and buried  by most  interventional cardiologists.

This time they   have to  swallow  the  unpalatable truth ! If they don’t ,  our  patients  would be the ultimate  losers and

will pay the  price dearly !

Personal foot note :

One of my colleague asked me  . . . Why am I  always  after the Interventional   cardiology  community !

I said ,  it is not my job to pull down any one group.  I am just exposing   the  irony of  “selective usage” or “selective  neglect”   of scientific  data by many of us !

The other day when  I was  observing  my colleague   puncturing  the inter atrial septum  with heavy bore needle  during a PTMC  procedure  the patient   was  comfortably watching and   enjoying   the procedure .

Even as  multiple wires  criss-crossed  the left atrium  and  the  balloon  hitting  the mitral valve repeatedly   there was  absolutely no pain.

Next day ,   in an another  patient  when IAS was punctured  it got stained  along with pericardium  ,  the patient had   severe  back pain and procedure was  to be  stalled temporarily  .

What  is the lesson learnt  ?

The pericardium and the epicardium (same as visceral pericardium )  has rich  pain  fibers. The above  patient  who had  stain  of epicardium had severe pain .

The former patient who had a perfect IAS puncture did not develop pain while the  later  who  had an  epicardial track   experienced pain.

The same analogy can be seen in patients  with myocardial rupture .While  sever chest pain is a rule  with a free wall tear , it is very rare for  patients with ventricular septal  rupture  to complain  sever pain as  IVS   rupture do not cleave the epicardial layers  .It is also uncommon for papillary muscle or chodal rupture to generate  significant pain .

What is the difference between  epicardium and endocardium in terms of pain fiber  innervation ?

Sub- endocardium has less  dense nerve supply than sub-epicardium. This is one more reason why isolated sub-endocardial  stress  less commonly result   angina ( Eg Hypertension and sub endocardial strain  often silent  ) while  even minimal irritation or insult of sub-epicardium induce severe  pain.

Further , cardiac  pain receptors   respond differently to type of stimuli  .The density of these receptors also  vary depending on planes of myocardial  tissue  .

What are  triggers for cardiac pain ?

Any of the following can trigger cardiac pain.The pain receptors in heart are not well developed as that of somatic system.

It is not clear whether the layers of heart has specialized receptors for various sensations.

  • Stretch*
  • Prick
  • Guide wire poke ,
  • Needle prick
  • Temperature .
  • Infection ,
  • Inflammation of  myocardium , pericardium*
  • Pressure injections
  • Cardiac ischemia*

*  These  three factors   are responsible for bulk of the cardiac pain . Please note needle prick on the heart is least painful !

How does ischemia   generate pain ?

The ischemia of myocytes secrete

Bio chemical

Substance P ,  prostaglandins, serotonin, adenosine, bradykinin,   and other mediators are involved

Neural

Carried by  myelinated A-d and unmyelinated C fibers run in the cardiac sympathetic nerves . It is understood ,both the fibers  respond to mechanical stretch while Type C fibers also carry chemo signals from bio chemical mediators as well .

Vagus  nerve has a major role in carrying  afferent signals of pain . It is  well known ,   if pain stimuli  is substantial the vaso vagal reflex is activated and bradycardia  and hypotension  occurs.

How is infarct pain different from Ischemic pain ?

Necrosis of nerve terminal will result in more intense pain and lasts longer .

Clinical examples for stretch induced cardiac pain

  • Acute RV/LV dilatation of any cause
  • Pulmonary artery/Aortic dilatation
  • Pericardial stretch could contribute more in generating this   pain
  • Mitral valve prolapse (Stretches  LV free wall )

Interventional  cardiologist should thank god for not innervating  the heart extensively . This  only allows  us to  spend  hours  together  inside the patients heart , other wise one would require a general anesthesia for doing a PCI

Does pericardium  suffer from  ischemia or necrosis ?

Pericardium is not an  avascular  structure . Pericardium gets its blood supply from twigs  of LIMA and phrenic arteries.So there  must be some impact of ischemia on pericardium . Since pericardium has  rich nerve supply there  is every reason to suspect existence of ischemic  pericardial  pain as well .

But  pericardial pain induced by   mechanical stretch  and inflammation is much more common  .While acute pericardial stretch is painful chronic stretch as in slowly accumulating    pericardial effusion is  a painless event !

Pain relief  after CABG

One of the reasons for angina relief  post CABG is attributed to the interruption to  pericardial nerve supply.

Reference

This 1957 article from circulation still  rules cardiac pain literature . http://circ.ahajournals.org/content/16/4/644.full.pdf+html

http://www.annualreviews.org/doi/full/10.1146/annurev.physiol.61.1.143


V wave  is one of two positive  upstrokes   seen  in JVP.  Physiological  “v” wave is due to  atrial filling  and reaches the peak at late  systole , while pathological ” v” waves  are often  due to tricuspid regurgitation  . It is  a mid systolic wave .It is a fusion of  “c”and “v” waves .

Here is a patient  with dilated cardiomyopathy with severe tricuspid regurgitation  who presented with prominent neck veins.

there is no difficulty in identifying the  v wave . Careful acuity will reveal  a  sharp  “a”  wave as well !

JVP pressure wave form of tricuspid regurgitation showing classical systolic cv waves

How to measure the amplitude of  v waves ?

In JVP,  there is a baseline oscillating column . Individual wave  spikes  occur over and above this baseline . Hence  technically there  should be two measurements  , but we take only the  top most part of the oscillating  column.

What is the indirect evidence for tall  v waves ?

Physiologically “y” descend is  integral part of v wave (In fact ,  “y” descend  can be referred to as down stroke of  “v” wave )  .For every  tall “v” wave  there  must be  a prominent  “y”descent . (Probably  constrictive pericarditis is an important exception ! )

If  “y” descend is not rapid but shallow one can suspect two conditions

  • Tricuspid stenosis
  • Significant RV dysfunction

How to differentiate v waves from a waves ?

“V” wave  is a passive filling wave hence it raises  slowly , has  relatively   shallow summit and  occurs in   mid or late-systole  . “A”waves are  due to active contraction of atria . It is a  sharp pre-systolic wave . One practical way to recognise   “a” wave is ,  it  never stays in the eye , it just flickers.  If your eye sees a sustained wave for more than  a fraction of  moment it can not be  “a”  wave ! Another point that may be useful is  “a” is taller than “v” in  right atrium .

Reference

Click below to hear the murmur of TR (Courtesy of Texas heart institute )

http://www.texasheart.org/Education/CME/explore/events/upload/HSPS13_TricuspidInsuff.mp3

Proximal LAD lesions require  specific and early Intervention.Hence we need to know what exactly  we mean by proximal LAD disease.Unfortunately , it means different things to different cardiologists .There is no dispute regarding the  origin of  LAD since it begins with bifurcation point  .The problem comes with  this question !

Up to what distance LAD can be termed as proximal ?

  1. Bifurcation  to   “First   diagonal” of  any size
  2. Bifurcation  to   “First Major diagonal”
  3. Bifurcation to     “First septal”  of any size
  4. Bifurcation to    “First  major septal”
  5. Bifurcation  to   “Any major  first branch ” (Either septal or diagonal )

Answer : I think  4 is the correct answer . But many believe  5 can be correct as well !

Why  there is  confusion in the  definition of proximal LAD ?

This is because the first branch of LAD itself is not a  constant one  . It can either be a septal  or  uncommonly  a diagonal.

It should be noted , the septal and  the diagonal  branches  neither respect   seniority  nor follow a  hierarchy .The first diagonal may be diminutive while the   second or third diagonal may be major one  and vice versa .Further  ,  there can be a trade of  in length and caliber of   septal and diagonal branches  .This  phenomenon is also  common between  diagonals  and   OMs  . All these confound the picture .

Cardiologists even though they are  primarily physicians they are  pro-anatomy  like surgeons when it comes to coronary interventions .

                                  In the strict sense ,  we  need to differentiate a  lesion  from being   physiologically proximal  or anatomically proximal  !

Is there a proximal LAD equivalent ?

There are three  situations  this can occur .

  • Some times a lesion  by  definition may not fit in  as proximal  LAD  but physiologically  few major diagonals  will arise after the lesion.
  • Other situation is , LAD lesion may be  mid or distal but  a major first  diagonal may be diseased  , making it  equivalent  to proximal LAD in terms of physiology.
  • A mid LAD  with a large OM lesion which is running in the D1  territory

Final message

It is ironical  millions of cardiology interventions happen  for proximal  LAD lesions  every year without  even  proper understanding of what we mean by  it ! Youngsters are argued to ponder  over this issue whenever  they indulge in  such cases for revascularisation!

Reference

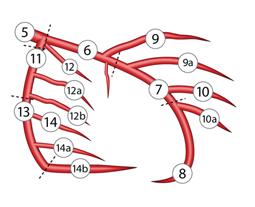
Text books differ in their definition about proximal LAD. Currently , the  SYNTAX  scoring system  has defined the coronary segments in a practical way.

http://www.syntaxscore.com/index.php?option=com_content&view=category&layout=blog&id=1&Itemid=32

Definition from SYNTAX

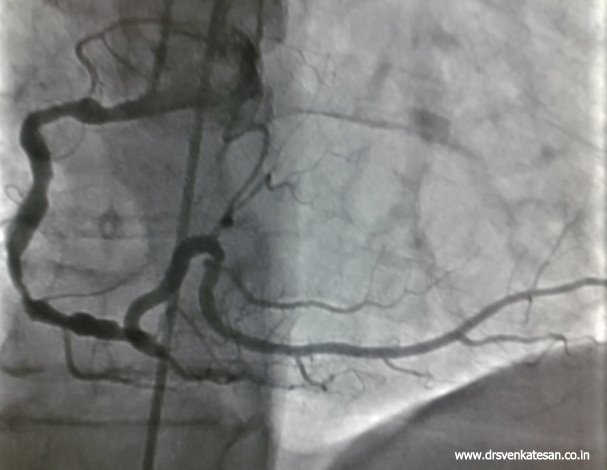
This is an  RCA of   a  patient who had chronic stable angina  , class 2  with moderate anti anginal medication.

What shall we do ?

  1. The RCA needs  multiple stenting
  2. Multiple plain balloon angioplasty
  3. CABG to PDA
  4. No intervention ?
  5. It depends upon status of LAD  and LCX

The correct response would be 5

Without knowing  the status LAD and LCX . . .  RCA should not be touched . Further,  the concept of tackling  the  coronary artery  by itself  is   fundamentally wrong !  We are supposed to tackle patient’s symptom ,   reduce future risk of  events and   not merely  their coronary artey !

His LAD and LCX was near normal. In the weekly  cath   meet   PCI to mid RCA  covering  the critical segment was  strongly debated but  lost a close race .

The final decision was to allow the patient to continue   intensified   medical management (Statin 80mg /Metoprolol 100mg ) . He is comfortable with that .

Medical management  in a tight  single vessel disease  can never be digested by  any   Interventional cardiologist  whatever   may be  the guidelines !

Final  message

Do not decide PCI on the basis of   how ugly a coronary artery looks , rather spend some time on true  symptomatology ,  optimise baseline therapy  and re assess risk profile

One learned dictum is ,  do not  meddle a RCA ,  however severe the lesion may be   if  LAD and LCX are fine.*

*This  rule is not applicable in ACS

If  we   think we have  unraveled  all the  mysteries  of   human coronary  blood flow   we are  sadly  mistaken . Most cardiac physicians spend  their  prime life  in opening the  obstructed coronary arteries  playing  a role of coronary plumber.

Like any plumber ,  it is not going to be  one time job and   our patients  would  have to hire their  services  periodically  . Many times  it turns  out to  be a 108/  911 call  as well !

Unfortunately , hem0dynamics  of  coronary blood flow  do not follow  the principle of  water flowing across  a domestic  pipeline.The most dramatic   difference  between  the  coronary blood flow and   water pipe  is ,   in the later  ,   as  the water is being ferried   across the house  ,   neither the building   nor the   pipe    contracts    (Unfortunately all our understanding , derivations and research were  based on simple physical  modules  of  hydrodynamics in a static  delivery  system )

Pressure flow relations especially in biological system is  not  simple. Since  our  foundations on principles of   blood flow  is based on this simplistic model  ,  every assumption  could be proven  wrong. This  is what  is happening now . Nothing seems to work  in a  learnt  manner.

A patient  with  100% occlusion  walks comfortably  without damaging his muscle.While an other patient  would  develop cardiomyopathy even if the occlusion is  gradual   and  incomplete  ! Hemodynamic  logic tells us blood flows from high pressure to lower pressure  zones  like a water fall !

But coronary waterfall is not a simple and smooth affair. It is not a free fall  ,  even as the water falls there are  pumpy  interruptions .When these  pumpy ride  occur  even in physiology one can imagine  the pathological states  , when  the coronary  artery is blocked ,  the myocardium is  scarred and the systemic blood pressure fluctuates .

While every  organ welcomes   the systole  ,  as they are fed  with  blood  during this time of cardiac cycle  . Heart  is only organ which sacrifices  its own blood flow during this phase  as the systolic contraction  interrupts the blood flow .

Determinants of coronary blood flow

What we learnt over the years has been too simplistic. It is not the  patency of vascular  system that matters. The coronary micro vasculature, the metabolic demand, the neuro  humoral regulation etc.  For  most cardiologists  the epicardial  patency   or stenosis remains the only relevant  issue

The reality is  much complex  to comprehend

  1. The coronary perfusion pressure
  2. Coronary flow reserve
  3. Coronary wave forms
  4. Sub endocardial vs subepicardial flow ratio
  5. Effect LVH on myocardial flow
  6. Coronary venous tone and arterial ischemia.

Now,  we have an entirely new concept which proposes (Rather proven concept !)   the  integrity of  myocardial contraction and relaxation on the coronary blood flow. This land mark paper in circulation has identified  six wave forms of coronary blood flow This include 4 positive  waves and two negative waves

Questions need to be answered 

During diastole  myocardium relaxes . Only if  the myocardium  relax   optimally  the compressive effect of systole  on coronary  coronary   micro vasculature is reversed  ,  intra coronary resistance  falls so that coronary blood flow can occur smoothly. We do not know  whether diastolic dysfunction would  affect the diastolic coronary filling waves  jeopardizing the coronary flow.

Myocardial viability is important for one more reason  , in the distribution  of   coronary blood flow .A dysfunctional muscle can not receive  and  inject  the blood  deep into  sub  endocardium (Note this becomes  important  when  revascularising   severely  dysfunctional segment )

Does myocardium has a  calf muscle analogy   and  behave like  a  powerful  intramuscular perfusing pump .

A breakthrough concept  from Davies et all in circulation .  These are not new ( Buck -Berg  ?)thought  about this decades ago .  The interest is rekindled in recent years  ,  as  complex angioplasties  following myocardial infarctions  failed  to improve outcome and relive symptoms in many .

During primary PCI ,  no- reflow  often  denotes a meaning  of  failed  PCI .The issue involved  is  hydrodynamics of intra myocardial  blood flow .The following  article partly  answers the  issue  underlying no re flow .http://circ.ahajournals.org/content/113/14/1721.full.pdf+html

Final message

Young  physicians  need to  spend  more time  in  basic  cardiac sciences . Lest, what  we  do  in cath lab blindly  will become a laughing stock  ! We have to go back to the golden years of  research in cardiac physiology  (1960 -1970s)  . Mastering coronary  angioplasty  may increase the blood  flow  up to the  myocardium ,  but pushing the blood beyond the muscle requires more sense  and effort .

A simple  hemodynamic  model based  on  physical  principles alone is a  greatest error we make in cardiac science . * Further, human heart muscle is not only influenced by the quantum of blood  it receives  but to the great extent the content of blood.The blood caries all the ill effects of  systemic diseases and  damage   the vessels and muscle .The interaction  between the  blood and  the muscle  is never  an issue in  the pure  physical labs .( Even animals misbehave !)

Human coronary circulation stands  unique among  others as it is a   life-sustaining circulation.It is  considered   a great  medical achievement   to visualise   the right and left coronary artery  system by coronary angiogram.  Actually  what we see is   only  a  fraction   of  the surface area  of  coronary circulation . The surface area of  epicardial coronary arteries   constitutes  less than 5 % of entire coronary vascular tree .

This  is the reason  normal coronary angiogram can never mean normal  coronary circulation !

This huge gap in our perception is the single important factor  that  explains the vagaries  of modern coronary care .

This also  make any coronary  scenario  a  reality .

“A patient with normal coronary angiogram getting a myocardial infarction the next day and a severe triple vessel disease living comfortably with medical management”

So ,  it is essentially a   false  sense of  scientific accomplishment   by the  cardiac scientists  at  least in the  of coronary circulatory physiology.

There are innumerable channels of micro vessels traversing across the heart, sharing , bridging , branching, penetrating  and  perfusing the muscle mass.They can be anatomicaly patent , physiologically non patent .They can be recruited by hemodynamic stress . It is also influenzed by  favirable growth milleu and hormonal and neural stimuli.

What determines the extent of these invisible circulation ?

and

An in vitro heart with special catheters showing the true extent of coronary circulation: Courtesy http://eurheartj.oxfordjournals.org/content/28/3/278.full.pdf+html

Why many cardiologists   do not give due credit  the   coronary collateral  circulation  ?

Right from the days  of  Levine in 1970s( Who made a seminal contribution  about coronary collateral)  the  utility value of  coronary  collateral  circulation   was  never able to convince the cardiology professionals .

It has been our traditional  teaching ( without much evidence of course  !) coronary collateral circulation  is not effective to support blood flow during exercise . This fact has been  disproved  many times . Coronary collateral circulation was indeed useful in limiting damage in ACS and  relieve symptoms in stable angina.It helps  in reverse remodeling and provided electrical stabilty as well in post MI population.

Still  the concept  was  alienated  and   made   totally irrelevant  in the interventional  era  . Many   cardiologists  found well-developed collateral’s as an interference to their expertise and ego since it has a potential to alter the indication of PCI.They  continue to have  strong  scientific conviction (Pseudo ?)   that man made collaterals must always been superior to God made collaterals !

Whenever  some credible  reports emerge about  collateral circulation   being   equivalent to  revascularisation procedure , these concepts were  prematurely buried for some reason.

In the last decade there was a concern  about  performing  PCI in patients with well-developed collaterals  .The argument was , they tend to develop early stent occlusion and restenosis . It  was a genuine  query  raised by few thought leaders in the field as  collateralised vessels  suffer from  low flow states  after PCI ,   if the pre -existing collateral continue to function.

But then , few  studies countered this  , and   said PCI  is safe and  in fact may  fares well   in  patients  with  extensive collaterals .

In these  studies  interventionist’s  argument looked  amusing !  as they  seem to  define a  successful  PCI  as  not only to open the occluded vessel  but also  make sure to close  all functioning  collaterals  .(What a  a pity for our natural biological  angiogenic forces which had  worked  and  grown meticulously for months!)

Cardiac science in the current format,  makes   the future look  bleak for coronary a collateral circulation .With  early PCI  becoming a norm we will never ever allow the natural collaterals to  grow  ,  and even the  established collaterals  will have to face a stiff   fight  for survival  with  sophisticated coronary interventions .

Competing interest in the filed of  coronary collateral   research

While the basic scientists want  to  grow collaterals with angiogenesis ,  stem cells etc  interventionists   continue to  indulge in rampant angioplasties which  will suppress  collateral growth.

This implies we will struggle to  establish  the true  importance of  coronary collateral circulation .

Final message

Can it be an  effective form of revascularisation  ? 

My personal  inference  is   coronary collateral  circulation  “would and should”  have  a definite role  in at- least  some of the subsets  with chronic coronary  syndromes. If we think otherwise . . .    it’s against the principle of  natural biological science .

A good  collateral   system with optimal medical management  can save not only our  patient’s  lives but also  their hard earned currencies !

Reference

Here is a rare article in European heart   journal that discuses coronary collateral circulation  . Let us welcome such wonderful  reviews which keep the interest alive on the filed.

http://eurheartj.oxfordjournals.org/content/28/3/278.full.pdf+html

Is there  an  anginal equivalent  in cerebral circulation ?

Coronary Ischemia produce  angina . . . Cerebral  ischemia do not produce  corresponding   ischemic cerebral pain ! Why ?

Exertional angina  is the dominant  event when coronary artery is  stenosed  . When cerebral artery is stenosed   exertional  head ache do not occur .  So , how does brain respond to  exertional  ischemia ? (EST is also  a stress  to our  cerebral circulation  .  If only we record  EEGs  during treadmill we will  know the truth !)

But in the clinical setting  ,  we are not only surprised by lack of head ache during cerebral  ischemia   , even  exertional   giddiness  is not a common presentation . Instead ,  brain  primarily   respond to ischemia  with focal neurological  deficit instead  of  generating  pain within the skull. This is often referred  to as TIAs .

But,  chronic ischemia  has its effect in the form of lacunar  infarct with its  clinical counter part  – vascular  dementia.

Electrical rhythm  disturbance   like   Ischemic cerebral  arrhythmia are also  known to occur .

The reason for these coronary vs cerebral stenosis behavior is  not clear . Number of possible explanations can be offered.

  1. Paradoxically ,   in spite  of  brain  being a central neurological  command , by itself  has less pain receptors  especially to ischemia
  2. The hypoxic threshold for cerebral cells may exceed many fold to  that of myocytes.
  3. Cerebral  auto-regulation is more developed than coronary regulation.
  4. The circle of  Willis  , though   do not help  much when individual  cerebral arteries are  occluded  suddenly , it does  play  a role in balancing cerebral circulation  at times of chronic  low flow states and  ischemia .
  5. Finally , even in physiology  many of us are comfortable with  little  brain function. One estimate says we  hardly  use   2-3 % of  brain’s processing power (Like our computer  CPU) .Hence  intellectual , deterioration  are  very  late  phenomenon of cerebral ischemia.


Reference 

How often head ache occur in  acute stroke ?

It occurs in less than 15 %  in acute ischemia .( In chronic ischemia it is very rare ? non existent ?)

The exact source of pain is not clear .

A stretch induced pain , dull infarct zone pain, cerebral edema induced transient  ICT may also contribute .

http://onlinelibrary.wiley.com/doi/10.1111/j.1526-4610.2009.01440.x/abstract

It  was a real surprise ,  when I found this journal exclusive for  head aches !


What is the mechanism of vascular head ache ?

It is ironical  ,  more often an excess blood flow by inappropriate vasodilatation that cause many episodes of vascular head ache . These confirm the complexities of  ischemic vs non ischemic pain within the brain .

The answer to this  seemingly innocuous  question is not  that simple at all.  We know ,sinus tachycardia is  a common expression of thyroid  excess while  sinus bradycardia is the  hall-mark of thyroid depletion. So  obviously ,  the first thing that would  strike us  is ,  there must be  something  cooking between thyroxine and the SA node .

We realised much later , there is no direct action of thyroid hormone on the SA node instead it has a crucial interaction with adrenergic system which   has the major influence on chronotropy.

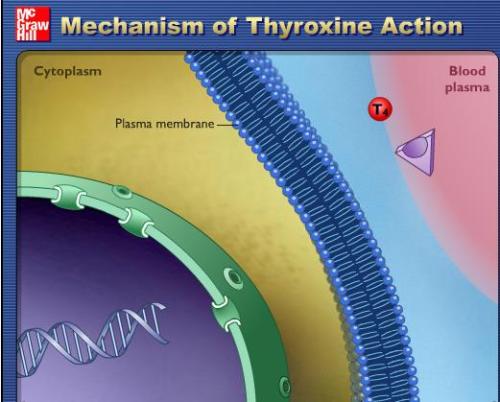
Click on the image for flash Animation (Courtesy Mcgraw Hill )

How does thyroid interact with adrenergic system ?

Thyroxine (T4)  is an inactive molecule , it has to get converted to  T3 for its action. This conversion takes place inside target cells like myocytes, pacemaker cells  (of course  it has action  on virtually any metabolically active cell !  )

The most important point to remember is , unlike catecholamines the thyroid receptors are located  in the surface of  the nucleus  inside the cell , instead of cell membrane . Surprisingly T4 does not require any specialised transporter to enter the cell.It simply diffuses into the bi-lipid layer of cell membrane as T4 is immensely lipid soluble.  . After entering the cell in the cytoplasm it gets converted into  T 3.

This T 3 is attracted towards the nucleus. Once  it is attached to nucleus , it brings about  changes in the gene configuration and  through  messenger RNA results in new protein generation . These cellular  elements are vital for maintaining the  ionic channels and ports and anti-ports.Among these the most important is adrenergic receptor molecule , an its  signal system namely the GTP/Adenyl cyclase/Cyclic AMP units in the cell membrane .

Thyroxine is a physiological hormone  required to maintain these adrenergic  receptor complex on day-to-day basis. (It can be called as cell servicing hormone )

The circulating catecholamine’s  action is  heavily  influenced by the thyroid hormone status.   Sympathetic  nervous system is the live wire for human biological system.  So , when thyroid is in excess the entire metabolism of  cell is increased and vice versa happens.With the close interaction with adrenergic system  , one can understand how thyroid excess causes anxiety state and depletion causes  depression.

Coming back to heart ,

  • Thyroid hormone   up-regulates  beta receptors in cell membrane and augments the action of epinephrine and  result  sinus  tachycardia .It can have positive inotropic action as well (Hyperdynamic  state )
  • Aguments intracardiac  conduction.
  • The action of thyroid hormone on heart can well extend to the pathological phase, where in it can cause multiple ventricular ectopics and atrial fibrillation. (Note the striking similarities between  these arrhythmias   and   adrenergic  arrhythmias !)

What is time frame for  thyroid  hormone action ?

Obviously thyroid hormone can not  have a rapid onset action  since it invites the nuclear synthesis  (Like steroid hormones)  it may take few weeks time for thyroid hormone to express its effects.

How does beta blockers exert its action in thyrotoxicosis ?

This occurs in two ways.

  • The beta blockers occupy the adversely up-regulated dense  beta receptors of cell membrane and  prevents excess adrenergic  action.
  • There is some evidence beta blockers prevent conversion of T4  into T3 .This seems to be less important than its direct sympathetic blockade.

For effective control of thyrotoxicosis one need to administer beta blocker in combination with anti-thyroid drugs.

Will calcium blockers be effective in controlling the tachycardia of thyrotoxicosis ?

No it is not . It may  reduce the heart rate a little but never to the extent of beta blocker. This is another  indirect evidence for  the interaction between thyroxine and adrenergic system.

If thyroid hormone is able to potentate the circulating catecholamine action why not it be used as a

positive Inotropic in cardiac failure ?

A very valid question.  It was tried by many researchers especially in dilated cardiomyopathy. .For some reason it has not worked well , except in patients with  associated with hypothyroid  state.I personally believe thyroid hormone must have  a major role  in chronic heart failure in spite of the fact  we have  proposed sympathetic blockade as concept for regulating cardiac failure.

Human coronary artery anatomy would  rank  top among  all human biological mysteries. The variations in their branching pattern is next only to palmar creases and cerebral gyri !

The left coronary artery can divide in to two , three  or even four branches occasionally.The trifurcation  occurs in upto 20 % of population .The ramus intermedious  can some times be a major division .Usually it supports the diagonal or OM territory.

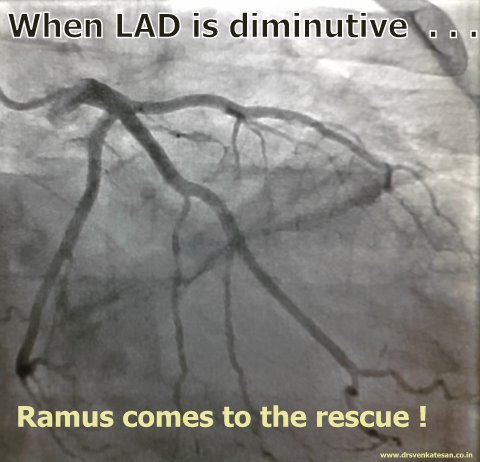
It is very rare to see a ramus  take a long course . Here  is a patient whose LAD is small  which  falls  short of LV apex . Sensing this , the ramus travels all the way to apex and support the LAD in distress !

RAO caudal view shows the Ramus reaching all the way to LV apex! Note the diminutive LAD and absence of true OMs from LCX.

* Technically  this can  also be  referred to as a rare form of dual LAD system .