Feeds:
Posts
Comments

Drug eluting stents are liberally used  worldover .

It is very unfortunate ,while the jury is still confused about the role of DES  “even”  in chronic coronary syndrome ,

There has been widespread use of DES in  the   potentially hazardous    thrombotic milieu  of STEMI  . It is well known  the DES ( polymer and drug)   has a dangerous liaison  with the thrombus.

Even as the evidence base was about to accumulate against the DES in STEMI , there was  an undue haste in the use of  this stent in STEMI .

Now in 2010 the results are out the DEDICATION trial

  • The culprit is out
  • The truth exposed
  • DES kills more life than bare metal stents   during primary PCI

Read this article  ,just released in Atlanta 2010

http://www.cardiosource.com/clinicaltrials/trial.asp?trialID=1618

Here is one of   the  very good resource   for  all those basic questions we often ask  in pediatric cardiac catheterisation. Mind you ,  great books do not come free of cost .

Have a preview . Thanks to Google books

Click on the book to enter  , if  you are lucky you will get the  information you need   free  . . .

Management of  atrial fibrillation has been a  big puzzle for cardiologists  for many  decades  till  it became a corporate game , and  now in the era of recession it has become  medicare’s  night mare !

So , we  were  made to dance to the tunes of the so called evidence based cardiology . . .

  • From only rhythm control to . . . in 1990s
  • Either rhythm or rate control  . . .       in early  late 1990s
  • Then cost control  was found  more important than rate control  . . .
  • . . . So rate control became superior to rhythm control in early 2000s

In 2010 , even the  rate control  became  a luxury ,  here comes the  real ace !   ” Casual rate control may be  suffice in most cases of AF “

Read this article  from  NEJM , which tries to  make  sense out of nonsense  and judge for yourself

Probably the most influential  article  in electrophysiology over  the  next decade

Click  below to reach Nejm article

http://content.nejm.org/cgi/content/full/NEJMoa1001337?query=TOC

http://content.nejm.org/cgi/content/full/NEJMe1002301?query=TOC

Gist of the trial

Technically and literally it  means a  “Take it easy attitude” as long as patient is comfortable , even a rate  of  more than 100 is allowed . Few years back the above concept could be termed a “non sense”

Final message

In this  perennial  management issue  of AF  ,  Whether ,   we were successful in  restoring   sinus rhythm or not , we have restored  the common sense*  Thanks to RACE 2 investigators.

* Do not unnecessarily trouble a  asymptomatic  patient with those powerful  and costly  antiarrhythmic drugs .

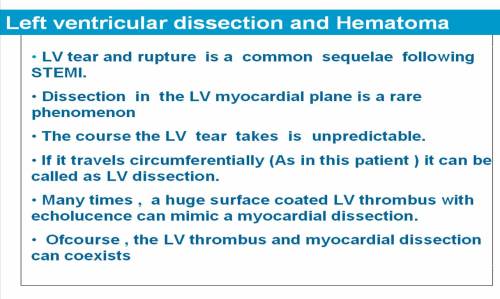
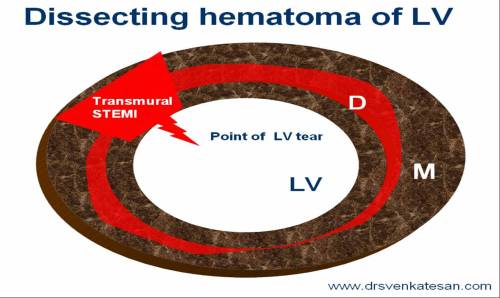
Left ventricular dissection is a rare complication of STEMI .A case report

Click on the slide to see the video  hosted in  youtube

Slide 1

Slide 2

Reference

http://www.ingentaconnect.com/content/bsc/echo/2009/00000026/00000003/art00006

http://resources.metapress.com/pdf-preview.axd?code=g4kqby7wnkjepetx&size=largest

The LV ejection fraction ,  is  the most revered medical parameter for both physicians and cardiologists.There are anesthetists and surgeons , who  do not  operate  a  cardiac patient  without knowing it.There are  physicians  who  do monthly assessment of EF in their patients  with dilated  cardiomyopathy.

Now ,every one is interested to know what is their EF ?  Thanks to the global  information highway .We witness ,   patients who are extremely delighted when their  EF increases from 45% to 48% . Similarly , they get depressed when it falls by 2% .

Why this hoopla around the LV EF ?

Every one knows EF is nothing but a LV contractile force at a particular  beat of the heart . It is possibly a crudest possible way to screen for   LV function.( Of course it can still be useful  in patients  with established myocardial disease to follow up  LV dysfunction)

The  most important caveat in  EF is it’s dependence on the loading conditions  of heart .It is   also  heavily influenced by the  heart rate.We now, even a severely dysfunctional LV can contract vigorously with inotropic stimulation  like dobutamine  or whenever local catecholamines.

Our obsession with EF is complete and it is not expected to get cured in the near future.

There are many hundreds of articles in cardiology literature  which  ridicules the EF as sole parameter for assessing LV function. Still ,  it is the number one parameter to asses LV function  in real world as well as in  vast number of land mark clinical  trials .  Are all those trial  results to be doomed ?

Even as  the  LV EF is   being labeled as  futile index  ,   we  also  realise we have not traveled  far from our great clinical   ancestors . Thousands of  years ago   the Chinese  yellow  emperor  of medicine  found  the cardiac contractility  by pulse volume  and predicted death accurately  ,  probably  better  than the live 3d echocardiography   derived EF   guided by LV volume rendering algorithm !

The purpose of this article is to tell the current generation physicians  there are some simple and probably  accurate  clinical tips  to rule out significant LV dysfunction.

One can confidentially tell  the LV  EF  would  be > 50%  in 99% of population if they have the following !

  • A brisk upstroke of carotid pulse.*
  • A well palpated tapping apical impulse**
  • A Loud  first heart sound(S1)
  • A  totally normal ECG (Even a normal QRS complex  is suffice !) ***
  • Normal CT ratio in Xray chest
  • A  comfortable brisk walk of  at 6 km/hour for 10 m .

* A brisk central arterial pulse is nothing but the reflection of LV DP/DT a sophisticated echo parameter assessed  with much hype ! A good thumb with an   alert brain can accurately tell a given patients dp/dt is within normal range.

** A loud S1 and tapping apical impulse indicate the velocity of closure of  anterior mitral leaflet.Which is in turn reflect the force of contraction of the antero lateral  papillary muscle of LV .So what you hear a loud s1 is nothing but the contractile function of the most important  part of LV namely the pap muscle of LV.

*** A normal ECG ,  generally tells us  all is  well with LV myocardium . Finally,  it makes  immense sense to correlate the functional capacity to EF. (90% correlation)

Final message

Mind you ,  all the above modalities come either  free of cost or a fraction of  echocardiography  . It is estimated up to 90% echocardiography scans to R/O LV dysfunction can be avoided . The global health care costs can be saved and be utilised for some better purpose like protecting our atmospheric shell  from the  hazardous   gases

Note of caution

While ,one can rule out signficant LV dysfunction by above mode  ,  it can miss  other forms of LV dysfunction like relaxation defect etc . (ofcourse the EF also misses it !) .Judicious use of functional  imaging modalities are adviced in those who require it.
The most famous and popular view in clinical echocardiography is para sternal long axis view.It gives us an instant information about the status of left atrium , left ventricle and aorta.Left atrium appears to be seen in full. Still , one should realise it is far from truth.There is a huge blind spot  for left atrium in this view .

For a complete imaging of LA one need to do a short axis view at aortic level, and of course a 4 chamber view . All these three views put together , can at best give a 80%  exploration of LA .The rest of the  20%(  some times vital !) can be seen only be transesophageal echo .

Why para sternal long axis fail to give even glimpse of the 4 pulmonary veins ?

  • Pulmonary veins are probably ,  the most vital structure  in LA . There are 4 veins , generally  arranged in 2 pairs
  • Unfortunately all these 4 veins does  not  interrupt the ultrasound beam in this view .The beam in para sternal view crosses  the anterior and lateral surfaces and to a  very small area of inter atiral septum(  IAS )
  • These enter  the posterior surface of the LA in an oblique angle . The angle of entry is widely variable .Some times they need to run a parallel course with LA posterior wall . This makes recognition and delineation  of PV from LA very difficult ..
  • Since all   4 pulmonary veins are located in the posterior aspect of LA ,  they  are best visualized either in apical 4 chamber (Right pulmonary veins) or short axis views(Left pulmonary veins)

When can pulmonary veins visible in PS- LAX view ?

When PVs take an abnormal course like in TAPVC or when they enter coronary sinus etc .

Rarely ,  huge LA enlargement may pull or push the PVs and make them visible in LAX view.

See the link

Hunting for  treasures in medical jungle is no easy job

There are  thousands  of websites for learning  radiology  and then ,

This one  . . .

Hats  off  to   William Herring, MD,

http://www.learningradiology.com/toc/tocorgansystems/toccardiac.htm

Even though it is a great vein , often the imaging pulmonary veins by echocardiography is a not a pleasant excercise.

This is due to the following facts

  • The pulmonary veins are posterior structures
  • They occupy the far field of echocardiographic window
  • The pulmonary veins often enter obliquely into the LA
  • The course of PVs are highly variable ( Like RCA origin !) especially in ASDs ,where identifying PVs becomes all the more important

Hence no fixed imaging angle can be advised . But generally a pattern is observed.

  • Right pulmonary veins are best viewed in apical 4 chamber or 5 chamber or in between (Especially RUPV is  seen best in 4.5 chamber view !)
  • Left pulmonary vein , best visualised in  Para sternal  long and short axis view.

Other modalities for imaging pulmonary veins

TEE : Can be  very useful since it is brings the vein closer to the probe .But needs more expertice.

Contrast echo :Probably a simple and best modality often underutilised.

Very useful to clinch the diagnosis when PVs take abnormal course as in PAPVC .

MDCT , Spiral CT, MRI  are the new age modalities that can provide us  with dramatic  3d images of PVs.

The  echocardiogram will always prevail over these sophisticated gadgets for its simplicity and also it’s ability to give us the physiology of pulmonary venous flow which is vital in many diseases(Constriction, Diastolic function etc)

The following illustration is a gross attempt to simplify the imaging of PVs.Please note the rules may not be applicable in all.

Left upper and lower pulmonary veins in short axis view will be posted shortly .

Reference

The images are  based on  personal observations and  an  excellent insight  on the topic from  Department of Cardiovascular Medicine, Guangdong Provincial People’s Hospital, Guangzhou , China

http://ejechocard.oxfordjournals.org/content/9/5/655.full

Are the drug eluting stents really better than bare metal stents ?
A million dolor question ? , No . . . a billion dolor question
A study which answered most convincingly with a huge data base  published in LANCET 2007.
  • 38 trials  , Metaanalysis
  • 18 023 patients with
  • 4 year follow-up of up to 4 years.
  • No mortality difference from bare metal stent vs DES
But unfortunately there is  no takers for this  study . The usage of DES continue to  surge ahead  .
The problem facing the medical science in the current era
It takes years  of research to get  into  the truth    and  still   longer time  for  us  to  accept it ! Ironically  falsehoods have immediate patronage and there is no incubation period !

Human body is a collection of trillions of cells.  Life  is nothing but , a bundle of energy flowing across each of these cells  .Every  organ  has a  specailised mode of communication among themselves and others. When a cell is in an excited state , there is a  likelihood of spontaneous electrical activity.This can happen in nerve cells, cardiac cells , GI tract,  or virtually in  any cell  which has a porous cell membrane and ionic fluxes across it .

  • Each cell membrane has a resting membrane potential . It  varies between -60 to – 90mv in most cells. When this potential increases there a propensity for  arrhythmias in heart  and convulsions in the brain , peristalsis in intestines and so on .
  • Drugs  like local anesthetic lignociane acts by blocking the  Na+ channels and there by neural activation .Similarly magesium  acts on these channels to reduce the excitability of these cells.
  • We know,  the sharp ascending stroke of cellular  action potential is mediated by Na + .Blockage of this channel blunts the action potential voltage and thus  the  early and late after depolarisation is prevented
  • Magnesium sulphate’s anticonvulsant action is directly  attributable  to this membrane stabilising action

Thus , membrane stabilising action  can be termed as “membrane sedating”  action