As I was mulling about the misplaced priorities in modern health delivery , today’s (25-01-2015) edition of “The Hindu” , India’s National newspaper carries an exact article by Dr B.M.Hegde .
No doubt ,his articles are constantly criticized by the scientific community for the simple reason, he is forcibly trying to add wisdom to science !
Chronic stable angina : Most can be effectively managed by optimal /intensive medicines and life style Interventions .About 10% will require PCI/CABG.
ACS – STEMI: Primarily managed with rapid and competent pre-hospital care with prompt thrombolysis in or out of hospital .Patients with large STEMI who develop complications (Again about 10 %) require PCI and few additional lives can be saved.
ACS-NSTEMI : This is the group that demand an important role for PCI . All true high risk UA/NSTEMI patients should receive urgent coronary angiogram and critical lesions should either be stented or sent for CABG (If the lesions are multiple and complex ) The field of interventional cardiology is expected to play a major role in this category of patients for the simple reason , we not only give dramatic relief from angina and also prevent a potentially a huge MI that is waiting to happen !
* It is vital to emphasise the “Aim and objective” in NSTEMI management is critically different from other two. We know , in CSA the aim is to give relief symptoms and improve excercise capacity . Both PCI/CABG are unlikely to prevent a future MI in CSA..In STEMI it has already occurred .The aim is to salvage myocardium and prevent future events. While PCI can do the former , it can’t do the later . In STEMI scenerio ,we have very good alternate modality called thrombolysis which can easily beat the pPCI in , cost , availability and time (and hence efficiency as well in most countries !)
Counter thought
The above suggestion is too simplified ,generalized , misleading , and unscientific, should strongly be disagreed. For those people who disagree , I provide an alternate scheme .It is ultra short ,comes in 5 lines .Very practical and scientific too !
In any patient , who is suspected to have either acute or chronic coronary syndromes ,take them to the cath lab in an urgent or semi urgent fashion .Do an angiogram and stent all lesions that you feel important . If stenting is not possible manage with optimal medicines and /or send them to the surgeons.
Final message
The essence of catheter based coronary care is simple.We complicate it. To understand this concept 100’s of cardiology journals and as many conferences and infinite number of books are churned out every year !
Following are revered facts . . . among the “Guardians of Cardiology” !
When false truths are synthesized to conceal a true myth . . . where will the poor myth complain ?Following are revered facts . . . among the “Guardians of Cardiology” !
Primary PCI is a greatest innovation in modern day cardiology .Without this modality most STEMI patients will buy Instant tickets to grave yard !
A cardiologist who intends to thrombolyse a STEMI is considered as a low quality cardiologist .
Streptokinase should have no place in the crash carts of modern coronary care units.
There is nothing called “Time window” for rescue angioplasty.
VVI pacemaker will convert an electrical problem of heart block into a mechanical one by depressing LV function .
Digoxin is an obsolete drug even in well established cardiac failure with dilated heart.
Beta blockers not only fail to control blood pressure smoothly , it often converts a hypertensive individual into a unhealthy one by it’s prohibitive side effects !
CAD is growing as an epidemic in most parts of the globe. It is a major determinant of health status of any country .Great strides in diagnostic, treatment modalities of CAD have been made in the last few decades. Still , the core principle of management of CAD resides in simple things like risk factor reduction / optimization , life style changes and few essential cardio-protective medications Aspirin, beta blockers and statins.
However , modern scientists have made a firm statement that knowing the coronary anatomy before starting the treatment is the only scientific approach . It is a huge assumption !
Is it practical ? or is it really required ?
CAD can be managed by means of medicines , interventions or surgery. Revascularisation is required only for those , who have critical , symptomatic lesions.
It is estimated , in only a fraction of CAD patients , we would require to know the anatomy . We have set criteria to choose patients for CAG , who are likely to have critical lesions.Physicians are trained for that elusive wisdom to choose such patients .Standard text books do mention clear-cut Indications for doing CAGs. Unfortunately , it is least respected and followed .
Cardiac physicians who would boast they can’t treat a CAD without knowing the coronary anatomy are clinically handicapped or poorly trained.
I am afraid such a class of cardiologists are rapidly breeding in the country side. They are encouraged to attend CME on clinical cardiology and basic principles of clinical decision-making .
We can’t keep on doing CAGs like ECG for every episode of angina . In fact treating CAD without knowing the anatomy remains (And it should be ) the dominant theme contemporary clinical practice . CAG is multi -edged sword
The most important side effect of routine coronary angiogram is , it ends up in infinite number of inappropriate interventions !
I think , we should pray in Hippocratic temples for sufficient wisdom to choose our patients. We can also learn it from Neurologists , they somehow manage most forms of cerebrovascular diseases (scientifically too ! ) without asking for angiogram of circle of Willis ! Mind you. . . brain is equally a vital organ !
Final message
It needn’t be a crime to treat CAD* without knowing the coronary anatomy. Rather . . . it would be so , to ask for CAG indiscriminately , in every episode of chest pain , without applying clinical sense !
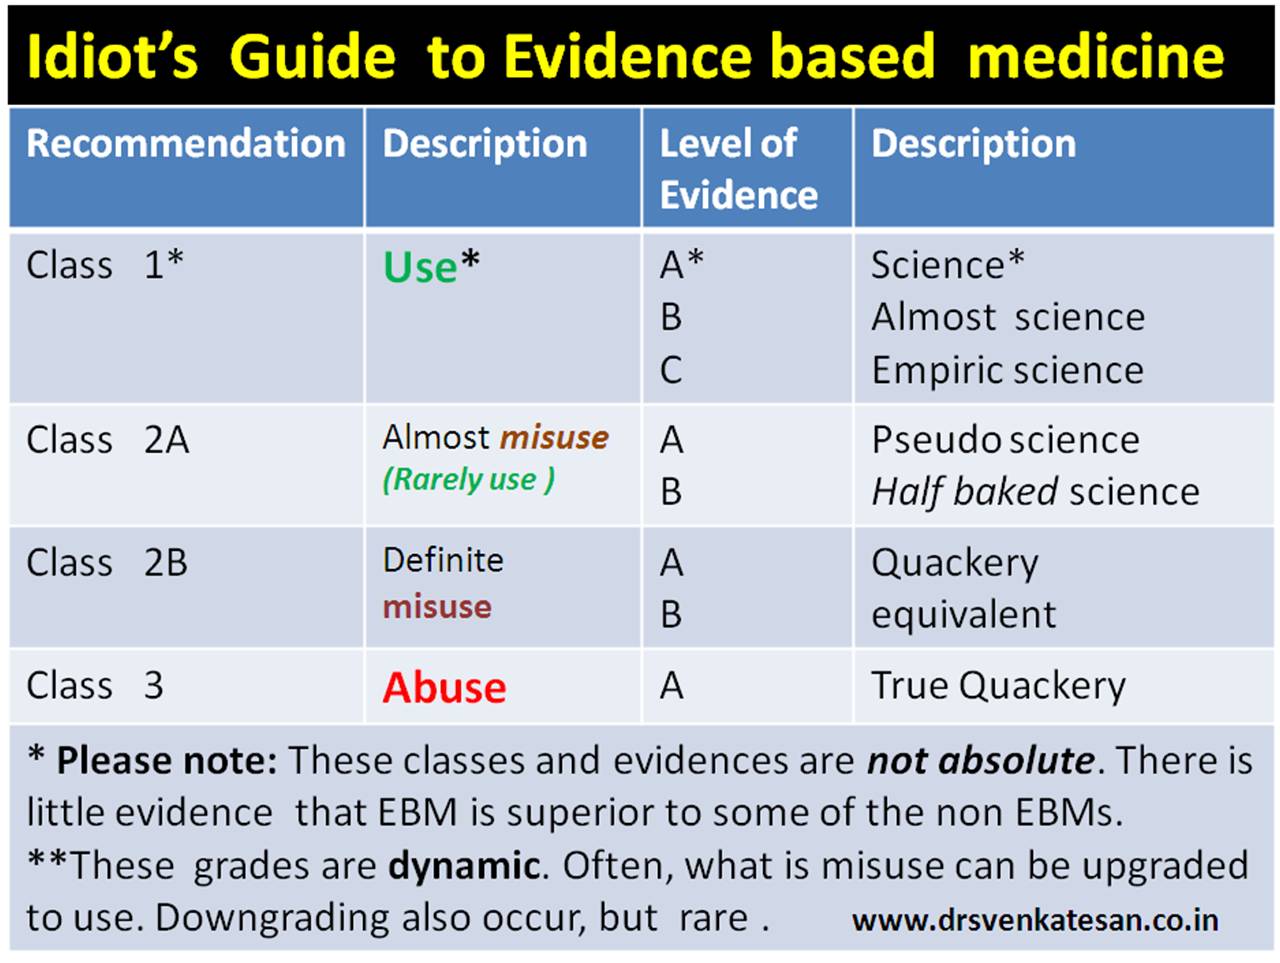
The current fad called EBM has lots of lacunae. Though evidence based approach is considered the ultimate journey towards truth ,lot of non academic factors contaminate it .In it’s current form , it is difficult to comprehend it.
This is an attempt to decode the mystery of EBM expressed in a simplified lay person’s term .They are the ones from whom we learn medicine. They are our teachers in the true sense.
By the way ,it is also my approach to EBM .Sorry , if this post sounds arrogant ! It is not the intention .Truths often times appear brutal .
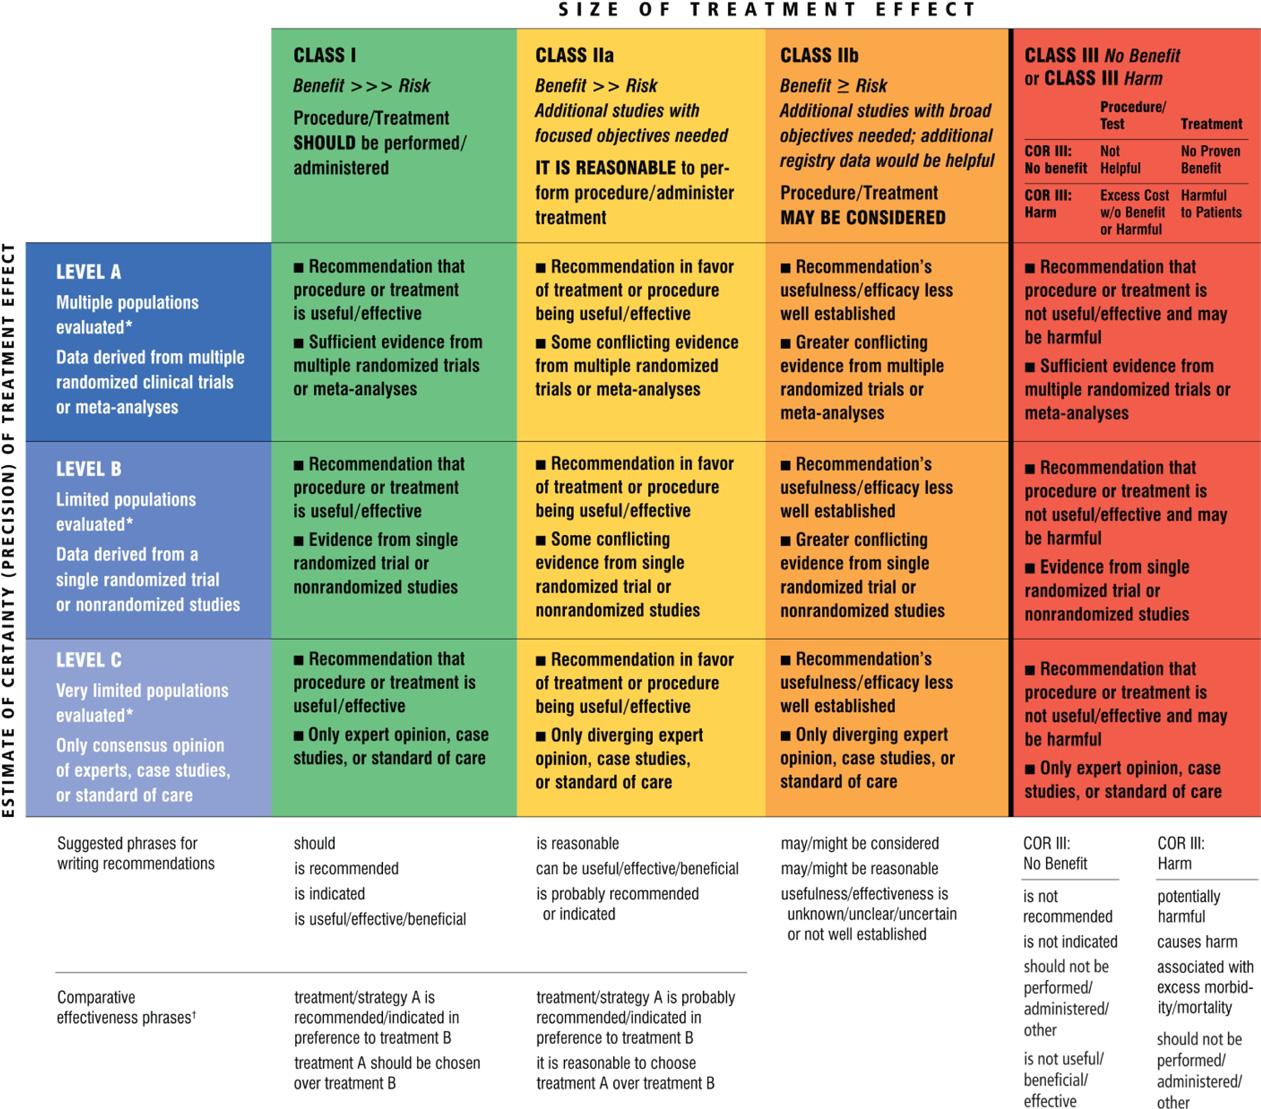
And . . . the Genius approach to EBM for comparison
What is the most important factor that will decide the revascularsation following a STEMI ?
Patient’s symptoms
Residual Ischemia documented by stress test /Perfusion scan
Presence of significant LV dysfunction
Coronary anatomy and lesion profile
Wealth of the patient (Insurance limit and other financial resources )
Response 2 is academically correct , but practically and politically response 5 would be the right one for most cardiologists .At any given day , affordability and availability of PCI will prevail over all other factors .
Affluence based cardiology
Image courtesey : Jupeter images
What is the height of inappropriateness in modern cardiac care ?
This world will never forgive the medical profession , if they do not fight against grossly inappropriate medical care system especially in the life saving situations .While one cardiologist just watches a left main disease patient with unstable angina die peacefully in a Govt institution , while another patient with asymptomatic distal PDA lesion gets a 3rd generation drug eluting stent in a nearby corporate hospital !
Please note : Harm is the ultimate outcome in both rich and poor.One suffers with non availability while the other is the victim of affordability .
Is a deceit camouflaged with a pseudo scientific fabric.
Can be encouraged in very selective patient population and diseases by experienced cardiologists , as it may be really useful when no other options are available.
Is diagonally opposite to evidence based medicine , should be banned in toto !
Answer:
4 is the correct answer .occasionally 3 can be true
Some of the examples of off label indication
Statins for Aortic stenosis
VSD device for RSOV closure
Ivabradine for cardiac failure
By the way how does an off label become on label?
It is not the ” God ” who gives the label to them
There are few “Demi Gods” sitting aside in the regulatory corridors of New york and Geneva who decide the fate of these drugs and devices . Ultimately the integrity of these organizations that will either protect or injure our patients !
Final message
Medical science grows my mistakes . . . hence we should be encouraged to do more of that . . . so that we can grow !
This happened in one of the cardiology work shops I recently attended , which beamed live cath lab procedures from across the country.
An interventional cardiology team in a bright sky blue suit was preparing a patient for graft angioplasty in a degenerated SVG graft to left circumflex . The patient had apparently had CABG few years ago (LIMA to LAD still functional ) . His LV EF was reported to be 40 %. The procedure was about to begin. The femoral artery was being cannulated . . .
As the audience were encouraged to ask questions. A young cardiologist wanted to know what was the indication to open up the graft / And what was his symptom ?
“Do not ask such silly question” . Prompt came the reply from one of a senior interventional cardiologist from within the cath lab. He further said such questions can not be entertained as the forum is meant for tips and tricks to cross a degenerated vessel graft . When he insisted for an answer , the entire panel joined the ridicule and the questioner quietly went out of the hall !
What do you infer from such reaction?
What makes this question silly ? Why the cardiologist got annoyed and amused ?
This odd reaction implies , the cardiologist has something to hide or has guilt of doing inappropriate procedure.
Such is the transparency in cardiology workshops transmitted live all over the country imagine what one can expect in regular cath labs .
Live workshops are not simply to train our hands . It is supposed to teach us the “what is right” and “what is wrong” , “what is good” and “what is bad” for our ailing patients. The senior cardiologists who administer these workshops should realise this fact. Very often a bad example is set . When asking for patient’s true symptoms looks silly for us . . . guess where our profession is heading for !
What is the “secret of success” among current generation cardiologists ?
A . Strong foundations in cardiology with excellent clinical skills and a rational approach to the given problem.
B. The secret lies in the nimble fingers which acts almost , like an extension of catheters in cath lab !
C. The speed with which he can mobilise a cath lab team in an ” off – office hour” primary PCI !
D. It is the the cunning art of converting coronary angiograms into angioplasties , by lucid discussions with patients and their relatives in the the silent cath lab corridors !
Answer:
When this question was posed to a group of cardiologists , D was considered most important B,and C came close behind and A was probably least important and few thought “A” character is rather an impediment to become a successful cardiologist !
*Unfortunately a successful cardiologist is defined in India by number of angioplasties he does per month, What a disgrace to a great medical specialty called cardiology !
What is normal CAG to angioplasty conversion ratio ?
This term is quiet often used in the main stream cardiology journals , in work places , conferences , hospitals and even among lay persons . No body bothers to define this terminology. What exactly this term means ?
It may not mean anything . . . to most of us even as the percentage of inappropriate angioplasty is steadily increasing over the years .
Picture courtesey : Jupeter Images
What does the term Inappropriate angioplasty mean ?
(Choose the correct answer . . . one or more may be true )
A.It simply means doing unnecessary angioplasties and has no major implication to any one.
B.A form of medical ignorance or an unethical act and should be strongly condemned.
C. An acceptable cardiology practice , need not be discouraged , as it improves the quality of life of physicians !
D. A sure act of “error by commission” that amounts to medical negligence .
E.It is a decent term for a major guideline violation
E. It can be termed as medical malpractice as it amounts to harming the patient with or without intention.
The contents of the this blog is being published as Kindle E book , as per the request of many of the readers. Every article will continue to be open source in this site. Again I shall reiterate the book format is not aimed at any commercial intent. It is only to facilitate learning in a single book format Here is the link to book https://amzn.in/d/euhL5vu
Click below to see who is watching this website live !
This site will never aim for profit. Still ,this donation link is added at the request of few visitors who wanted to contribute and of-course that will help make it sustainable .
Please Note
The author acknowledges all the queries posted by the readers and wishes to answer them .Due to logistic reasons only few could be responded. Inconvenience caused is regretted.