Feeds:
Posts
Comments

Posts Tagged ‘stemi’

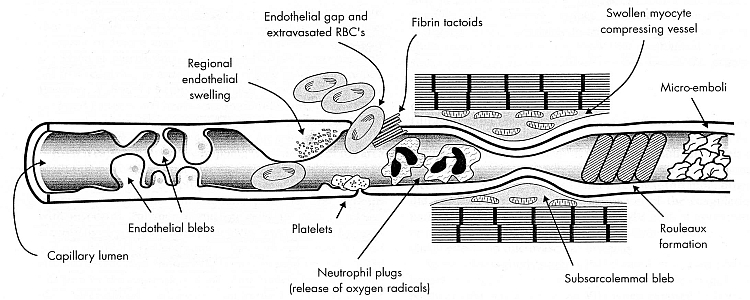
No reflow is the terminology used primarily in cath labs where, even  after a successful opening and stenting  of a coronary artery the coronary blood flow is not  restored to myocardium . The point to be emphazised here is blood do cross  successfully the site of  the obstruction but fails to enter the muscle segment  to which the coronary artery is supplying. So the paradoxical situation of artery  being open but the  myocardium is closed to receive  blood flow  happens . This is termed as no -reflow.  Actually it is a  misnomer , and  ideally it should be called “no flow” because  normal distal flow  does not  occur (After PCI)  in the first instance  to get interrupted  later on  and be labeled as  no re-flow.  .The only positive effect of PCI in these situation is blood flow would have improved by few centimeters ie till it reaches  but falls short of myocardium . In fact no reflow , can be termed as  glorified and concealed  terminology  for  PCI failure . It needs urgent action . No reflow is also called as myocardial epicardial dissociation.

Mechanism of no reflow.
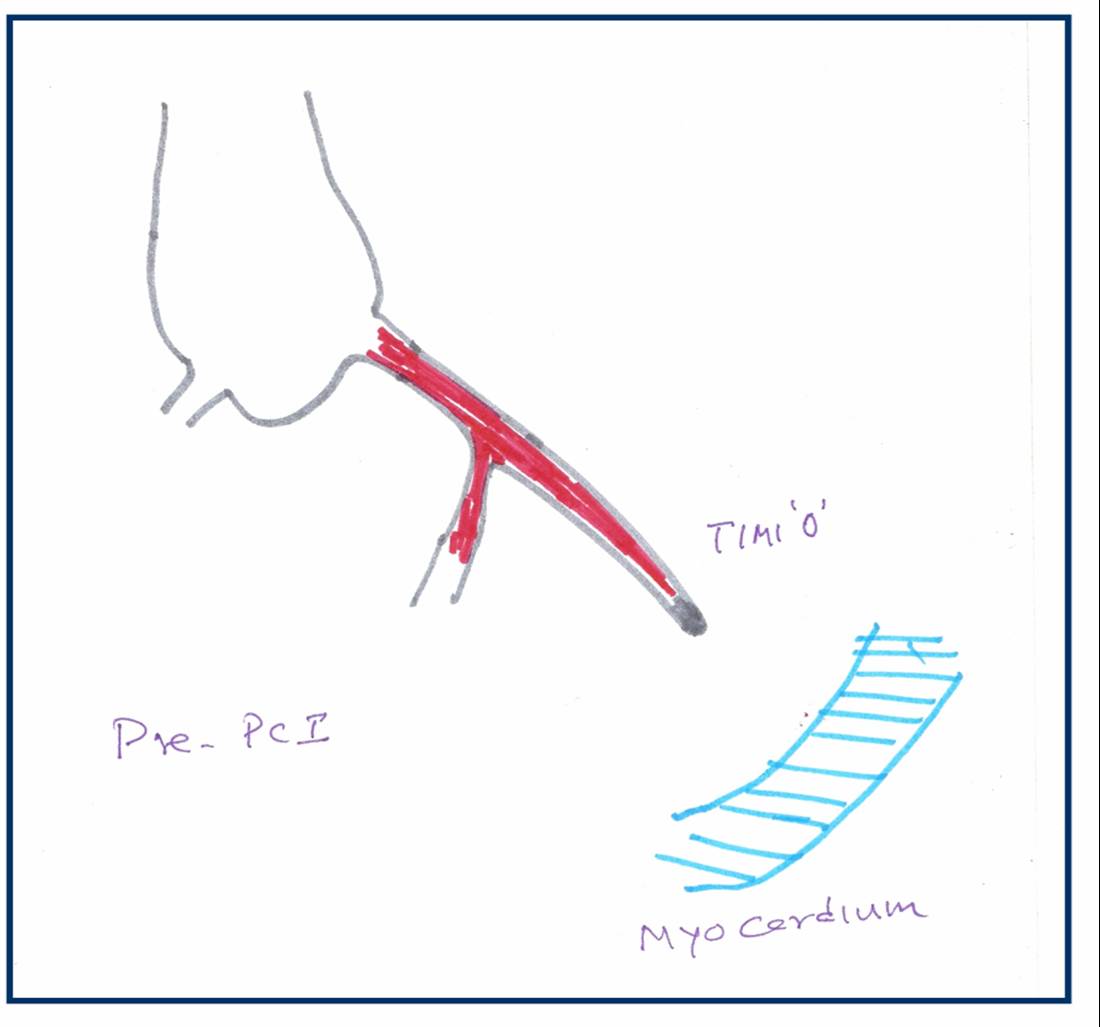
Curious case of open coronary artery and closed myocardium !
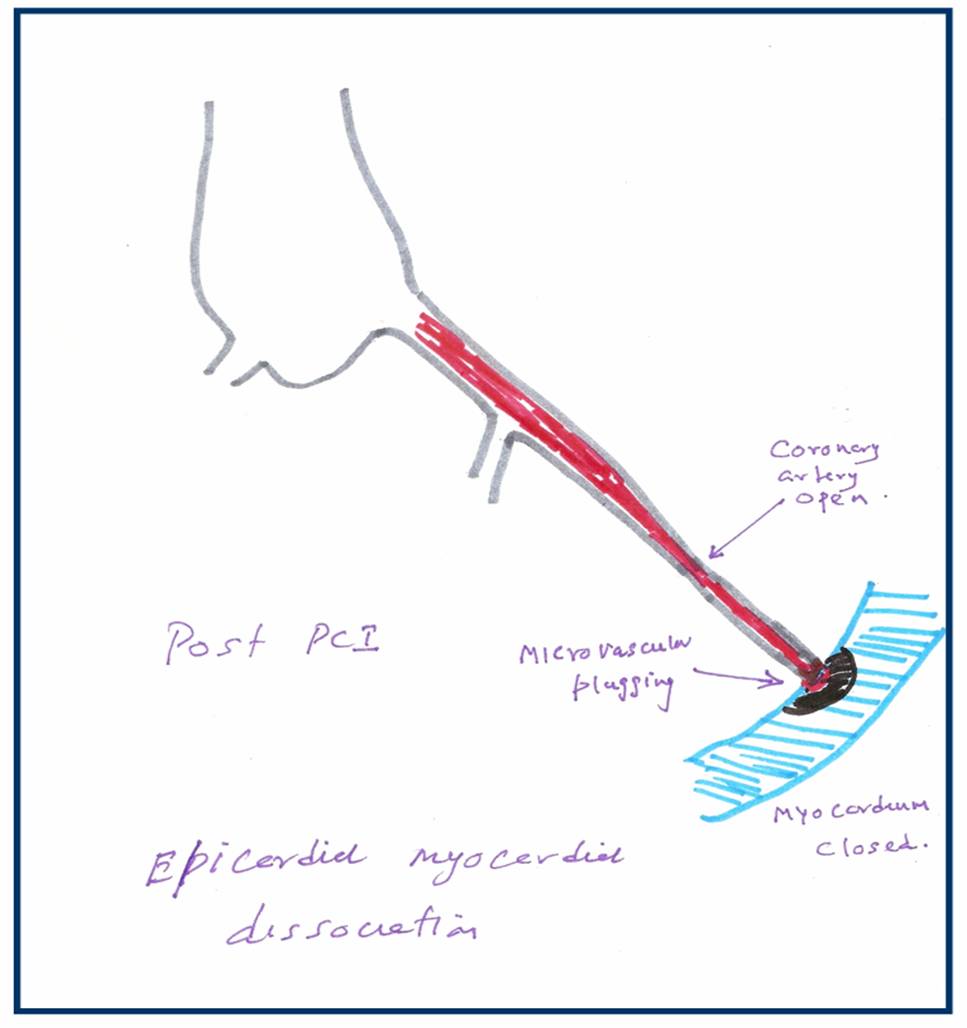
Coronary  microvascular plugging  is mainly  due to thrombus and atheromatous debri , myocardial  edema , microvascular spasm may also contribute.

Where can it occur ?

  • First described in cath lab, especially following primary angioplasty.
  • It can very  well happen following thrombolysis in STEMI.
  • Can occur in venous grafts.

How do you recognise no reflow?

In cath lab it will be self evident from the check angiogram. Some times it is less obvious and may  require, myocardial  blush score, TIMI frame  count, contrast echocardiography, PET scan etc. In post MI a very simple method to recognise this entity could be the observation of persistent ST elevation in ECG .

Treatment.

Extremely difficult. Almost every coronary vasodilator has been tried.(Nitrates, nicorandil, calcium blockers, etc).Success is less than 30%.  High pressure flushing with saline inside the coronary artery is advocated by some.Others believe it’s dangerous to do it. So prevention is the key. Avoid doing PCI in complex, thrombotic lesions. Use thrombus suction device like export catheter(Medtronic). Distal protective devices are double edged devices , useful only in experienced hands.

Unanswered question

What is the size of the particle (thrombotic and atheromatous  debri)  the   coronary microcirculation safely handle and push it into the coronary venous circulation and the coronary sinus for disposal ?

If we can lyse the thrombus into micro particles by some mechanism and make it traverse the coronary circulation this complication of microvascular  plugging can be treated and prevented .

What is the final message ?

  • No reflow is relatively common condition during emergency PCI done for ACS patients
  • More common in complex thrombotic lesions.
  • Can also  occur in STEMI
  • Treatment is often vexing . In fact the treatment of this condition is so difficult , it can be termed  almost synonymously with “Failed PCI” if flow is not restored.
  • Successful treatment of no- reflow  means not momentry restoration of  myocardial flow  by mechanical and pharmacological modalities ,but to maintain sustained myocardial   perfusion. This we realise, as patients who have had a no reflow during  a PCI, do not perform as well in the follow up  .
  • So prevention is the key.

Read Full Post »

Differential response of thrombolysis between left and right coronary system

  • Thrombolysis is the specific treatment for acute myocardial infarction. ( Privileged few , get primary PCI))
  • Failed thrombolysis occurs in significant number of patients ( 30-40%).
  • Persistent ST elevation  120 minutes after thrombolysis is best indicator of failed thrombolysis.
  • It has been a consistent observation  failed  thromolysis  is more frequent in anterior   or LAD myocardial infarction.

In a simple study we have documented  patients  with inferior MI  rarely had persistent ST elevation and thrombolysis  was   successful in vast majority  of  patients  ( Except in few patients associated lateral MI)


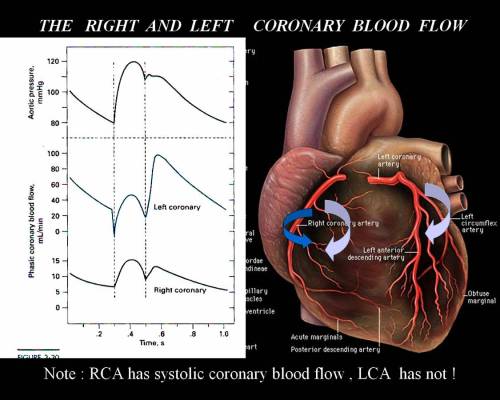
The mechanism of better thrombolysis in right coronary artery  is simple.The success of thrombolysis , apart from early time window , is directly correlated with pressure head  and the duration of contact between the thrombolytic agent and the thrombus. In right coronary circulation the  blood flow is continuous ,  occurs  both in systole and diastole that facilitates the maximum delivery of the thrombolytic agent . Further there is a favorable  pressure gradient  across RV myocardium  as the transmural occluding pressure across RV is considerably less then LV myocardium.

This paper was presented in the  “Annual cardiological society of India scientific sessions”

at Chennai, Tamil Nadu.India December 2000

Click to down load PPT full presentation

Read Full Post »

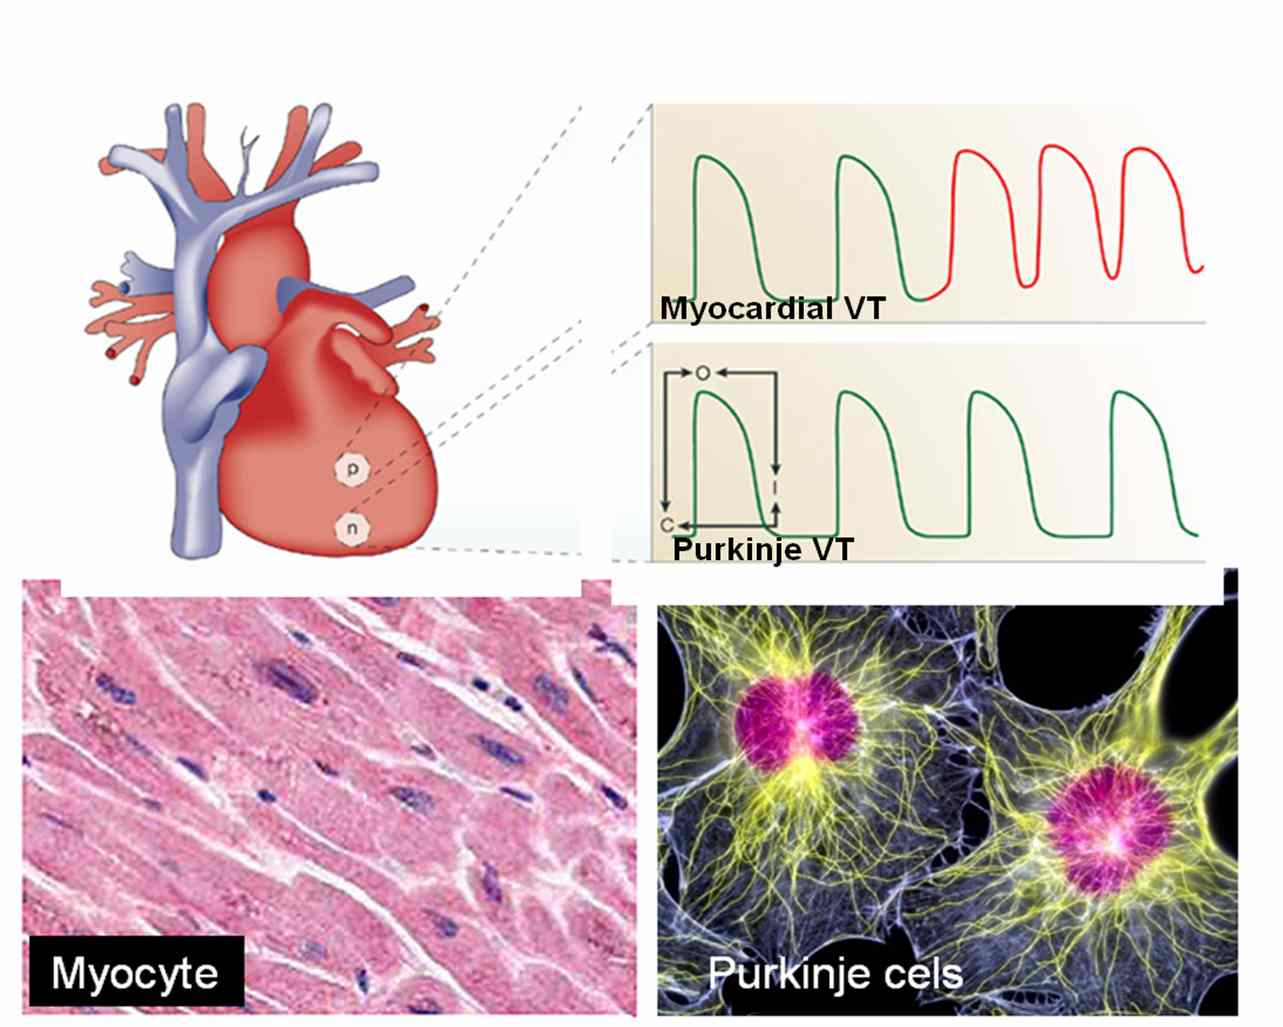
The cell of origin of ventricular tachycardia is rarely discussed at bedside. It is still in research labs !

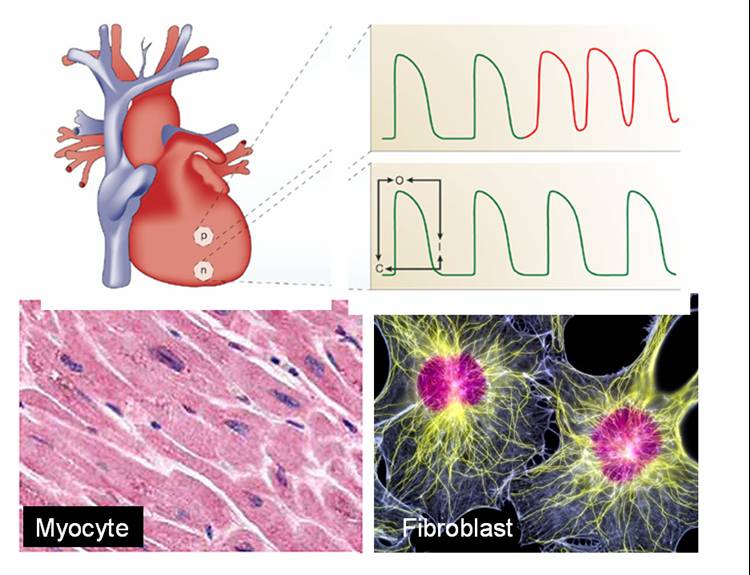
                                    Ventricles are not made up off entirely myocytes. Apart from myocytes it contains specialised  purkinje cells , fibrocytes, interstitial cells and  some times primitive mesenchymal cells. Ventricular tachycardia can arise either in purkinje cells, the myocytes  or even the fibrocytes. The myocyte  VT  classically occur during ACS or post infarct VTs.They are  more often hemodynamically unstable and quickly degenerate into ventricular fibrillation. Myocardial VT is likely to be pulseless and require DC cardiversion frequently. Purkinje VTs are relatively less unstable. If VT arise proximally in the septum near the distal his, or in bundle branches (BBR) the VT is more stable.They  are likely to respond to be medical management.

What is the therapeutic implication of knowing  myocardial VT ?

                               In fact  ,simply knowing the cell of origin of VT is not suffice .The ionic currents inside the cell that trigger and sustain the VT is more important. There are few ionic circuits responsible for VT. Sodium , Intra cellular calcium, potassium , beta receptor mediated calcium current.If we know the individual ionic culpirit we can block that specifically  . Now we have multi purpose ion blockers  like amiodarone which acts like a broad spectrum antibiotic and terminates a VT.

                              So as of now there is no real purpose of breaking our head  in locating the cell  of origin  and the ions responsible for VT  at  the bed side ,( Researchers will do that for us !).  We have only few  antiarrhythmic drugs available in our crash cart  .Our job is to choose the optimal  drug  which will fit in for our patient. In electro physiology labs, radio frequency ablation is done .This is  nothing but shooting down the abnormal electrical  focus (Cluster of cells or a samll segment of myocardium).  In future,  a single abnormal  cell could be selectively neutralised with cell based therapy assisted by  nanopore robots !

Read Full Post »

                                  Indication for thrombolysis in ST elevation MI  is mainly determined by clinical and ECG features. ST elevation of more than 1mm in two consecutive leads with a clinical suspicion of acute coronary event demands immediate thrombolysis.

                                 Early repolarisation syndrome(ERS) is a  is typical mimicker of STEMI . In ERS , ST segment elevation occurs in many leads especially precardial .This entity is estimated to occur in nearly 3-5% of population where a genetic variation in the potassium channel activation is reported.

                              If they  land in ER with some sort of chest pain , chances are high for labelling  them as ACS . It is not uncommon for  CCU physicians  to  witness  an  ERS being lysed . Even in many of the land mark trials (ISIS ) there has been many inappropriate thrombolysis , recognised later on.

What can really happen if you thromolyse them inadvertently ?

Generally nothing happens . But they are exposed to the risk of thromolysis. The ECG changes persist. And troponin will be negative and  echocardiogram will not reveal any wall motion defect.

Are we legally liable if a patient  with ERS was thrombolysed and he ends up with a bleeding complication like stroke ?

                        While the physician may feel guilty , there is no reasons for him to feel so.The guidelines are kept little lineant  for  the indication for thromolysis. When we are promoting  a strategy of early  thrombolyis  on a population based approach  in STEMI ,  there is bound to have a overlap with normality .The benefits out of early thrombolysis for eligible  patients for outweigh the few inappropriate thromolysis.

When you want to catch  a   real criminal  it is unavoidable,  one gets hold of all suspected criminals before letting them free . Unfortunately  in this exercise , some of the innocent  might experience   intimidation or even a injury  at the hands of law enforcers.

                               Similarly if a patient with ERS develop a severe esophageal spasm and typical  angina like chest pain he is absolutely certain to receive thrombolysis. (Troponin, CPK come later , and the results never veto the clinical and ECG criteria ,except probably in LBBB) .Many times critical  time dependent decisions are prone for errors in CCU.   So it may be  unscientific to ask why an ERS was  thrombolysed !

 How can one prevent inadvertent thrombolysis in ERS ?

                            Always ask for the previously recorded ECGs .If it is available and  look exactly similar to the current ECG  chances are unlikely  for ACS. In ERS ST segment is generally concavity upwards . ACC/AHA  guideline for STEMI  ,is  aware of this fact , but still  advices thrombolysis for all ST elevation irrespective of the morphology of ST segment elevation. This is propably intentional,   not  to incorporate morphology cirteria of ST elevation  for thromolysis .It would potentially  make many true STEMIs  diagnosed falsely  as ERS and deny thrombolysis.


What is the latest news about ERS ?

                       Now data are coming up, ERS is not entirely benign condition.Some of them ( Even a fraction of ERS population could be a significant number) can have a overlap between Brugada syndrome and they  could be prone for dangerous ventricular arrhythmia when challanged with ischemic or other stress.

Read Full Post »

This is a 15-year-old post about LVH, written in 2008. Few of my colleagues, now agree with this, still hesitate to oblige in the open, suggesting it is too good to be true! Re-posting it for your own assessment. Surprised, why cardiology community didn’t consider this observation worthy to pursue.

Advantages of Left ventricular hypertrophy (LVH)

Left ventricular hypertrophy is one of the most common clinical cardiac entity.It is recognised either by ECG or echocardiography.LVH has a unique place in cardiology as it can imply a  grossly pathological state or  a marker of healthy heart as in physiological hypertrophy in athletes.

Logic would suggest, in this era of  stem cells and  nano medicine ,  every muscle fibre in ventricle is worth in gold !. So when the nature provides an  extra reserve of myocardium in the form of LVH one should welcome it , if otherwise not harmful.

Is LVH due to systemic hypertension benign ?

Not really, LVH has been shown to be an independent cardiac risk factor. (The famous Framingham study)Further LVH can result in diastolic dysfunction and the risk of cardiac failure increases.

But in spite of these observations, an  astute clinician with considerable experience will appreciate , patients with LVH fare better during an acute coronary syndrome !

This has been a consistent clinical observation . (Shall we call it as class C . ACC /AHA evidence ? )

Is LVH  an asset during ACS ?

  • A hypertrophied heart takes ischemic injury very easy , it doesn’t really hurt much . Another possibility is that in  LVH myocytes are relatively resistant to hypoxia .
  • Patients with LVH rarely show  significant wall motion defect following an STEMI.This is probably because the full thickness transmural necrosis is almost never possible even if extensive MI occurs.
  • This is also reflected in ECG  as these patients   rarely develop q waves in  following STEMI .
  • Persistent ST elevation and failed thrombolysis is very uncommon in pateints with LVH.
  • LVH provides  a relative immunity against development of cardiogenic shock . It requires 40% of LV mass destruction to produce cardiogenic shock.This can rarely happen in LVH. In a  long term analysis we have found none of the patient with LVH developed cardiogenic shock following STEMI.
  • LVH patients  are also protected against development of free wall rupture.

 Concluding message

                   “Lack of published evidence is the weakest evidence to dismiss a true myth”

LVH , either pathological or physiological, has a hitherto unreported beneficial effect.It acts as a myocardial reserve and helps limit the impact of STEMI.


Read Full Post »

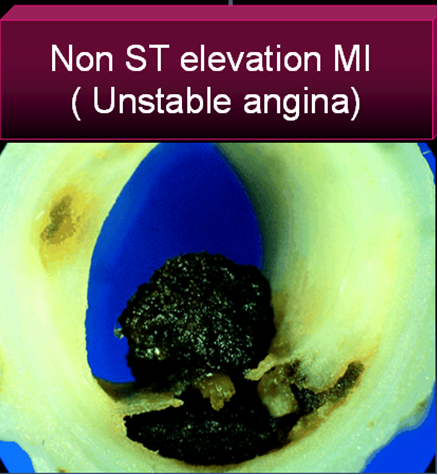
              Intra coronary thrombosis is the sine qua non of acute coronary syndrome ( Both STEMI and NSTEMI.) But thrombolysis is the specific therapy in STEMI and is contraindicated in NSTEMI/UA.

Why is this apparent paradox ? What is basic differnce between UA and AMI ?

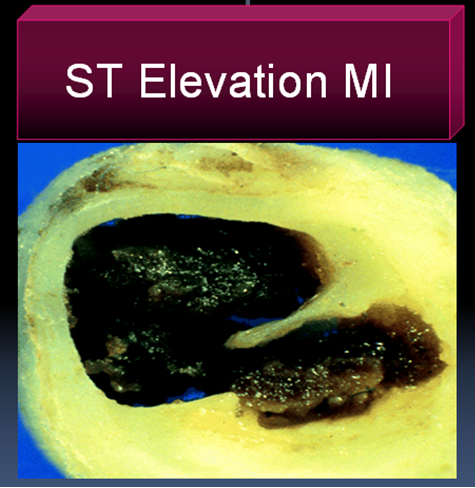
In STEMI there is a sudden & total occlusion of a coronary artery usually by a thrombus with or without a plaque .The immediate aim is to open up the blood vessel . Every minute is important as myocardium undergoes  a continuous process ischemic necrosis. So thrombolysis (or more specifically fibrinolysis should be attempted immediately) .The other option is primary angioplasty,  which will not be discussed here.

The thrombus in STEMI  is RBC &  fibrin rich and often called a red clot. Number of fibrinolytic agents like streptokinase, Tissue palsminogen activator,(TPA) Reteplace, Tenekteplace etc have been tested and  form the cornerstone of STEMI management.The untoward effect of stroke  during  thrombolysis  is well recognised , but usully the risk benefit ratio favors thrombolyis in most situations except in very elderly and previous history of stroke or bleeding disorder.

Unstable angina is a  close companion of STEMI . Many times it precedes STEMI often called preinfarction angina. During this phase blood flow in the coronary artery  becomes sluggish gradually,and patients develop  angina at rest .But unlike STEMI there is never a total occlusion and myocardium  is viable but ischemic,  and emergency salvaging of myocardium is not a therapeutic aim but prevention of MI becomes an aim. It is a paradox of sorts ,  even though thrombus is present in  UA ,  It has been learnt by experience thrombolytic agents are not useful in preventing an MI .


Why  thrombolysis is not useful in UA ?

1.In unstable angina  mechanical obstruction in the form of plaque fissure/rupture is more common than completely occluding thrombus. So lysis becomes less important.

2. Even if the thrombus is present , it is often intra plaque  or intra lesional and the  luminal  projection of thrombus is reduced  and hence thromolytic agents have limited area to act.

3.Further in UA/NSTEMI since it is a slow and gradual occlusion (Unlike sudden & total occlusion in STEMI) the platelets  get marginalised and trapped within the plaque .Hence in UA  thrombus is predominantly  white  . Often, a central platelet core  is  seen over which fibrin clot may also be  formed.

4.All available  thrombolytic agents act basically as a fibrinolytic agents,  and   so it finds   difficult to lyse the platelet rich clot.There is also a small risk of these agents lysing the fibrin cap and exposing underlying platelet  core and trigger a fresh thrombus.This has been documented in many trials( TIMI 3b to be specific) So if we thrombolyse in UA , there could be a risk of recurrent ACS episodes in the post thrombolytic phase.

5. UA is a semi emergency where  there is no race against time to salvage myocardium .Administering a  stroke prone thrombolytic agent tilts the risk benefit ratio against it.

6. Among UA, there is a significant group of secondary /perioperative UA   due to increased demand situations. Here there is absolutely no role for any thromolytic agents,  the  simple reason is , there is  no thrombus to get lysed. 

7.Many of the UA patient have multivessel CAD and might require surgical revascualarisation directly .


So fibrinolytic  agents are contraindicated in UA so what is the next step ?

The emergence of  intensive and aggressive platelet-lytic agents.

A combination of aspirin, clopidogrel, heparin, glycoprotien 2b 3a antagonist formed the major therapeutic protocol in these patients.Even though these are called antiplalet agents some of them  like 2b/3a antagonist eptifibatide, tirofiban, and many times even heparin has a potential to dissolve a thrombus. So technically one can call these agents  as thrombolytic agents.

What are the unresolved issues

                                       Even though clinical trials have convincingly shown thrombolytic agents  have no use in UA .There is a nagging belief  THAT  there could  be group of patients  with UA , still might benefit from thrombolysis as total occlusions have been documented  in some cases with UA.This is  especially true in peri-infarction unstable angina (Pre & post) as there is a fluctuation  between total and subtotal occlusions ) .But bed side recognition of this population is very difficult.

Many would consider this issue as redundant now,  since  most of  these patients  are taken up for emergency revascularisations

Read Full Post »

Interventional cardiology as a speciality is in cross roads.

The number of coronary interventions (PCI) has increased exponentially world over. With increasing  Cath labs and growing  expertise ,  access to PCI has enormously increased  even in underdeveloped countries.  Meanwhile ,  public lack  specific technical information about the appropriateness  of these costly procedures. It is our duty to do self audit on this issue.  .

                           In this context,  the evaluation  following a PCI  should look beyond  lumen oriented  endpoints.  Many  land mark trials on DES report 3 months are 6 months angiographic outcome and better luminal appearance . Many   tend to worry  more about the status of the stent rather than the patient !  This is primarily because the device companies have repeatedly stressed the technical end points rather than clinical end points .

It is a  well recognised fact  that ,stented coronary artery never guarantees against future  coronary events (ACS) either within the stent or away from it .It is an explict fact that , a patient  after getting a coronary stent , especially a drug eluting stent carries a life long risk of acute stent obstruction and possibly SCD .This information is rarely passed on to the patient in  and hence they are not able to take “learned consent”

It is true ,  one gets  a gratifying feeling  when  opening up a obstructed artery , but we also need  to answer this simple question   What is it’s impact on  patient’s  life  ?

COURAGE & OAT trials have put a break on the  prevailing precondtioned behaviour in the labs, namely any obstruction must be relieved if  technically feasible .

One should recall  the Gruentzig’s legacy  . Whaterver,  we do inside  a  patient’s coronary artery must have some useful purpose . We should not use patient’s  coronary artery to show our expertise and skills !

Dr.S.Venkatesan, Madras Medical College, Chennai, India

Read Full Post »

Recurrent myocardial infarction following an ACS is a fairly common clinical problem. Many times this is not recognised because it is difficult to establish the diagnosis.

The issues relevant here is

When does the first infarct (Index infact) process end ? and when the second infarct process start ?

Can the first infarct be a STEMI and the reinfarct be NSTEMI ? ( Dual acute coronary syndrome )

The only way to confirm a diagnosis of reinfarction is to document raising titres of cardiac enzymes and second peaking of CPK MB . New fresh ST elevation after a succesful thrombolysis is also a useful sign. But ST elevation in a q lead simply reflects a wall motion defect . So it requires enzymes to confirm it.

When there is tachycardia the ST segments tend to elevate following MI.

Other confounders are Infarct expansion and infarct extension .

These are macropathological entities almost impossible to dignose with surface ECG. What we diagnose as re-infarction could be an infact a infarct expansion.The modern terminology for infarct expansion is ventricle remodeling .The extreme remodeling results in ventricular aneurysm .Adverse acute ventricular remodeling can closely mimic a reinfarction .

What is clinical relevance of diagnosing reinfarction ?

Nothing great !

In modern day cardiology it is not a bother whether the infarct is expanding, extending or reinfarcting !All one has to do in a patient with chest pain ,showing a fresh ST elevation following STEMI is to take him/her to cath lab .

The only issue here one has to remember there are mechanical cause also for ST elevation following STEMI .

Dr.S.Venkatesan,Madras medical college, Chennai.

Read Full Post »

Is reciprocal ST  segment changes  occur  only in STEMI ? Can it occur in UA/NSTEMI ?   


                      Even   after   100 years of electro cardiology   the electrophysiological mechanism of ST elevation in STEMI  and ST depression in Unstable  angina is   still in the hypothetical stages. One popular theory   says that the   current of injury   as we see   as  ST  segment elevation  in surface ECG  is  actually   an illusion. It’s   apparently due to   constant negative current    pushing down the   rest of ECG segments. Ironically   the concept   of  reciprocal ST depression in patients who have  ST elevation is well debated  for over 3 decades and  is considered  a  settled issue. It   probably   represents , a  purely electrical phenomenon where the  tail end  of the  lead   picks up the opposite vector. Even   as   conflicts   continue to confront the basic electro physiological   concepts management    strategies   of   acute coronary syndromes is witnessing   great strides.
Aim
                                     We   hypothesized   if   ST depression occurs as response to ST elevation it’s logic to expect strong ST depressive forces should  possibly elevate The ST segments in the reciprocal leads .
In fact  we have seen this phenomenon in three distinct  clinical situations. 
1) ST   elevation   in posterior leads: Patients who present   with isolated   ST depression in V1,  V2 , V3  and  ST elevation in posterior chest leads V7, V8 .These patients were initially thought to have isolated posterior MI. But later the cardiac enzymes were found to be normal   indicating no myocardial necrosis   echo evaluation revealed wall motion defects in anterior segments rather than in posterior segments. CAG revealed critical   LAD disease .  This we believe a pure reciprocal ST elevation in the posterior leads to  a  ST depressive forces in anterior leads.
 2) Inferior  ST   elevation   with ST depression   in   V4- V6 : Few  patients who present with  infero    lateral STEMI   later  do not  evolve into  Q  MI but as a NSTEMI .The initial ST elevation  was found  be transient and  disappeared  much earlier,  while the  ST depression  lateral leads persisted.
 3) ST elevation in AVR   in high risk unstable angina :As   already reported in the literature,  we have seen  ST  elevation in AVR  in patients with  high risk unstable angina. This was   more often observed when there is > 3mm ST depression in V4-V6. The AVR  ST elevation  possibly   represents   the  reciprocal  vector.
    Conclusion
                                            ST elevation in certain   specific leads in   some of the patients with ACS,   could   be   a pure reciprocal   electrical phenomenon   to   dominant ST depressive forces in Opposite leads .  And hence   ST elevation in the surface ECG during early hours of ACS   should be interpreted more cautiously. The   sanctity   assocociated with ST segment   elevation   could  be  opened   for debate. 
 
                                     To down load full PPT  click on  the slide

//

Read Full Post »

                    Lateral myocardial infarction is not a common site when compared to anterior and inferior MI. But the lateral MI has some unique features, since it involves free wall of the ventricle.The laplace law mediated wall stress is more as the dyskinetic segments bulge with a long radius .Due to this,  lateral MI has a distinctly high risk for free wall rupture .Further pericardial rub is more common in thse patients.Ischemic mitral regurgitation and vulnerability to LVF is also more prevalent if the lateral wall is involved.  Generally lateral MI pateints have a turbulent and complicated course than a simple inferior or anteroseptal MI.

The angiographic correlation of  lateral MI is rarely reported in literature.

The following leisons are commonly observed.

1. Proximal  LAD with large D1  involvement

2. Isolated large D1/D2 disese

3.A left dominat LCX  with large OM1 disease

4.Large ramus disease

5.LAD total and RCA to LAD/D1 collateral pattern

Final message

If we encounter a lateral MI either alone or in combination with inferior/  posterior MI , it is better to manage these patients  aggresively with early triaging for CAG and revascularisation.

Read Full Post »

« Newer Posts - Older Posts »